Enhancing sulforaphane content

This 2020 Chinese study experimented with enhancing sulforaphane content of broccoli florets in a range of conditions:

“For direct water blanching at 60°C, sulforaphane yield increased with treatment time from 1698.0 ± 121.9 μmol per kg DW (0 min) to 2833.3 ± 118.6 μmol per kg DW (1 min) and then steadily decreased to the lowest value of 2345.8 ± 57.7 μmol per kg DW for 5 min.

The sulforaphane yield of broccoli after 5 min thermal treatment at 65 °C was even lower than the value obtained for raw broccoli. The reason could be leaching of glucoraphanin into blanching water coupled with partial inactivation of myrosinase resulting in low yield of sulforaphane.

For direct water blanching, the best treatment temperature for maximizing sulforaphane yield was 60 °C.

Sulforaphane yield depends on the relative activity of myrosinase and ESP in the broccoli matrix and 3 min treatment at 65 °C during in-pack processing in this study was found to be the best condition that favours conversion into sulforaphane instead of sulforaphane nitrile. This indicates that the condition favours inactivation of ESP to a larger extent while maintaining sufficient myrosinase activity resulting in optimal conversion into sulforaphane.

Under this condition, it seems that all extractable glucoraphanin is converted to sulforaphane assuming 1 to 1 conversion, since glucoraphanin content of broccoli samples were determined to be 3141.2 μmol per kg DW whereas the sulforaphane yield was 3983 μmol per kg DW. The slightly higher sulforaphane yield than would be predicted from the level of glucoraphanin in raw broccoli requires further investigation.”

https://pubs.rsc.org/en/content/articlehtml/2020/fo/c9fo02089f “Mild heat combined with lactic acid fermentation: a novel approach for enhancing sulforaphane yield in broccoli puree”


1. The study presented evidence for kitchen practices:

  • Per the above graphic’s point a, I’ve changed to let broccoli sprout heating continue for 1 minute after microwaving to achieve up to but no more than 60°C (140°F). This allows further myrosinase hydrolization of glucoraphanin into sulforaphane. My practice had been to immediately cool them down, which was suboptimal point c on the 60°C line. I still transfer broccoli sprouts to a strainer immediately after microwaving.
  • The 60°C cliff finding of Microwave broccoli to increase sulforaphane levels was confirmed by this study’s 65°C direct blanching finding.

2. I didn’t view this study’s in-pack or lactic acid bacteria fermentation findings as having practical kitchen use. Maybe it’s a cultural difference?

3. Poor performance at 65°C after 5 minutes was partially attributed to “leaching of glucoraphanin into the blanching water.” But poor 65°C performance was evident at the 1 minute point compared with good 60°C performance.

“Partial inactivation of myrosinase” at 65°C was more likely to be the dominant factor.

4. Regarding:

“The slightly higher sulforaphane yield than would be predicted from the level of glucoraphanin in raw broccoli requires further investigation.”

The microwaving study author was on a productive investigation track with:

“Microwave irradiation might help to release more conjugated forms of glucosinolates and then get hydrolyzed by released myrosinase.”

That track developed in part from finding that broccoli florets microwaved on full power to 60°C increased glucoraphanin past control (raw) levels:

“The control GLR amount was 2.18 µmol/g DW, while the HL60 GLR amount was 2.78 µmol/g DW.”

Not to mention the coincident 1,114% increase in sulforaphane content of ordinary broccoli purchased at a grocery store!


I arrived at this study through it being referenced in the enjoyable 2020 Spanish review Functional Ingredients From Brassicaceae Species: Overview and Perspectives. Those reviewers noted that this study’s 2019 predecessor Fermentation for enhancing the bioconversion of glucoraphanin into sulforaphane and improve the functional attributes of broccoli puree (not freely available) found:

“Preferential formation of SFN-nitrile (less potential as inducer of phase II detoxification enzymes than SFN) instead of SFN.”

Part 3 of Rejuvenation therapy and sulforaphane

Part 1 focused on the study’s clinical biomarkers. Part 2 highlighted its epigenetic clocks. Now we’ll look at rejuvenation of cognitive function.

Charts for this study’s most relevant human aging applications – measured by the new human-rat relative biological age clock – were in supplementary data due to combining study untreated tissue samples into clock training data. Reanalyses showed:

“Using the final version of the epigenetic clocks, we find that treatment effects become even more significant especially for the hypothalamus.”

Human-rat relative clock percentages of rejuvenation were:

  • “Blood 70.6%
  • Liver 79.4%
  • Heart 61.6%
  • Hypothalamus 20.9%”

The Discussion section addressed hypothalamus rejuvenation:

“Why does plasma fraction treatment not reduce brain epigenetic age by the same magnitude as it does other organs? We can only begin to address this question after having first understood what epigenetic aging entails.

As it stands, our knowledge in this area remains limited, but it is nevertheless clear that:

  1. Epigenetic aging is distinct from the process of cellular senescence and telomere attrition,
  2. Several types of tissue stem cells are epigenetically younger than non-stem cells of the same tissue,
  3. A considerable number of age-related methylation sites, including some clock CpGs, are proximal to genes whose proteins are involved in the process of development,
  4. Epigenetic clocks are associated with developmental timing, and
  5. Relate to an epigenomic maintenance system.

Collectively, these features indicate that epigenetic aging is intimately associated with the process of development and homeostatic maintenance of the body post-maturity.

  • While most organs of the body turnover during the lifetime of the host, albeit at different rates, the brain appears at best to do this at a very much slower rate.
  • While most tissues harbor stem cells that are necessary for replenishment and turnover, stem cells in adult brain have only been detected in a defined and very limited area of the subventricular zone, olfactory bulb (in rats), hippocampus and hypothalamic proliferative region.

As such, if plasma fraction treatment’s rejuvenating effect is:

  • Mediated through the process of development and
  • Involves tissue stem cells

then its effect on epigenetic age of the brain would appear to be modest, which indeed it does.

It is to be noted however, that improving brain function does not depend on neurogenesis as much as it does on synapse formation and factors such as NMDA receptors, which decline in density with age.

Assessment of plasma fraction treatment on cognitive function (learning and memory). Rats were subjected to Barnes maze test – nine consecutive days of test where the time (in seconds) required by rats to find the escape hole (latency) was recorded and plotted. Error bars depict 2 standard errors.

Within a month of plasma fraction treatment, rats exhibited significantly reduced latency to escape, i.e., they learned and remembered better. After the second month, treated rats began with a slightly reduced latency period compared to untreated old rats, and once again, they learned much faster than the latter.

By the third month, it was clear that treated rats remembered the maze much better than untreated ones even from the first day of test as their latency period was significantly reduced. By the end of the test period, their latency was similar to that of young rats. This feature was sustained and repeated in the fourth month.”

Not sure why there’s a 62-day gap between “Second month” and “Third month.” Maybe it had something to do with “First month” starting 10 days after the first treatment and “Third month” similarly starting 13 days after the second treatment?


Many of us know older people who lived well past their time of good cognitive function:

  • We see how they’re helpless and dependent; and
  • We see how others take advantage of them in their morbidity phase, where healthspan stops increasing but lifespan continues.

We can make personal plans for that day, sure. But let’s also put some urgency into applying this study’s new human-rat relative biological age clock, and make:

“A step change in aging research. Although conservation of aging mechanism could be equally deduced from the existence of multiple individual clocks for other mammals (mouse, dog), the single formula of the human-rat clock that is equally applicable to both species effectively demonstrates this fact.”

Part 2 of Rejuvenation therapy and sulforaphane

A rejuvenation therapy and sulforaphane focused on the study’s clinical biomarkers and not its biological age measurements. This Part 2 curation of the study highlights its epigenetic clocks because:

“While clinical biomarkers have obvious advantages (being indicative of organ dysfunction or disease), they are neither sufficiently mechanistic nor proximal to fundamental mechanisms of aging to serve as indicators of them. It has long been recognized that epigenetic changes are one of several primary hallmarks of aging.

DNA methylation (DNAm) epigenetic clocks capture aspects of biological age. The discrepancy between DNAm age and chronological age (term as ‘epigenetic age acceleration’) is predictive of all-cause mortality. Pathologies and conditions that are associated with epigenetic age acceleration includes, but are not limited to, cognitive and physical functioning, centenarian status, Down syndrome, HIV infection, obesity, and early menopause.

The [new] human-rat clocks apply to both species. The two human-rat pan-tissue clocks are distinct, by way of measurement parameters. One estimates absolute age (in units of years), while the other estimates relative age, which is the ratio of chronological age to maximum lifespan; with values between 0 and 1. This ratio allows alignment and biologically meaningful comparison between species with very different lifespan (rat and human), which is not afforded by mere measurement of absolute age.

Relative age estimation was made using the formula: Relative age = Age / maxLifespan where the maximum lifespan for rats and humans were set to 3.8 years and 122.5 years, respectively.”

From Supplementary Table 3, old control and old treatment subjects were males 109 weeks old, 55% of their maximum lifespan (109 / 197.6). Young control subjects were males 30 weeks old, 15% of their maximum lifespan.

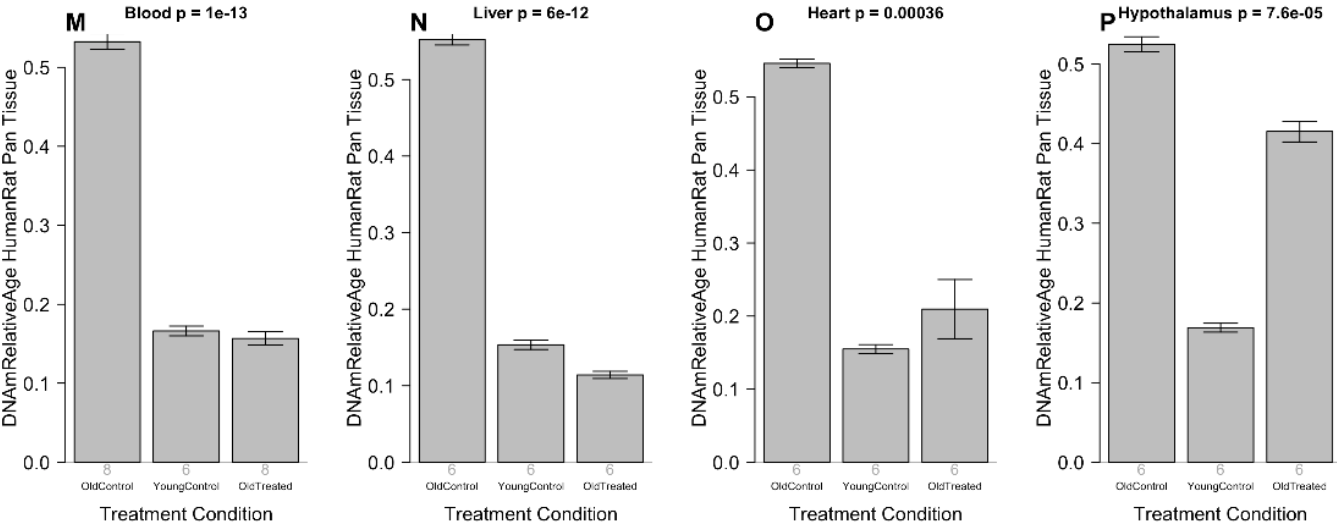
The money charts for this study’s human aging applications – measured by the new human-rat relative biological age clock – were buried in Supplementary Figure 12, bar plots M through P:

“Human-rat clock measure of relative age defined as age/maximum species lifespan. Each bar-plot reports the mean value and one standard error.”

From Supplementary Table 8, the percentages of rejuvenation for the above bar plots, calculated as “(100 * (1 – Old Treated / Old Control)” were:

  • “Blood 70.6%
  • Liver 79.4%
  • Heart 61.6%
  • Hypothalamus 20.9%”

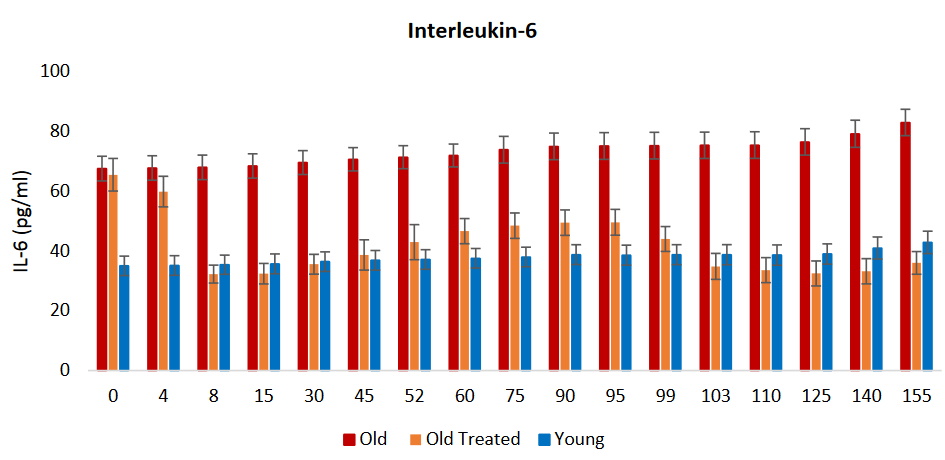
Let’s return to clinical biomarkers for comparison purposes. The current study measured pro-inflammatory cytokine IL-6 blood plasma levels at every time point, but didn’t publish numbers. Bar plots and narrative were:

“Inflammation is an important response that helps protect the body, but excess inflammation especially in terms of duration of this response can have very detrimental effects instead. This occurs when inflammation fails to subside and persists indefinitely; a condition referred to as chronic inflammation, which for reasons not well-understood, increases with age and is associated with a multitude of conditions and pathologies.

The levels of two of the most reliable and common biomarkers of chronic inflammation, interleukin 6 (IL-6) and tumor necrosis factor α (TNF-α), are found to be considerably higher in old rats, and these were very rapidly diminished, within days by plasma fraction treatment, to comparable levels with those of young rats. This was especially stark with IL-6.

In time, the levels of these inflammatory factors began to rise gradually, but they were once again very effectively reduced following the second administration of the plasma fraction on the 95th day.”

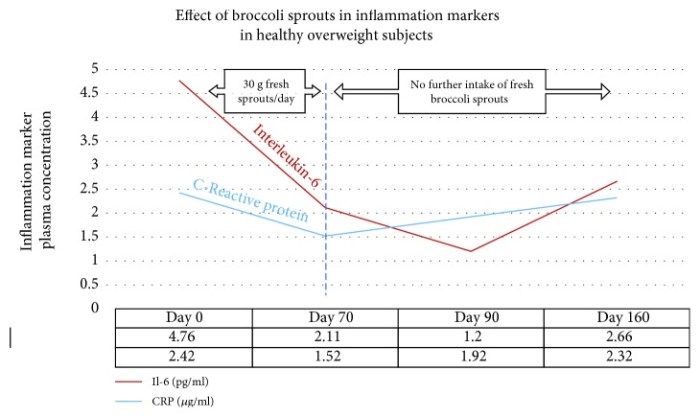
Let’s compare the above IL-6 graphic with IL-6 concentration improvements of our 2018 model clinical trial, Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects, calculated as (100 * (1 – Day _ mean / Day 0 mean):

Mean pg/ml | % improvement | Period | Broccoli sprout consumption

  • 4.594 | 0% | Day 0 | “One week before the beginning of the intervention period, subjects were asked to avoid the consumption of Brassica vegetables (broccoli, radish, cauliflower, Brussel sprouts, mustards, among others) and their derived products.”
  • 1.748 | 62.0% | Day 0 to 70 | Subjects ate 30 g raw broccoli sprouts every day, and stopped eating them after Day 70.
  • 0.896 | 80.5% | Day 0 to 90 | “After the intervention period, a follow-up recovery period for all subjects continued for another 90 days with no ingestion of broccoli sprouts.”
  • 2.170 | 52.8% | Day 0 to 160 | Subjects had not eaten broccoli sprouts after Day 70.

Results between the studies were similar in that:

  1. IL-6 levels improved during early treatments through rat Day 8 and human Day 70, respectively.
  2. IL-6 levels continued decreasing shortly after treatments for 7 days (through rat Day 15) and 20 days (through human Day 90), respectively.
  3. IL-6 levels rose after rat Day 15 and human Day 90, respectively, but were still significantly below Day 0 values at rat Day 95 and human Day 160.

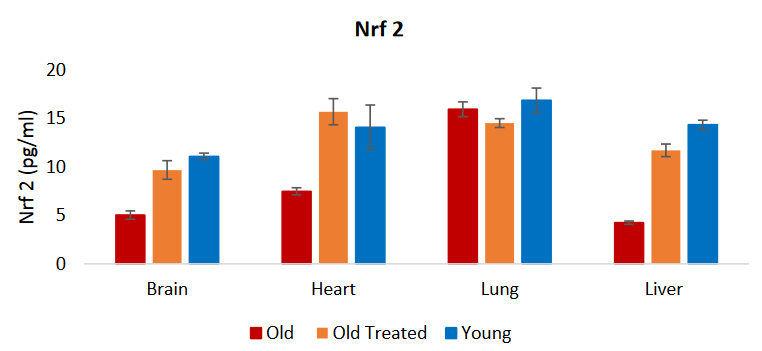
The current study measured Nrf2 but didn’t publish numbers. Bar plots and narrative were:

“The reduction of these inflammation markers is consistent with the profile of the nuclear factor erythroid 2-like 2 protein (Nrf2), which plays a major role in resolving inflammation, in part by inhibiting the expression of IL-6 and TNF-α. Nrf2 also induces the expression of antioxidants that neutralizes ROS [reactive oxygen species], which is also a significant feature in inflammation.”

A PubMed search on “nrf2 sulforaphane human” didn’t turn up relevant 2020 human in vivo studies. I disregarded reviews, cancer studies, disproven hypotheses, and other compounds listed in the below graphic.

I won’t repeat the entire Nrf2 section from the Part 1 curation, just one graphic and paragraph:

It [sulforaphane] is not only a potent Nrf2 inducer but also highly bioavailable [around 80%], so that modest practical doses can produce significant clinical responses. Other Nrf2 activators [shown in the above image] not only lack potency but also lack the bioavailability to be considered as significant intracellular Nrf2 activators.”


As noted in Reviewing clinical trials of broccoli sprouts and their compounds, there are no sulforaphane clinical trials that also use epigenetic clocks. Broccoli sprouts and their compounds’ effects on human aging is an area that hasn’t drawn attention and funding.

What effects may broccoli sprout compounds have on human aging? With this new human-rat relative biological age clock, researchers can get reliable answers from rat studies, with human clinical trials needed only to confirm those findings!

As rejuvenation research continues, what could people do easily, cheaply, and today for our long-term selves? Don’t know about the hypothalamus, but our blood, liver, and heart biological ages may decrease as we reduce inflammation and oxidative stress by eating broccoli sprouts.

I’m at a similar percentage of species maximum lifespan as were the study’s treated subjects. It’s my choice as to what my healthspan will be.

There isn’t evidence today to definitively say that changing my inflammatory phenotype with broccoli sprouts has had / will have rejuvenation effects on biological ages of my cells, organs, and body. But if eating broccoli sprouts every day not only reduces chronic inflammation and oxidative stress as expected, but also makes me younger, I could probably learn to live with that. 🙂

Continued with Part 3 of Rejuvenation therapy and sulforaphane.

An environmental signaling paradigm of aging

To follow up A rejuvenation therapy and sulforaphane, the study’s lead laboratory researcher – Dr. Harold Katcher – provided evidence for an environmental signaling paradigm of aging in this 2015 paper:

“The age-phenotype of a cell or organ depends on its environment and not its history.

Organ dysfunction is not the cause of aging, but is the result of its milieu. Therefore, the aged milieu is the cause. Though it has been thought that the aging immune system is the cause of aging, it can seen to be the result of aging.

The systemic milieu of an organism sets the age-phenotype of its cells, tissues and organs. Cells and organs secrete factors into blood, which are determined by the age-phenotype and repair-states of those cells and organs. The presence and concentrations of these blood-borne factors determine the age-phenotype of cells and organs.

Here we must be a bit more speculative. Changes in concentrations of factors present in blood, rather than their presence or absence, determines age-phenotype.

Interactions between disparate levels of the body’s hierarchy establish a consensus age-phenotype for cells and organs, and this largely occurs via the bloodstream. There appear to be positive factors that promote youthful age-phenotypes and negative factors that promote the aged phenotypes.

We readily consider development as a ‘program’, and it seems clear that we must consider post-adult development as ‘programmed’ as well. But if there is a program it is neither in genes nor chromatin, but in interaction of complex, interconnected systems spanning hierarchical levels.

If these aforementioned principles are correct, it should be easy to verify. If so, whole organism rejuvenation might require little more than:

  • Changing concentrations of all age-determining molecules of the bloodstream and various stem cell niche environments to youthful levels;
  • For a time sufficient to cause rejuvenation at the cellular level.

Once cells start secreting factors appropriate to their new, younger age-phenotypes, cognate changes should propagate through hierarchical levels.

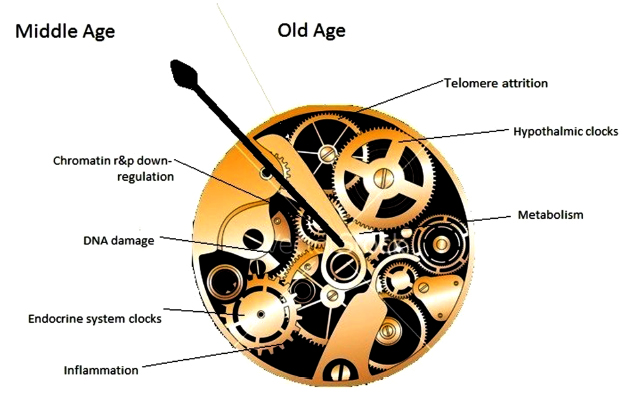
The analogy to workings of a mechanical clock is not very exact. ‘Gears’ represent individual aging clocks, both cellular and organic (shown at different levels within the mechanism) which interact, ultimately resulting in organismic age, i.e. ‘body clock’, represented by the ‘hour hand’ (no minute hand is shown).

In mammals, readout of the clock corresponds to age-related composition of blood plasma. In this model, moving the hour hand backwards should result in a turning back of composite clocks as well – a result obtained when induction to pluripotence is used to reset cellular clocks.

Apart from being slowed down or sped up, the body clock can also be reset. Organisms, organs, and their cells can be reset to different age-phenotypes depending on their environment.

We know that old transplanted tissues and organs can regain function and live for the entire life of the younger host at least in rodents. We must suppose that age-phenotype changes must have taken place at the cellular level to allow this.

Rejuvenation cannot be explained on the basis that aging represents accumulation of irreparable cellular damage.

None of these principles are rigorously established as such, but all are supported by experimental evidence.”

http://www.eurekaselect.com/130538/article “Towards an Evidence-based Model of Aging”


Here are some of his responses to comments on the blog post that first curated his current research:

“We’ve (scientists), spent the past 70 years trying to definitively prove the commonsense ‘wear and tear’ theories and have not succeeded. So I tried something different, looking at results of experiments.

This is not based on ‘theory’ (say mitochondrial aging or ‘wear and tear’) but on experimental evidence. Theory comes in explaining our results, not achieving them. There is a theory becoming clear, one very different from the commonsense view of ‘wear and tear’ aging.

We haven’t examined immune response. All that we know for sure is that chronic inflammation of aging stopped. I can definitively say that chronic inflammation due to aging can be reversed with factors present in young blood.

There are amazing things that Big Pharma won’t touch as there’s not enough profit in them (they can’t be patented). So I guess we’re somewhat the same, but we know what to do and have proven it – for us, it’s not money. However, money allows you to do things.

Being 75 myself puts a time-frame around the project. We plan to propose its use for diseases of aging – eventually, everyone will use it. It will end up changing humanity. As people already seem to have too much free time to begin with, what will people do with those extra years they will be given?”


Sections 3 “Aging Manifestations that Have Hitherto Been Proposed as the Causes of Aging are the Consequences of Aging” and 10 “Several Factors ‘Conspire’ to Promote Inflammation in Old Mammalian Bodies, Inflammation Leads to Several Diseases of Aging and Perhaps to Aging Itself” were especially informative.

The former section discussed cells that were capable of making repairs but didn’t make repairs, with aging being the consequence of this behavior. The latter reviewed topics such as senescence, IL-6, NF-κB, and C-reactive protein in terms of feedback loops.

See Reevaluate findings in another paradigm for comparisons of Section 6 with another view of hypothalamic aging.

A rejuvenation therapy and sulforaphane

The founder of the epigenetic clock methodology with the coauthor of Aging as an unintended consequence released a 2020 rodent study “Reversing age: dual species measurement of epigenetic age with a single clock” at https://www.biorxiv.org/content/10.1101/2020.05.07.082917v1.full.pdf:

“We employed six clocks to investigate the rejuvenation effects of a plasma fraction treatment in different rat tissues. Two of these epigenetic clocks apply to both humans and rats.

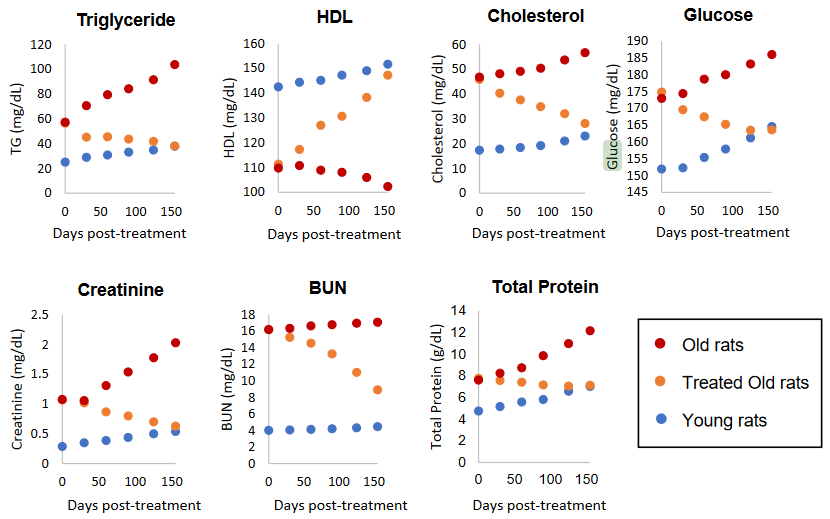
The treatment more than halved the epigenetic ages of blood, heart, and liver tissue. A less pronounced, but statistically significant, rejuvenation effect could be observed in the hypothalamus.

The treatment was accompanied by progressive improvement in the function of these organs as ascertained through numerous biochemical/physiological biomarkers and behavioral responses to assess cognitive functions. Cellular senescence, which is not associated with epigenetic aging, was also considerably reduced in vital organs.

Plasma fraction treatment consists of two series of intravenous injections of plasma fraction. Rats were injected four times on alternate days for 8 days. A second identical series of injections were administered 95 days later. In its entirety, the experiment lasted 155 days.

Overall, this study demonstrates that a plasma-derived treatment markedly reverses aging according to epigenetic clocks and benchmark biomarkers of aging.”

The study hasn’t been peer reviewed, so can’t be viewed yet as conclusive. Given that researchers’ single-most valuable asset is their reputations, though, will the findings have major revisions?


I was alerted to the study by Josh Mitteldorf’s blog post Age Reduction Breakthrough, who did his usual excellent curation:

“Most of the explosion in aging research (and virtually all the venture capital startups) are looking to treat aging at the cellular level. Their paradigm is that aging is an accumulation of molecular damage, and they see their job as engineering of appropriate repair mechanisms.

The truth, as Katcher [the lead lab researcher] understands it, is that, to a large extent, aging is coordinated system-wide via signal molecules in the blood. The problem is that there are thousands of constituents represented in tiny concentrations in blood plasma, but conveying messages that cells read. Which of these are responsible for aging?

The two-species clock[s] was [were] a significant innovation, a first bridge for translating results from an animal model into their probable equivalent in humans. Besides the methylation clock[s], the paper presents evidence of rejuvenation by many other measures. For example:

  • IL-6, a marker of inflammation, was restored to low youthful levels;
  • Glutathione (GSH), superoxide dismutase (SOD), and other antioxidants were restored to higher youthful levels;
  • In tests of cognitive function (Barnes maze), treated rats scored better than old rats, but not as well as young rats.;
  • Blood triglycerides were brought down to youthful levels;
  • HDL cholesterol rose to youthful levels; and
  • Blood glucose fell toward youthful levels.

These results bring together three threads that have been gaining credibility over the last decade. Mutually reinforcing, the three have a strength that none of them could offer separately.

  1. The root cause of aging is epigenetic progression = changes in gene expression over a lifetime.
  2. Methylation patterns in nuclear DNA are not merely a marker of aging, but its primary source. Thus aging can be reversed by reprogramming DNA methylation.
  3. Information about the body’s age state is transmitted system-wide via signal molecules in the blood. Locally, tissues respond to these signals and adopt a young or an old cellular phenotype as they are directed.”

Several of these aging measurements are also positively affected by sulforaphane. Using Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease as a reference:

1. “Chronic inflammation”

“Antioxidants in general and glutathione in particular can be depleted rapidly under conditions of oxidative stress, and this can signal inflammatory pathways associated with NF-κB. SFN [sulforaphane] has been shown to inhibit NF-κB in endothelial cells.

Two key inflammatory cytokines were measured at four time points in forty healthy overweight people [our model clinical trial, Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects]. The levels of both interleukin-6 (Il-6) and C-reactive protein (CRP) declined over the 70 days during which the sprouts were ingested. These biomarkers were measured again at day 90, wherein it was found that Il-6 continued to decline, whereas CRP climbed again. When the final measurement was taken at day 160, CRP, although climbing, had not returned to its baseline value. Il-6 remained significantly below the baseline level at day 160.”

OMCL2019-2716870.010

2. “Oxidative stress”

“As a mediator for amplification of the mammalian defence system against various stressors, Nrf2 [nuclear factor erythroid 2-related factor 2] sits at the interface between our prior understanding of oxidative stress and the endogenous mechanisms cells use to deal with it. Diseases known to be underpinned by oxidative stress are proving to be more responsive to amplification of cellular defences via Nrf2 activation than by administration of direct-acting antioxidant supplements.

SFN, with absolute bioavailability of around 80%, [is] capable of increasing several endogenous antioxidant compounds via the transcription factor, Nrf2.

Nrf2 is ubiquitously expressed with the highest concentrations (in descending order) in the kidney, muscle, lung, heart, liver, and brain. Nrf2 was shown to prevent endothelial cells from exhibiting a proinflammatory state. Nrf2 is required for protection against glucose-induced oxidative stress and cardiomyopathy in the heart.

Well in excess of 500 genes have been identified as being activated by SFN via the Nrf2/ARE [Antioxidant Response Element] pathway, and it is likely that this underestimates the number as others are being discovered. Of the available SFN clinical trials associated with genes induced via Nrf2 activation, many demonstrate a linear dose-response. More recently, it has become apparent that SFN can behave hormetically with different effects responsive to different doses.

It [sulforaphane] is not only a potent Nrf2 inducer but also highly bioavailable so that modest practical doses can produce significant clinical responses. Other Nrf2 activators [shown in the above image] not only lack potency but also lack the bioavailability to be considered as significant intracellular Nrf2 activators.”


The study’s most relentlessly questioned, scrutinized, and criticized findings may be the two new epigenetic clocks that apply to both humans and rats. The researchers invited other researchers to validate these clocks because:

“If validated, this would be a step change in aging research. Although conservation of aging mechanism could be equally deduced from the existence of multiple individual clocks for other mammals (mouse, dog), the single formula of the human-rat clock that is equally applicable to both species effectively demonstrates this fact.”

The commonalities of this study with efforts to change my inflammatory phenotype with broccoli sprouts were summarized in the Discussion section:

“Apart from rejuvenating the vital organs of the treated rats, plasma fraction also impacted two fundamental physiological processes that underlie a great number of pathologies, namely oxidative stress and inflammation. Within a week of treatment, the markers of chronic inflammation (IL-6 and TNF-α) were significantly reduced and remained low throughout the entire experiment.

Likewise, markers of oxidative stress in brain, heart, lung and liver, which were very much higher in control old rats, were at the end of the experimental period, indistinguishable between plasma fraction-treated old rats and young ones. Concomitant with this drastic reduction in oxidative stress was the augmented levels of antioxidants (GSH, Catalase and SOD) in these tissues, indicating that modulating the levels of ROS [reactive oxygen species] to that of youthful rats is at least one way by which plasma fraction suppresses oxidative stress. It remains to be ascertained whether the rate of ROS generation is also reduced.

The levels of Nrf2, a transcription factor that impacts on oxidative stress, as well as inflammation, were raised by plasma fraction treatment of old rats to those of the young ones, indicating yet another level by which this treatment modulates these two critical processes. Collectively, these results show that plasma fraction treatment impacts not only the overt performances of organs, but also the underlying physiological processes that are pivotal for optimal organ function and health.”

Great stuff, huh? Are you ready to change your phenotype?

Continued with Part 2 of Rejuvenation therapy and sulforaphane.

Work your voluntary muscles today

This 2020 review by the Aging as a disease research group highlighted their specialty:

“A theory that fits both the aging and the rejuvenation data suggests that aging is caused primarily by the functional (and notably, experimentally reversible) inactivation of resident stem cells, which precipitates deteriorated tissue maintenance and repair and leads to the loss of organ homeostasis.

The damaged and unrepaired tissues suffer changes in their biochemistry, including the molecular crosstalk with resident stem cells, which further inhibits productive, regenerative responses. The inflammatory and fibrotic secretome can then propagate systemically, affecting the entire organism.

Skeletal muscle accounts for almost 40% of the total adult human body mass. This tissue is indispensable for vital functions such as respiration, locomotion, and voluntary movements and is among the most age-sensitive in mammals.

Muscle is capable of active repair in response to daily wear and tear, intense exercises, or injuries. Muscle regeneration relies on the adult muscle stem cells, also called satellite cells.

Rather than a significant decline in the total number with age, most of the data support a dramatic lack of activation of muscle stem cells after injury and a concomitant lack in the formation of progenitors that are needed for repair.

Multiple experimental approaches have been used for tissue rejuvenation and/or systemic rejuvenation; these include ablation of senescent cells and re-calibration of key signaling pathways that are needed for productive stem cell responses. To test the success in experimental rejuvenation, 1-4 approaches are typically applied, and skeletal muscle is well-suited for assaying each one.”

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7007696/ “Skeletal muscle as an experimental model of choice to study tissue aging and rejuvenation”


The review had a short section on inflammation details. Not enough, and there’s no tissue repair. Continuing unchecked is a systemic issue that led the reviewers to their paradigm of aging as a disease.

The review concluded with a subject that’s taught in high school, and should be understood at least before college graduation. It’s curious that an item like sample size required emphasis. Maybe research that doesn’t adhere to basics is a current issue?

Aging as an unintended consequence

The coauthors of 2018’s The epigenetic clock theory of aging reviewed progress that’s been made todate in understanding epigenetic clock mechanisms.

1. Proven DNA methylation features of epigenetic clocks:

  1. “Methylation of cytosines is undoubtedly a binary event.
  2. The increase in epigenetic age is contributed by changes of methylation profiles in a very small percent of cells in a population.
  3. The clock ticks extremely fast in early post-natal years and much slower after puberty.
  4. Clock CpGs have specific locations in the genome.
  5. It applies to prenatal biological samples and embryonic stem cells.

While consistency with all the five attributes does not guarantee veracity of a model, inconsistency with any one will signal the unlikely validity of a hypothesis.”

2. Regarding what epigenetic clocks don’t measure:

“The effects of

  • Telomere maintenance,
  • Cellular senescence,
  • DNA damage signaling,
  • Terminal differentiation and
  • Cellular proliferation

have all been tested and found to be unrelated to epigenetic ageing.”

3. Regarding cyclical features:

“Both the epigenetic and circadian clocks are present in all cells of the body, but their ticking rates are regulated. Both these clocks lose synchronicity when cells are isolated from tissues and grown in vitro.

These similarities compel one to ponder potential links between them.”

This was among the points that Linear thinking about biological age clocks missed.

4. The reviewers discussed 3 of the 5 treatment elements in Reversal of aging and immunosenescent trends:

“It is not known at this stage whether the rejuvenating effect is mediated through the regeneration of the thymus or a direct effect of the treatment modality on the body. Also, it is not known if the effect is mediated by all three compounds or one or two of them.

What we know at this stage does not allow the formation of general principles regarding the impact of hormones on epigenetic age, but their involvement in development and maintenance of the body argue that they do indeed have a very significant impact on the epigenetic clock.”

Not sure why they omitted 3000 IU vitamin D and 50 mg zinc, especially since:

“It is not known if the effect is mediated by all three [five] compounds or one or two of them.”

5. They touched on the specialty of Aging as a disease researchers with:

“Muscle stem cells isolated from mice were epigenetically much younger independently of the ages of the tissue / animal from which they were derived.

The proliferation and differentiation of muscle stem cells cease upon physical maturation. These activities are initiated in adult muscles only in response to injury.“

6. The reviewers agreed with those researchers in the Conclusion:

“Epigenetic ageing begins from very early moments after the embryonic stem cell stage and continues uninterrupted through the entire lifespan. The significance of this is profound as the question of why we age has been attributed to many different things, most commonly to ‘wear-and-tear.’

The ticking of the epigenetic clock from the embryonic state challenges this perspective and supports the notion that ageing is an unintended consequence of processes that are necessary for

  • The development of the organism and
  • Tissue homeostasis thereafter.”


https://journals.sagepub.com/doi/10.1177/1535370220918329 “Current perspectives on the cellular and molecular features of epigenetic ageing” (not freely available)

Linear thinking about biological age clocks

This 2020 review by a Hong Kong company’s researchers compared and contrasted measures of biological age:

“More than a dozen aging clocks use molecular features to predict an organism’s age, each of them utilizing different data types and training procedures. We offer a detailed comparison of existing mouse and human aging clocks, discuss their technological limitations and the underlying machine learning algorithms. We also discuss promising future directions of research.

Biomarkers placed on an intuitive plane of Accuracy vs Utility. Bubble size depends on the number of clocks based on a corresponding aging biomarker.

Currently, DNAm [DNA methylation] is the most accurate and the most frequently used biomarker in biohorology. However, it is harder to apply a DNAm clock compared to clocks based on clinical blood tests. Moreover, DNAm marks often take a long time to emerge in response to aging interventions.

Chromatin structure and telomeres, while intriguing, are too labor intensive and error-prone to be practical.”

https://www.sciencedirect.com/science/article/pii/S1568163719302582 “Biohorology and biomarkers of aging: current state-of-the-art, challenges and opportunities”


We think about chronological age linearly. The reviewers hinted at but didn’t directly assess the extent to which techniques such as linear regression may also influence people to think linearly about biological age.

We experience cyclical changes every day (like sleep), month, season, and longer periods. The reviewers didn’t mention techniques that incorporate our cyclical experiences or assess cyclical biological age.

1. The reviewers pointed out some biological age clock linearity flaws:

“Most aging clocks base their BA [biological age] definitions either on CA [chronological age] or mortality risk. Mortality risk in its turn is derived from demographic tables and can be assumed to be a function of CA in most animals, including human.

Thus, aging clocks are ultimately treating CA as a substitute BA with the caveat that deviations from the actual CA signify better or worse physical fitness when compared to age matched controls. Such a design has several flaws.”

2. They pointed out non-linear characteristics of chromosomal telomere length:

“DNA lesions caused by oxidative stress are repaired less efficiently in telomeric regions, which causes frailty and subsequent telomere shortening. Oxidative stress levels may fluctuate due to habitat, life style, inflammatory diseases – factors that do not necessarily represent replicative clock ticking.

Telomere length typically fluctuates within ±2-4% per month. This led scientists to hypothesize that telomere attrition is an oscillatory process.”

Since cell components show cyclical phases, why wouldn’t cells and each higher living structural level likewise demonstrate cyclical phases? That avenue wasn’t explored.

3. They mentioned the non-linearity of epigenetic clocks:

“If an organism’s DNAm profile is not directly linked to the thermodynamic root of aging [entropy] but instead is a downstream product of competing processes, the applicability of DNAm aging clock methodology is at risk. In this case different aging clocks may not be equally good for different experiment settings.

While genetic, pharmacological and dietary interventions with proven effect on life expectancy change the methylation state of the age-associated CpG sites, they do so in different ways. Caloric restriction is more efficient in preventing methylation loss at hypomethylated sites and methylation gain at hypermethylated sites than rapamycin.

These findings imply that DNAm profiles do not simply gravitate towards the average with age and that there is no single pathway through which all aging processes are imbued into an organism’s epigenetic landscape.”

4. Genetic and epigenetic regulatory pathways were presented with linear thinking:

“Protein structures encapsulating DNA and regulating its accessibility (chromatin and histones) have also been shown to change with age. Moreover, DNAm machinery and histone modifications are interlinked and change throughout aging concordantly.

For example, DNA methyltransferases are attracted by the H3K36me mark. With aging it is less tightly regulated, and thus, more sporadic DNAm occurs, which ultimately translates to epigenetic clock ticking.”


An individual’s capability to regulate their own aging phenotype wasn’t addressed, only externally applied “aging interventions.” Diseases were considered chronological-“age-associated.”

Biological aging was neither viewed as a disease nor as an unintended consequence. If these researchers don’t grasp the foundations of their field of study, why do they work in the biological aging field? It isn’t just math.

  • Could this paper reflect one company’s desire to frame arguments in favor of the company’s offered solution?
  • Could this paper reflect a “chronological age is the cause” meme that satisfied organizational imperatives for sponsors like the Buck Institute for Research on Aging?
  • Or could it be that the reviewers had other paradigms?

What do you think?

Broccoli sprouts oppose effects of advanced glycation end products (AGEs)

This 2020 Australian/UK review subject was AGEs:

“AGEs are formed during cooking and food processing or produced endogenously as a consequence of metabolism. Deleterious effects of AGEs are underpinned by their ability to trigger mechanisms well known to elicit metabolic dysfunction, including activation of inflammatory pathways, oxidative stress and impaired mitochondrial oxidative metabolism. They have been widely implicated in complications of diabetes affecting cardiovascular health, the nervous system, eyes and kidneys.

Reactive carbonyl groups are constantly being produced via normal metabolism and when production overrides detoxification, AGEs accumulate. AGE formation may take several days or weeks to complete in the body.

Factors affecting AGE content of food depends on composition of protein, fat, and sugar and types of processing and cooking methods employed, predominantly on temperature and duration of preparation. Circulating free-AGEs concentrations are a good marker for dietary AGE intake while plasma protein-bound AGEs better represent endogenously produced AGEs.

Receptor for Advanced glycation end products (RAGE) signals via transcription factor NF-kB increasing gene expression of inflammatory mediators and production of ROS (reactive oxygen species).”

https://onlinelibrary.wiley.com/doi/abs/10.1002/mnfr.201900934 “The Role of Dietary Advanced Glycation End Products (AGEs) in Metabolic Dysfunction” (not freely available)


Let’s use the Australian 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease as a reference for how sulforaphane may counter effects of AGEs:

1. “Activation of inflammatory pathways”

“Antioxidants in general and glutathione in particular can be depleted rapidly under conditions of oxidative stress, and this can signal inflammatory pathways associated with NF-κB. SFN [sulforaphane] has been shown to inhibit NF-κB in endothelial cells.

Two key inflammatory cytokines were measured at four time points in forty healthy overweight people [our model clinical trial, Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects]. Levels of both interleukin-6 (Il-6) and C-reactive protein (CRP) declined over the 70 days during which sprouts were ingested. These biomarkers were measured again at day 90, wherein it was found that Il-6 continued to decline, whereas CRP climbed again. When the final measurement was taken at day 160, CRP, although climbing, had not returned to its baseline value. Il-6 remained significantly below the baseline level at day 160.”

OMCL2019-2716870.010

2. “When production overrides detoxification”

“SFN significantly activates Nrf2 and as such has the potential to modulate the expression of genes associated with redox balance, inflammation, detoxification, and antimicrobial capacity, all key components of the upstream cellular defence processes.

Toxins presented to Phase 1 enzymes produce intermediate compounds which are sometimes more toxic to cells than the initial toxin. It is therefore important that Phase 2 is sufficiently active that intermediate products cannot accumulate in the cellular environment.

As a monofunctional inducer, SFN has been described as an ideal detoxifier, as its effect on Phase 1 is minimal compared with its significant activity on Phase 2.”

3. “Oxidative stress”

“As a mediator for amplification of the mammalian defence system against various stressors, Nrf2 sits at the interface between our prior understanding of oxidative stress and endogenous mechanisms cells use to deal with it. Diseases known to be underpinned by oxidative stress are proving to be more responsive to amplification of cellular defences via Nrf2 activation than by administration of direct-acting antioxidant supplements.

SFN, with absolute bioavailability of around 80%, is capable of increasing several endogenous antioxidant compounds via transcription factor Nrf2.”

4. “Complications of diabetes affecting cardiovascular health, the nervous system, eyes and kidneys”

“Nrf2 is ubiquitously expressed with highest concentrations (in descending order) in the kidney, muscle, lung, heart, liver, and brain. Nrf2 was shown to prevent endothelial cells from exhibiting a proinflammatory state. Nrf2 is required for protection against glucose-induced oxidative stress and cardiomyopathy in the heart.

Well in excess of 500 genes have been identified as being activated by SFN via the Nrf2/ARE [Antioxidant Response Element] pathway, and it is likely that this underestimates the number as others are being discovered. Of available SFN clinical trials associated with genes induced via Nrf2 activation, many demonstrate a linear dose-response. More recently, it has become apparent that SFN can behave hormetically with different effects responsive to different doses.

It [sulforaphane] is not only a potent Nrf2 inducer but also highly bioavailable so that modest practical doses can produce significant clinical responses. Other Nrf2 activators [shown in the above image] not only lack potency but also lack the bioavailability to be considered as significant intracellular Nrf2 activators.”


As mentioned in Changing an inflammatory phenotype with broccoli sprouts, per the above bolded part of section 3, I stopped taking N-acetyl-cysteine, the precursor to our endogenous antioxidant glutathione. I stopped taking curcumin last year due to no noticeable effects, probably because of its poor bioavailability. I may soon stop taking more vitamin E than the RDA, and β-carotene.

I changed my diet last summer to reduce AGEs, with mild effects. I expect stronger effects from also daily eating 60 grams of 3-day-old broccoli sprouts that yield 27 mg of sulforaphane after microwaving.

Reviewing clinical trials of broccoli sprouts and their compounds

This 2020 Spanish review analyzed recent clinical trials that used broccoli sprouts and their compounds. Stringent criteria for study selection resulted in few trials being considered:

  • “We reduced the timeframe to the last years, from 2012 to the present.
  • We focused our work on the data of studies carried out with human adults with different pathologies.
  • Articles [that] did not provide us with specific information about consumption of cruciferous foods or ingredients derived from Brassicaceae products, documents based on healthy volunteers, and patients with pathologies unrelated to our objective of study were also not included in the analysis.”

None of the 15 analyzed clinical trials were unqualified successes. Some of the problems noted were summarized in this critique of the largest study:

“The authors presented the results that there was a risk for T2DM [type 2 diabetes mellitus] with the intake of cruciferous foods and glucosinolates. However, this study presented big limitations because:

  • It did not review or consider the cooking procedures,
  • It did not quantify the amount of vegetables consumed on a daily or weekly basis, and
  • It did not quantify the glucosinolate contents in the different vegetables consumed. Besides,
  • The population sample was homogenous, because all of the participants were health-area workers, and the results are not extrapolatable to the general population. Finally, it should be highlighted that
  • Other nutrients and confounding factors were not considered in the study, and they could affect the development of these pathologies.”

“Figure 1 – General scheme of the glucosinolates (GSLs) and common hydrolysis products. ESP: Epithiospecifer proteins.”

https://www.mdpi.com/1420-3049/25/7/1591/htm “The Role of Brassica Bioactives on Human Health: Are We Studying It the Right Way?”


The reviewers’ answer to the title’s question “Are We Studying It the Right Way?” was NO. The 15 analyzed trials lacked one or more clearly defined measurements related to their target diseases:

“It is crucial that the outcome measure is of biological relevance; biomarkers or risk factors measured must be associated to the latter development of a disease. The degree of progression of the disease greatly influences the response observed.”

So: Why not consider Aging as a disease for clinical trials with broccoli sprouts and their compounds?

  1. “Lack of cure goes hand in hand with inability to accept that this [aging] is disease. It used to be that, please do not diagnose that there’s bacterial meningitis, because there is no cure. Whatever else you can come up with, do it first. Now, diagnose it as fast as possible, so we can put patients on antibiotics immediately. The same will happen to aging.”
  2. Several of the clinical trials’ methodological and statistical problems could be resolved with recognizing aging as a disease. “Healthy” old people who have no other diseases may be scarce, but there are large populations to sample control groups from among healthy and unhealthy young people, and unhealthy old people.
  3. The reviewers already have experience in using “healthy” 46 ± 6 year-old people in a clinical trial of broccoli sprouts and their compounds.
  4. A wide range of epigenetic clocks are available to test the efficacy of broccoli sprouts and their compounds with respect to human aging phenotypes.

As far as I can tell, epigenetic clocks haven’t been used in the subject area thus far! The review’s reference [7] from 2015 didn’t mention them.

Reference [55] was the October 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease, which I’ve been using as the most current and comprehensive of the subject todate. Its references of broccoli sprouts and their compounds with respect to aging included:

“Nrf2 [nuclear factor erythroid 2-related factor 2] transcriptional activity declines with age, leading to age-related GSH [reduced glutathione] loss among other losses associated with Nrf2-activated genes. This effect has implications, too, for decline in vascular function with age. Some of the age-related decline in function can be restored with Nrf2 activation by SFN [sulforaphane].

A potent Nrf2 activator is capable of inducing hundreds of genes simultaneously. Of the phytochemicals with Nrf2 inducer capacity, Brassica-derived SFN is the most potent naturally occurring biomolecule known at this time.”

However, it had only one reference of DNA methylation, the 2015 The Role of Sulforaphane in Epigenetic Mechanisms, Including Interdependence between Histone Modification and DNA Methylation. Even that was a review rather than a study, and it had no mention of epigenetic clocks.

Maybe broccoli sprouts and their compounds’ effects on human aging is an area that just hasn’t drawn attention and funding?

Growing a broccoli sprouts Victory Garden

To follow up How much sulforaphane is suitable for healthy people? I’ve started growing broccoli sprouts, and a “30 60 grams of fresh broccoli sprouts incorporated daily into the diet” [1] program. See Week 2 of Changing an inflammatory phenotype with broccoli sprouts for changes.

I loosely follow [2]‘s sprouting guidelines. One preparation difference is microwaving per [3]‘s findings as follows:

My current microwaving time for 60 grams of 3-day-old broccoli sprouts in 100 ml of water with a 1000 W microwave on full power is 35 seconds. The temperature gets up to 57°C. See Enhancing sulforaphane content for changes. I immediately dump the broccoli sprouts into a colander and spray with cold water to stop heating at the desired temperature.

The first batch of broccoli sprouts was a mild, cabbage-tasting side dish to the home-style chicken soup on page 238 of [4].

The a priori hypotheses:

    1. 30 grams of fresh broccoli sprouts will not have “51 mg (117 μmol)” of glucoraphanin [1] because they “Used the elicitor methyl jasmonate (MeJA) by priming the seeds as well as by spraying daily. MeJA at concentrations of 156 μM act as stressor in the plant and enhances the biosynthesis of the phytochemicals glucosinolates. Compared to control plants without MeJA treatment, the content of compounds as the aliphatic glucosinolate glucoraphanin was enhanced up to 70%.” 117 μmol / 1.70 = 69 μmol is the expected glucoraphanin amount in 30 grams weight of fresh broccoli sprouts. 69 x 2 = 138 μmol in 60 grams.
    2. One measurement [5] of how much sulforaphane is present in fresh broccoli sprouts before microwaving is 100 μmol / 111 g = .9 μmol / g. (.9 x 30 g) = 27 μmol is the expected sulforaphane amount in 30 grams of fresh broccoli sprouts. Changed assumption to 0 μmol sulforaphane due to 2013 Sulforaphane: translational research from laboratory bench to clinic “Broccoli sprouts are correctly described as releasing, generating, or yielding but not containing SFN [sulforaphane].”
    3. Last week a [3] coauthor agreed to make the data available to facilitate calculations. While I’m waiting… The study said the Figure 3 HL60 sulforaphane amount was 2.45 μmol / g. Eyeball estimate of the below Figure 3 control (raw broccoli florets) is a glucoraphanin amount of ~2.2 μmol / g. I assume that the broccoli florets and sprouts conversion would be the same at a 2.45 μmol / 2.2 μmol ≈ 1.11 ratio. I expect that microwaving the raw broccoli sprouts to 60°C will convert the 138 μmol of glucoraphanin to a 153 μmol amount of sulforaphane at this assumed 1.11 conversion ratio.
    4. The estimated sulforaphane weight per [6] would be (153 μmol / 5.64) = 27 mg which is comparable to clinical trial dosages listed in [7] and [8].
    5. I’ve been sitting around a lot since returning from Milano, Italy, on February 24, 2020, and probably weigh around 75 kg. The estimated dosage represents 153 μmol of sulforaphane / 75 kg = 2.04 μmol of sulforaphane / kg, compared to the 1.36 μmol of glucoraphanin / kg average of [1]. (The study provided the subjects’ mean weight in Table 1 as “85.8 ± 16.7 kg.” The average dosage per kg body weight was 117 μmol of glucoraphanin / 85.8 kg = 1.36 μmol of glucoraphanin / kg.)
    6. Don’t have a practical estimate of the amount of sulforaphane I metabolize from post-microwave glucoraphanin that would add to the calculated 153 μmol of sulforaphane. Both [7] and [8] cited a 2012 study that found: “Some conversion of GRN [glucoraphanin] to SFN can occur in response to metabolism by the gut microflora; however, the response is inefficient, having been shown to vary ‘from about 1% to more than 40% of the dose.’”
    7. Don’t have a practical estimate of the “internal dose” [8] that would result from 153+ μmol of sulforaphane.

I don’t have a laboratory in my kitchen 🙂 and won’t have quantified results. See Grow a broccoli sprouts Victory Garden today! for August 2020 practices.


References in order of citation:

[1] 2018 Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects

[2] 2017 You Need Sulforaphane – How and Why to Grow Broccoli Sprouts

[3] 2020 Microwave cooking increases sulforaphane level in broccoli curated in Microwave broccoli to increase sulforaphane levels

fsn31493-fig-0003-m

[4] 2016 Dr. Vlassara’s AGE-Less Diet: How a Chemical in the Foods We Eat Promotes Disease, Obesity, and Aging and the Steps We Can Take to Stop It

[5] 2016 Effect of Broccoli Sprouts and Live Attenuated Influenza Virus on Peripheral Blood Natural Killer Cells: A Randomized, Double-Blind Study

[6] 2020 https://pubchem.ncbi.nlm.nih.gov/compound/sulforaphane lists sulforaphane’s molecular weight as 177.3 g / mol. A 1 mg weight of sulforaphane equals a 5.64 μmol sulforaphane amount (.001 / 177.3).

[7] 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease

[8] 2019 Broccoli or Sulforaphane: Is It the Source or Dose That Matters? Note that a coauthor didn’t disclose their business’ conflict of interest for an effectively promoted commercial product.

How much sulforaphane is suitable for healthy people?

This post compares and contrasts two perspectives on how much sulforaphane is suitable for healthy people. One perspective was an October 2019 review from John Hopkins researchers who specialize in sulforaphane clinical trials:

Broccoli or Sulforaphane: Is It the Source or Dose That Matters?

These researchers didn’t give a consumer-practical answer, so I’ve presented a concurrent commercial perspective to the same body of evidence via an October 2019 review from the Australian founder of a company that offers sulforaphane products:

Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease


1. Taste from a clinical trial perspective:

“Harsh taste (a.k.a. back-of-the-throat burning sensation) that is noticed by most people who consume higher doses of sulforaphane, must be acknowledged and anticipated by investigators. This is particularly so at higher limits of dosing with sulforaphane, and not so much of a concern when dosing with glucoraphanin, or even with glucoraphanin-plus-myrosinase.

Presence and/or enzymatic production of levels of sulforaphane in oral doses ranging above about 100 µmol, creates a burning taste that most consumers notice in the back of their throats rather than on the tongue. Higher doses of sulforaphane lead to an increased number of adverse event reports, primarily nausea, heartburn, or other gastrointestinal discomfort.”

Taste wasn’t mentioned in the commercial review. Adverse effects were mentioned in this context:

“Because SFN is derived from a commonly consumed vegetable, it is generally considered to lack adverse effects; safety of broccoli sprouts has been confirmed. However, use of a phytochemical in chemoprevention engages very different biochemical processes when using the same molecule in chemotherapy; biochemical behaviour of cancer cells and normal cells is very different.”

2. Commercial products from a clinical trial perspective:

“Using a dietary supplement formulation of glucoraphanin plus myrosinase (Avmacol®) in tablet form, we observed a median 20% bioavailability with greatly dampened inter-individual variability. Fahey et al. have observed approximately 35% bioavailability with this supplement in a different population.”

Avmacol appeared to be the John Hopkins product of choice, as it was mentioned 15 times in its clinical trials table. A further investigation of Avmacol showed that its supplier for broccoli extract, TrueBroc, was cofounded by a John Hopkins coauthor! Yet the review stated:

“The authors declare no conflict of interest.”

Please disclose easily discoverable ethical and commercial conflicts without prevarication. Other products were downgraded with statements such as:

“5 or 10 g/d of BroccoPhane powder (BSP), reported to be rich in SF, daily x 4 wks (we have assayed previously and found this not to be the case).”

They also disclaimed:

“We have indicated clinical studies in which label results have been used rather than making dose measurements prior to or during intervention.”

No commercial products – not even the author’s own company’s – were directly mentioned in a commercial perspective.

3. Dosage from a clinical trial perspective:

“Reporting of administered dose of glucoraphanin and/or sulforaphane is a poor measure of the bioavailable / bioactive dose of sulforaphane. As a consequence, we propose that the excreted amount of sulforaphane metabolites (sulforaphane + sulforaphane cysteine-glycine + sulforaphane cysteine + sulforaphane N-acetylcysteine) in urine over 24 h (2–3 half-lives), which is a measure of “internal dose”, provides a more revealing and likely consistent view of delivery of sulforaphane to study participants.

Only recently have there been attempts to define minimally effective doses in humans – an outcome made possible by development of consistently formulated, stable, bioavailable broccoli-derived preparations.”

Dosage from a commercial perspective:

“Of available SFN clinical trials associated with genes induced via Nrf2 activation, many demonstrate a linear dose-response. More recently, it has become apparent that SFN can behave hormetically with different effects responsive to different doses. This is in addition to its varying effects on different cell types and consequent to widely varying intracellular concentrations.

A 2017 clinical pilot study examined the effect of an oral dose of 100 μmol (17.3 mg) encapsulated SFN on GSH [reduced glutathione] induction in humans over 7 days. Pre- and postmeasurement of GSH in blood cells that included T cells, B cells, and NK cells showed an increase of 32%. Researchers found that in the pilot group of nine participants, age, sex, and race did not influence the outcome.

Clinical outcomes are achievable in conditions such as asthma with daily SFN doses of around 18 mg daily and from 27 to 40 mg in type 2 diabetes. The daily SFN dose found to achieve beneficial outcomes in most of the available clinical trials is around 20-40 mg.”

The author’s sulforaphane products are available in 100, 250, and 700 mg capsules of enzyme-active broccoli sprout powder.

4. Let’s see how these perspectives treated a 2018 Spanish clinical trial published as Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects.

From a commercial perspective:

“In a recent study using 30 grams of fresh broccoli sprouts incorporated daily into diet, two key inflammatory cytokines were measured at four time points in forty healthy overweight [BMI 24.9 – 29.9] people. Levels of both interleukin-6 (Il-6) and C-reactive protein (CRP) declined over the 70 days during which sprouts were ingested.

These biomarkers were measured again at day 90, wherein it was found that Il-6 continued to decline, whereas CRP climbed again. When the final measurement was taken at day 160, CRP, although climbing, had not returned to its baseline value. Il-6 remained significantly below baseline level at day 160.

Sprouts contained approximately 51 mg (117 μmol) GRN [glucoraphanin], and plasma and urinary SFN metabolites were measured to confirm that SFN had been produced when sprouts were ingested.”


From a clinical trial perspective, glucoraphanin dosage was “1.67 (GR) μmol/kg BW.” This wasn’t accurate, however. It was assumed into existence by:

“In cases where authors did not indicate dosage in μmol/kg body weight (BW), we have made those calculations using a priori assumption of a 70 kg BW.”

117 μmol / 1.67 μmol/kg = 70 kg.

This study provided overweight subjects’ mean weight in its Table 1 as “85.8 ± 16.7 kg.” So its actual average glucoraphanin dosage per kg body weight was 117 μmol / 85.8 kg = 1.36 μmol/kg. Was making an accurate calculation too difficult?

A clinical trial perspective included this study in Section “3.2. Clinical Studies with Broccoli-Based Preparations: Efficacy” subsection “3.2.8. Diabetes, Metabolic Syndrome, and Related Disorders.” This was somewhat misleading, as it was grouped with studies such as a 2012 Iranian Effects of broccoli sprout with high sulforaphane concentration on inflammatory markers in type 2 diabetic patients: A randomized double-blind placebo-controlled clinical trial (not freely available).

A commercial perspective pointed out substantial differences between these two studies:

“Where the study described above by Lopez-Chillon et al. investigated healthy overweight people to assess effects of SFN-yielding broccoli sprout homogenate on biomarkers of inflammation, Mirmiran et al. in 2012 had used a SFN-yielding supplement in T2DM patients. Although the data are not directly comparable, the latter study using the powdered supplement resulted in significant lowering of Il-6, hs-CRP, and TNF-α over just 4 weeks.

It is not possible to further compare the two studies due to vastly different time periods over which each was conducted.”


The commercial perspective impressed as more balanced than the clinical trial perspective. The clinical trial perspective also had an undisclosed conflict of interest!

A. The clinical trial perspective:

  • Effectively promoted one commercial product whose supplier was associated with a coauthor;
  • Downgraded several other commercial products; and
  • Tried to shift responsibility for the lack of “minimally effective doses in humans” to commercial products with:

    “Only recently have there been attempts to define minimally effective doses in humans – an outcome made possible by the development of consistently formulated, stable, bioavailable broccoli-derived preparations.”

But unless four years previous is “recently,” using commercial products to excuse slow research progress can be dismissed. A coauthor of the clinical trial perspective was John Hopkins’ lead researcher for a November 2015 Sulforaphane Bioavailability from Glucoraphanin-Rich Broccoli: Control by Active Endogenous Myrosinase, which commended “high quality, commercially available broccoli supplements” per:

“We have now discontinued making BSE [broccoli sprout extract], because there are several high quality, commercially available broccoli supplements on the market.”

The commercial perspective didn’t specifically mention any commercial products.

B. The commercial perspective didn’t address taste, which may be a consumer acceptance problem.

C. The commercial perspective provided practical dosage recommendations, reflecting their consumer orientation. These recommendations didn’t address how much sulforaphane is suitable for healthy people, though.

The clinical trial perspective will eventually have to make practical dosage recommendations after they stop dodging their audience – which includes clinicians trying to apply clinical trial data – with unhelpful statements such as:

“Reporting of administered dose of glucoraphanin and/or sulforaphane is a poor measure of the bioavailable / bioactive dose of sulforaphane.”

How practical was their “internal dose” recommendation for non-researcher readers?


Here’s what I’m doing to answer how much sulforaphane is suitable for healthy people.

I’d like to posthumously credit my high school literature teachers Dorothy Jasiecki and Martin Obrentz for this post’s compare-and-contrast approach. They both required their students to read at least two books monthly, then minimally handwrite a 3-page (single-spaced) paper comparing and contrasting those books.

Each monthly assignment was individualized so that students couldn’t undo the assignment’s purpose – to think for yourself – with parasitical collaboration. This former practice remains a good measure of intentional dumbing-down of young people, the intent of which has become clearer.

You can see from these linked testimonials that their approach was in a bygone era, back when some teachers considered a desired outcome of public education to be that each individual learned to think for themself. My younger brother contributed:

“I can still remember everything Mr. Obrentz ever assigned for me to read. He was the epitome of what a teacher should be.”

Microwave broccoli to increase sulforaphane levels

This 2020 Chinese/USDA study investigated effects on sulforaphane amount from heating broccoli in water and microwaving at different power settings to different temperatures:

“Microwave treatment causes a sudden collapse of cell structure due to the increase in osmotic pressure difference over vacuole membrane. Mild heating could increase SFR [sulforaphane] level, possibly explained by the increased activity of MYR [the enzyme myrosinase] which can hydrolyze GLR [glucoraphanin] into SFR at high temperature (up to 60°C).

Microwave‐cooked broccoli had higher levels of these two compounds compared to broccoli heated in water. The broccoli sample without cooking as a control showed the least amount of GLR, indicating that microwave heating did help to release more GLR from the cell.

In the temperature range of 50–60°C, a positive correlation was observed between GLR or SFR contents and temperature. However, these two physiochemical contents were negatively correlated with temperature when it increased to 70°C.

The glucoraphanin (GLR) and sulforaphane (SFR) contents (μmol/g DW) in florets of broccoli during microwaving at 40, 50, 60, and 70°C using low power level (LL) or high power level (HL). Data are reported as the mean ± SD (n = 3). Values with different letters are significantly (p < .05) different.

[For example, sulforaphane levels of the control (raw), LL40, LL70, and HL40 conditions weren’t significantly different, and the HL70 level was significantly lower than those levels]. The microwave using high level at 60°C showed the greatest SFR level (2.45 µmol/g DW).”

Table S1 from the supporting material:

Temperature

(°C)

Time

(S)

Power level

(W)

Heating in water 40 185 NA
50 230
60 262
70 290
Microwave (HL) 40 65 950
50 90
60 108
70 120
Microwave (LL) 40 115 475
50 148
60 178
70 200

https://onlinelibrary.wiley.com/doi/10.1002/fsn3.1493 “Microwave cooking increases sulforaphane level in broccoli”


The researchers demonstrated a more effective method of increasing sulforaphane than did the cited and widely discussed 2004 Heating decreases epithiospecifier protein activity and increases sulforaphane formation in broccoli (not freely available). The older study methods were difficult to implement in kitchens, and evaluated heating temperature as the only factor.

The present study added microwave power level irradiation effects as a factor, and simplified heating temperature implementation. People can use Table S1 to maximize broccoli floret sulforaphane content in their kitchens. See Week 2 of Changing an inflammatory phenotype with broccoli sprouts for changes.

The study provided an optimal sulforaphane end result of “(2.45 µmol/g DW)”. I asked a study author for additional data, and they replied:

“The control GLR and SLR amount was 2.18 and 0.22 µmol/g DW, respectively, while the HL60 GLR amount was 2.78 µmol/g DW.”

Microwaving 10 grams of broccoli florets to 60°C (140°F) increased the sulforaphane amount by 1,114% (2.45 / .22)! That also increased the glucoraphanin amount by 27% (2.78 / 2.18) for further processing into sulforaphane after eating.

I replied: That’s an exciting result, increasing sulforaphane more than 11 times, while also increasing glucoraphanin! I haven’t found similar experiments with broccoli sprouts. Would you expect similar results?

The study author responded:

“We didn’t expect this result, and think microwave irradiation might help to release more conjugated forms of glucosinolates and then get hydrolyzed by released myrosinase. Further studies are being carried out.”


The study also measured broccoli stems:

“GLR and SFR were hardly detected in stems. Less than 52% of GLR was detected in the [50/50] mixture of florets and stems compared to florets.

Microwaved at 60°C, the florets had a concentration of GLR and SFR at 2.78 and 2.45 µmol/g DW, respectively, which was significantly higher than the levels detected in mixture of florets and stems (1.21 and 0.82 µmol/g DW, respectively).”

The 50% florets / 50% stems mixture’s glucoraphanin amount of 1.21 µmol was roughly comparable with the 1.08 µmol glucoraphanin amount of mature broccoli extract in item 2 below.

Reminders from Eat broccoli sprouts today:

  1. A 1 mg sulforaphane weight equals a 5.64 μmol sulforaphane amount.
  2. “Content of glucoraphanin in extract from broccoli sprouts was 16.6 μmol per gram of fresh weight. In contrast, mature broccoli extract contained 1.08 μmol per gram of fresh weight.”
  3. The bioavailability of sulforaphane in a broccoli sprout extract with the myrosinase enzyme 100 μmol gelcap was 36.1% which weighed 6.4 mg.
  4. The question of how much sulforaphane is suitable for healthy people remains unanswered.

Eat broccoli sprouts today!

This 2020 Korean letter to a journal editor cited 23 recent papers in support of sulforaphane’s positive effects, mainly in anti-cancer treatments:

“Gene expression is mediated by chromatin epigenetic changes, including DNA methylation, histone modifications, promoter-enhancer interactions, and non-coding RNA (microRNA and long non-coding RNA)-mediated regulation. Approximately 50% of all tumor suppressor genes are inactivated through epigenetic modifications, rather than by genetic mechanisms, in sporadic cancers. Accumulating evidence suggests that epigenetic modulators are important tools to improve the efficacy of disease prevention strategies.

Because sulforaphane (SFN) induces the nuclear factor erythroid 2-related factor 2 (Nrf2)-antioxidant response element pathway that induces the cellular defense against oxidative stress, SFN has received increased attention because it acts as an antioxidant, antimicrobial, anti-inflammatory, and anticancer agent.”

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7068201/ “A recent overview on sulforaphane as a dietary epigenetic modulator”


Letters to the editor aren’t peer-reviewed, though. One of the cited papers was a 2018 Czech mini-review that included metabolism, preparation and processing evidence:

“Sulforaphane is a phytochemical that occurs in plants in the form of biological inactive precursor glucoraphanin. This precursor belongs to the group of phytochemicals – glucosinolates – that are rapidly converted to isothiocyanate by the enzyme myrosinase.

The process of transformation takes place after a disruption of plant tissues by biting, chewing, slicing, and other destruction of tissues, when myrosinase is released from plant tissues. When myrosinase is destroyed during meal preparation (during cooking, steam cooking, or microwave treatment), a likely source of isothiocyanates is microbial degradation of glucosinolates by intestinal microflora. However, hydrolysis by microflora has been reported to be not very efficient, and in humans it is very diverse and variable.

Content of glucoraphanin in extract from broccoli sprouts was 16.6 μmol per gram of fresh weight. In contrast, mature broccoli extract contained 1.08 μmol per gram of fresh weight. Total amount of glucosinolates in young broccoli sprouts is 22.7 μmol per gram of fresh weight and 3.37 μmol per gram of fresh weight for mature broccoli.

Percentage amount of sulforaphane formed from its precursor glucoraphanin in broccoli which had not been heat treated and had been lyophilized [freeze-dried] was 22.8%. Broccoli steaming (5 min) and its lyophilization decrease the amount of sulforaphane formed to 4.2%.”

https://www.liebertpub.com/doi/full/10.1089/jmf.2018.0024 “Isothiocyanate from Broccoli, Sulforaphane, and Its Properties (not freely available)


Information about 43 completed sulforaphane clinical trials is here. Among them, the 2014 Effect of Broccoli Sprouts on Nasal Response to Live Attenuated Influenza Virus in Smokers: A Randomized, Double-Blind Study was of particular interest, stating:

“Nutritional interventions aimed at boosting antioxidants may be most effective in individuals who are relatively antioxidant-deficient at baseline, a condition likely to be more prevalent in smokers.”

I didn’t notice regular supplement dosage studies. Maybe I didn’t read control group information carefully enough?


https://pubchem.ncbi.nlm.nih.gov/compound/sulforaphane lists sulforaphane’s molecular weight as 177.3 g/mol. A 1 mg sulforaphane capsule weight equals a 5.64 μmol sulforaphane amount (.001 / 177.3).

From the 2015 Sulforaphane Bioavailability from Glucoraphanin-Rich Broccoli: Control by Active Endogenous Myrosinase:

  • Figure 4 showed bioavailability of sulforaphane in a broccoli sprout extract with myrosinase 100 μmol gelcap was 36.1% which weighed 6.4 mg (36.1 / 5.64).
  • Figure 3 showed bioavailability of sulforaphane in freeze-dried broccoli sprouts in pineapple-lime juice was 40.5% in 50, 100, and 200 μmol amounts and 33.8% with 100 μmol gel caps. You do the weight math.
  • Figure 2 showed that if broccoli sprout extract didn’t have the enzyme, bioavailability of sulforaphane was 10.4% whether the amount was 69 or 230 μmol, weighing 1.27 mg (69 x .104) / 5.64 and 4.24 mg (230 x .104) / 5.64.

Bioavailability ranged from Figure 2’s 10.4% to Figure 4’s 36.1%. The question of how much sulforaphane is suitable for healthy people remains unanswered.


Train your immune system every day!

This 2019 US review subject was β-glucan:

“β-1,3-Glucans (hereafter referred to as glucan) are natural molecules able to significantly improve our health. In human studies, the tested (and suggested) daily dose remains in the range of 100–500 mg for stimulation of the immune system, whereas for a decrease in cholesterol levels a daily dose of 3 g is recommended.

Glucan does not represent essential nutrients, but it might be successfully used not only for:

  • Improvement of immune functions, but also to improve the general quality of life via
  • Improvements of immune status,
  • Lowering cholesterol,
  • Improving blood glucose levels and
  • Reduction of stress.

ClinicalTrials.gov summarizes 177 [now 207 with 110 completed] β-glucan clinical trials, mostly in cancer, gastrointestinal tract therapy, lowering cholesterol and improvements of immune reactions.

The question is not if glucans will move from food supplement to widely accepted drug, but how soon.

Reactions known to be influenced by glucan are represented in white, reactions where glucan has no confirmed effects are shown in black. The first defensive body response to infection results from formation of the anorexia cytokines (IL-1, IL-6, IL-8, and TNF-α).”

https://www.mdpi.com/1420-3049/24/7/1251/htm “Beta Glucan: Supplement or Drug? From Laboratory to Clinical Trials”

The review is also indexed at https://www.betaglucan.org/i-p/ under “Immunomodulator”


I’m curating this review on Day 12 of a self-quarantine after coming back from Milano, Italy, Monday, February 24, 2020. The previous Friday into Saturday I flew to Milano sitting with a group of elderly Italians who were returning from vacation.

On Saturday my traveling companion and I used the Milano rail and crowded subway system to go downtown. On Sunday we used their crowded rail, crowded bus, and crowded ferry systems to visit Como, Bellagio, and Menaggio.

I don’t think we could have mixed in more with people during transits, touristing, and Carnevale celebrations.

IMG_9539

After returning to our hotel Sunday evening, we heard about the coronavirus outbreak south of Milano and the closing of ten towns. We changed flights and departed for the US early Monday morning.

Neither of us have had any signature symptoms of COVID-19 (fever, shortness of breath, dry cough). Our daily diet the past few years included β-glucan from steel-cut oats (~3 g) and from a 1/3, 1/6 yeast cell wall supplement.

Coincidence?

Each of our futures will depend on what we do Now to prepare.

Take responsibility for your one precious life.

Moonrise at sunrise with Venus