Taurine’s effects on healthspan and lifespan, Part 2

Four 2023 papers that cited Part 1, starting with a review of hypothetical parameters for taurine clinical trials that aren’t going to happen because:

  • Drug companies can’t make money from a research area that’s cheap, not patentable, and readily accessible.
  • Government sponsors are likewise not incentivized to act in the public’s interest per their recent behavior.

“We propose the rationale that an adequately powered randomized-controlled-trial (RCT) is needed to confirm whether taurine can meaningfully improve metabolic and microbiome health, and biological age.
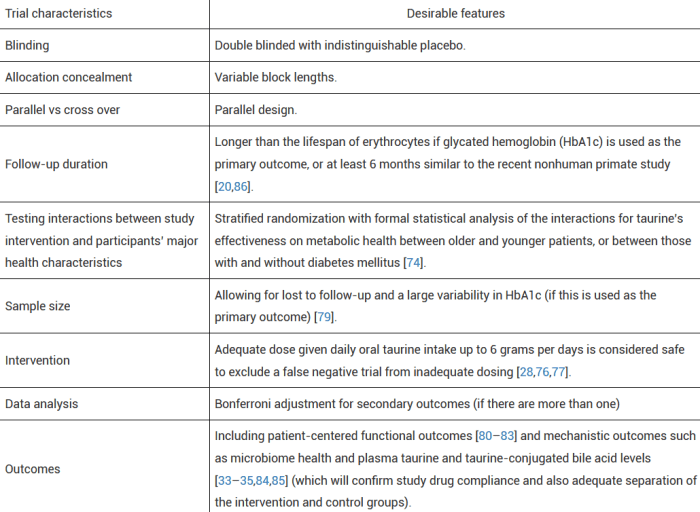
taurine hypothetical trial

Using long-term survival as a primary outcome is desirable but difficult; any demonstrable difference in this outcome will require a substantial sample size with prolonged follow-up (e.g., 5 years or longer) if the effect size is relatively small (or modest at best). Biological age based on DNA methylation biomarkers according to the Levine PhenoAge or newer biological age models is increasingly being recognized as an important dynamic health parameter, and hence it can also be used as a surrogate outcome in assessing benefits of taurine supplementation.

The recent taurine trial on nonhuman primates used an equivalent dose that was between 3 and 6 g per day for an 80-kg person, and this could represent a reasonable dose range for any human RCTs. We believe that a 6-month or longer interventional period matching what was successfully done on nonhuman primates will be an acceptable time frame in assessing potential efficacy of taurine on human metabolic health in a RCT.”

https://www.sciopen.com/article/10.26599/1671-5411.2023.11.004 “Flattening the biological age curve by improving metabolic health: to taurine or not to taurine, that’s the question”

A six-month duration and a 6 grams per day dose were in the above table’s desirable features column, but epigenetic clock measurements weren’t included as an outcome. I’d guess that its omission reflected disagreements among coauthors, because the desirability of using epigenetic clocks as surrogate measures of human healthspan and lifespan was mentioned several times.


Another review:

“As described in the first half of this review, recent advances in omics analysis technology have led to research to detect the causative gene of dilated cardiomyopathy. It has been found that rare mutations in the taurine transporter gene contribute to the development of dilated cardiomyopathy in humans. It is unlikely that a taurine-deficient diet is a factor in dilated cardiomyopathy, but taurine intake may have positive cardiovascular effects.

The second half summarizes the relationship between taurine and healthspan and lifespan. It is difficult to summarize the effect of age in whole body taurine content, which may vary in species, strain, sex, and age of animal models. Future human studies will clarify the relationship between dietary taurine intake and healthy life expectancy.”

https://www.sciencedirect.com/science/article/pii/S1347861323000749 “Taurine deficiency associated with dilated cardiomyopathy and aging”


A human study investigated brain chemicals that fluctuate with our circadian rhythm:

“We conducted a MRS study at 7 T, where occipital NAD content, lactate, and other metabolites were assessed in two different morning and afternoon diurnal states in healthy participants. Salivary cortisol levels were determined to confirm that the experiment was done in two circadian different physiological conditions.

Although no significant differences in NAD+, NADH, and NAD+/NADH were detected between the morning and afternoon sessions, there was a significant variance difference in NAD+/NADH, with a higher variance of NAD+/NADH redox ratio in the morning.

None of the over 30 measured brain metabolites were significantly affected by the circadian rhythm (CR) except for taurine, which decreased in the afternoon. Further CR studies should consider the prospective measurement of taurine levels in different regions of the human brain, and explore how taurine supplements could impact brain CR metabolism in health and diseases.”

https://www.frontiersin.org/articles/10.3389/fphys.2023.1285776/full “Effect of circadian rhythm on NAD and other metabolites in human brain”

I omitted findings regarding this study’s pathetic Balloon Analogue Risk Task (BART) test. Older studies that drew spurious findings from this video game include:


A rodent study modeled human childhood cataracts:

“Our analysis identified targets that are required for early normal differentiation steps and altered in cataractous lenses, particularly metabolic pathways involving glutathione and amino acids. Glutathione and taurine were spatially altered, and both taurine and the ratio of reduced glutathione to oxidized glutathione, two indicators of redox status, were differentially compromised in lens biology.

1-s2.0-S2213231723002707-ga1_lrg

Dietary amino acid supplementation has been shown to prevent cataract development, and dietary intake of taurine was protective in a glutathione depletion-derived opacity model. This opens up the possibility that dietary supplementation of taurine could be used as a strategy to prevent human congenital cataracts.

Our findings shed light on molecular mechanisms associated with congenital cataracts, and point out that unbalanced redox status due to reduced levels of taurine and glutathione, metabolites already linked to age-related cataracts, could be a major underlying mechanism behind lens opacities that appear early in life.”

https://www.sciencedirect.com/science/article/pii/S2213231723002707 “Unbalanced redox status network as an early pathological event in congenital cataracts”



PXL_20240103_191340418

Take acetyl-L-carnitine if you are healthy

Eight 2023 acetyl-L-carnitine / L-carnitine papers, starting with three healthy human studies:

“Thirty healthy volunteers aged between 19 and 52 years were divided randomly into two equal groups, one of which received 1000 mg of L-carnitine (LC) per day over a 12-week period. Total cholesterol and HDL-C increased significantly after supplementation. LC could be useful in impeding development of heart diseases in subjects with low HDL-C.”

https://journaljammr.com/index.php/JAMMR/article/view/5166 “L-Carnitine Increases High Density Lipoprotein-Cholesterol in Healthy Individuals: A Randomized Trial”

Rationale for dose selection wasn’t provided, and the possibility of limited results due to poor study design wasn’t mentioned.


“This study examined effects of 12 weeks of LC supplementation on bone mineral density (BMD) and selected blood markers involved in bone metabolism of postmenopausal women participating in a resistance training (RT) program. Participants’ diets were supplemented with either 1 g of LC-L-tartrate and 3 g of leucine per day (LC group) or 4 g of leucine per day as a placebo (PLA group), in a double-blind fashion.

Because the study protocol consisted of both exercise and supplementation, some favorable changes in the BMD could be expected. However, it was not possible to detect them in the short study period. No significant modification in BMDs of the spine, hip, and total skeleton and no differences between groups in one-repetition maximum could be due to the relatively short duration of the RT intervention.”

https://nutritionandmetabolism.biomedcentral.com/articles/10.1186/s12986-023-00752-1 “Effect of a 3-month L-carnitine supplementation and resistance training program on circulating markers and bone mineral density in postmenopausal women: a randomized controlled trial”

Same comments as the first study regarding no rationale for dose selection, and no mention that limited results were possibly due to an inadequate dose.


In a letter to the editor, a researcher took issue with a study’s methodology:

“Based on finding that intravenous provision with carnitine alone does not increase muscle carnitine accretion, and on the above-reevaluated data, it appears that the basis for carnitine with caffeine being able to increase muscle carnitine levels, and thereby manipulation of muscle metabolism and exercise performance, is uncertain.

Carnitine bioavailability in any group would have been 9.5%. This assessment would be in line with previously recorded values of 5%–18% carnitine bioavailability. It is firmly believed that low carnitine bioavailability is attributable to the inability of kidneys to reabsorb carnitine when the threshold concentration for tubular reabsorption (about 40–60 μmol/L) has passed this value.

The authors’ proposed long-term use of carnitine supplementation as an aid to improve fat oxidation in type II diabetes also seems to lack provision.”

https://physoc.onlinelibrary.wiley.com/doi/10.14814/phy2.15736 “LTE: Does caffeine truly raise muscle carnitine in humans?”


Two genetic studies:

“Our findings suggest that humans have lost a gene involved in carnitine biosynthesis. Hydroxytrimethyllysine aldolase (the second enzyme of carnitine biosynthesis) activity of serine hydroxymethyl transferase partially compensates for its function.”

https://www.researchsquare.com/article/rs-3295520/v1 “One substrate-many enzymes virtual screening uncovers missing genes of carnitine biosynthesis in human and mouse”


“Reported prevalence of primary carnitine deficiency (PCD) in the Faroe Islands of 1:300 is the highest in the world. The Faroese PCD patient cohort has been closely monitored and we now report results from a 10-year follow-up study of 139 PCD patients.

PCD is an autosomal recessive disorder that affects the function of organic cation transporter 2 (OCTN2) high-affinity carnitine transporters, that localizes to the cell membrane and transport carnitine actively inside the cell. Without proper functioning OCTN2 carnitine transporters, renal reabsorption of carnitine is impaired, and as a consequence, patients suffering from PCD have low plasma levels of carnitine. This can disturb cellular energy production and cause fatigue, but also in extreme cases lead to cellular dysfunction and severe symptoms of coma and sudden death.

PCD patients seem to adhere well to L-carnitine treatment, even though they have to ingest L-carnitine tablets at least three times a day. Overall mean L-carnitine dosage was 66.3 mg/kg/day.”

https://onlinelibrary.wiley.com/doi/10.1002/jmd2.12383 “Patients with primary carnitine deficiency treated with L-carnitine are alive and doing well—A 10-year follow-up in the Faroe Islands”

The average daily dose is (66.3 mg x 70 kg) = 4,641 mg. A third of this dose would be about 1.5 g.

The first study of Acetyl-L-carnitine dosing also suggested dosing L-carnitine three times a day because of 10-20% bioavailability.


A study with unhealthy humans:

“This retrospective study analyzed medical records of adult patients between March 2007 and April 2019, with presenting complaints of fatigue and lethargy. Acetyl-L-carnitine has physiological functions similar to L-carnitine but has higher bioavailability and antioxidant properties. This study confirmed that a triple combination therapy with γ-linolenic acid, V. vinifera extract, and acetyl-L-carnitine can improve arterial stiffness in patients.

Our study had some limitations:

  1. The study population may not be representative of the entire Korean adult population.
  2. The study did not have a medication-free control group. Instead, the comparison group comprised patients with medication compliance <80%.
  3. Drop-out rate of the triple-combination therapy (46.2%, 147/318) was relatively high, indicating the possibility of bias due to loss to follow-up.
  4. The study did not consider lifestyle factors such as smoking, diet, and physical activity level, which may affect arterial stiffness.
  5. The study did not examine interactions among drugs comprising the combination therapy, although all drugs are known to positively impact blood vessels.”

https://onlinelibrary.wiley.com/doi/10.1111/jch.14708 “Efficacy of γ-linolenic acid, Vitis vinifera extract, and acetyl-L-carnitine combination therapy for improving arterial stiffness in Korean adults: Real-world evidence”

This study’s acetyl-L-carnitine dose was 500 mg three times a day.


Wrapping up with two rodent studies:

“Acetyl L-carnitine (ALCAR) has proved useful in treatment of different types of chronic pain with excellent tolerability. The present work aimed at evaluating the anti-hyperalgesic efficacy of ALCAR in a model of persistent visceral pain associated with colitis.

The acetyl group in the ALCAR molecule can enhance cholinergic signalling by promoting synthesis of neurotransmitter acetylcholine, which plays an important role in both the enteric and central nervous systems. Acetylcholine signalling has significant antinociceptive effects in development of visceral pain, so it has been proposed as a therapeutic target.

ijms-24-14841-g001

ALCAR significantly reduced establishment of visceral hyperalgesia in DNBS-treated animals, though the interventive protocol showed a greater efficacy than the preventive one.

  • The interventive protocol partially reduced colon damage in rats, counteracting enteric glia and spinal astrocyte activation resulting from colitis.
  • The preventive protocol effectively protected enteric neurons from inflammatory insult.

These findings suggest the putative usefulness of ALCAR as a food supplement for patients suffering from inflammatory bowel diseases.”

https://www.mdpi.com/1422-0067/24/19/14841 “Anti-Hyperalgesic Efficacy of Acetyl L-Carnitine (ALCAR) Against Visceral Pain Induced by Colitis: Involvement of Glia in the Enteric and Central Nervous System

This study cited multiple animal studies that found acetyl-L-carnitine was effective for different types of pain. I’ve taken it every day for nineteen years, and haven’t noticed that effect.


“Repetitive mild traumatic brain injuries (rmTBI) may contribute to development of neurodegenerative diseases through secondary injury pathways. Acetyl-L-carnitine (ALC) shows neuroprotection through anti-inflammatory effects, and via regulation of neuronal synaptic plasticity by counteracting post-trauma excitotoxicity. This study aimed to investigate mechanisms implicated in etiology of neurodegeneration in rmTBI mice treated with ALC.

ALC is an endogenously produced carnitine metabolite present in tissue and plasma, and readily crosses the blood brain barrier, unlike its unacetylated form. ALC is also a commonly available nutritional supplement, with a known safety profile, and had been well-studied for its role in aiding β-oxidation of long chain fatty acids in the mitochondria.

While some studies have shown promise for improving clinical and psychometric outcomes in individuals with probable Alzheimer’s disease (AD) and mild cognitive impairment, other studies that included participants with moderate AD progression were less conclusive. It may be that this lack of improvement is related to a therapeutic window of opportunity. Once neurodegenerative mechanisms have commenced, a reversal of these processes is not attainable.

There is currently a lack of evidence for safe therapeutics that can be administered long-term to reduce the risk of individuals developing cognitive and neuropsychological deficits after rmTBIs. Prophylactic ALC treatment in a paradigm of neurotrauma may be a way to maximize its therapeutic potential.

While brain structures display differential vulnerability to insult as evidenced by location specific postimpact disruption of key genes, this study shows correlative mRNA neurodegeneration and functional impairment that was ameliorated by ALC treatment in several key genes. ALC may mitigate damage inflicted in various secondary neurodegenerative cascades – confirmed by improvements in behavioral and cognitive function – and contribute to functional protection following rmTBI.”

https://www.frontiersin.org/articles/10.3389/fphar.2023.1254382/full “Repetitive mild traumatic brain injury-induced neurodegeneration and inflammation is attenuated by acetyl-L-carnitine in a preclinical model”

I read many traumatic brain injury papers earlier this year, but only curated two in Brain endothelial cells. I came away thinking that there’s no permanent recovery from TBIs, as just symptoms are effectively treated.

Most TBIs happen to old people who have diminished brain reserves. I didn’t see studies that factored in evidence of what happened earlier in injured people’s lives that created TBI susceptibility but wasn’t remembered.

Unlike other years, I haven’t watched any football this season. It’s unsettling that transient entertainment value continues to take precedence over permanent effects on players’ lives.


PXL_20231223_175628957

Building your plasmalogen savings account

A webinar from earlier this week with Dr. Goodenowe, a clinical trial facilitator, and a physician:

From the Q&A segment:

“Is there a particular age where it’s recommended to test for plasmalogen levels? And what levels would be considered normal?

That’s a good question. That actually raises this whole concept of optimal health and this concept of aging.

The best way to think about it – we talked about this paycheck-to-paycheck situation, where as long as our bills are paid every day, technically we think we’re normal. But we still feel this sense of health anxiety – if you will – like we just don’t know if my car breaks down, or my water heater breaks down, do I have enough money to pay these events in my life?

That’s what health feels like to a lot of people, because they’re just kind of getting by. From a health perspective, they’re considered normal, but they have no reserve capacity, and they have no vitality in terms of health.

Plasmalogens are a type of molecule that you build a savings account of, over years, over decades. Your heart builds them up, your brain builds them up, and you slowly accumulate them. Then when you get an oxidative stress like what’s happening now in today’s world with all the covid and myocarditis and brain fog – a lot of these things are being caused because that reserve of plasmalogens has been depleted.

We want plasmalogens for a longevity perspective. There are other situations that can have low plasmalogens, other things can really knock your plasmalogens down.

So you want to start early, you want to build a savings account, and you want to maintain it. Maintain health and function, and create a sustained surplus for optimal health, for optimal neuromuscular performance.”


PXL_20231207_185012059

Another reason to chew broccoli sprouts

This 2023 review explored a naturally produced antimicrobial:

“This review focuses on the role of abundant hypothiocyanous acid (HOSCN), a potent oxidant that kills bacteria but is non-toxic to human cells. Produced from thiocyanate (SCN) and hydrogen peroxide (H2O2) in a variety of body sites by peroxidase enzymes, HOSCN has been explored as an agent of food preservation, pathogen killing, and even improved toothpaste.

Lactoperoxidase (LPO) is considered the main producer of HOSCN, and is secreted in saliva, tears, breastmilk, and lacrima of mammals. LPO regulates the oral microbiome and keeps breastmilk free of pathogens during the first few weeks after delivery. LPO has long been understood to play a role in prevention of dental caries.

Thiocyanate is mostly acquired from diet. Many food plants contain glucosinolates – precursors to isothiocyanates – found in vegetables of order Brassicales (broccoli, cabbages, turnips, mustard, horseradish, etc.).

HOSCN is likely to exist at substantial concentrations in the oral cavity and the respiratory tract, and is probably present under any inflammatory circumstances. Oxidative damage caused by HOSCN is largely reversible, since HOSCN cannot oxidize thiols to sulfinic or sulfonic acid.

mmi15025-fig-0002-m

The study of bacterial HOSCN stress response is in its infancy. Results summarized above suggest overlaps with both ROS and RCS responses, particularly in the areas of redox homeostasis (e.g., glutathione metabolism), cysteine metabolism, and prevention of protein aggregation, but considerable work needs to be done to more fully characterize this response.”

https://onlinelibrary.wiley.com/doi/10.1111/mmi.15025 “Hypothiocyanite and host–microbe interactions”


PXL_20231130_190421232.MP

What is the health utility of white blood cell type count ratios?

This post explores CBC ratios of neutrophils-to-lymphocytes (NLR) and lymphocytes-to-monocytes (LMR) as healthy biomarkers.

Uses of the neutrophils-to-lymphocytes ratio asserted:

A normal range of NLR is between 1–2, and values higher than 3.0 and below 0.7 in adults are pathological.

I saw only one study out of 151 references, reference 61 from 2017, that demonstrated a “below 0.7” range. All of its sampled subjects had sepsis or septic shock, though. Not exactly people from which to derive healthy parameters for the general population.

I looked through all 2023 papers of the 223 papers that cited this review. I didn’t see any that questioned a healthy status of a low neutrophils-to-lymphocytes ratio in humans. Almost all 2023 papers focused on diseases, not health, as if that’s what we want from researchers and medical professionals.

So if a review gets enough citations, its assertions become a fait accompli, elevated to an indisputable fact. Nevermind that unlike study researchers, reviewers aren’t bound to demonstrate evidence from tested hypotheses. Citing paper writers also aren’t obligated to actually read and understand what they cite.


I looked at papers that cited any of the four papers in Uses of the lymphocytes-to-monocytes ratio. There were hundreds of citations over the years, but I didn’t see any 2023 papers that related the LMR to health rather than disease.

The reciprocal monocytes-to-lymphocytes ratio may have prognostic value or “association with” other disease conditions. But do patients care about abstract values such as area under the curve?

Are hormone ratios useful in explaining health? Behavior? Neurobiology? Anything? had a similar situation:

“Analysis of individual variables offers more information and a more accurate picture of underlying relationships.”

This paper suggested by analogy that researching treatments to increase lymphocyte and/or decrease monocyte absolute counts rather than change ratios should be emphasized for health.


Labcorp blood tests from earlier this week came back yesterday. I’ll repeat a paragraph from another blog post that illustrates my viewpoint on them:

“Every explanation of those reference ranges, and optimal ranges built from all-cause mortality statistics, requires a suffix “of people who didn’t positively change their healthspan and lifespan.”

  • What value is there in optimizing (pick a measurement) against those outcomes?
  • Why compare my efforts, or results, or any other aspect of my life, to people who didn’t actionably care about their one precious life?”

Relevant white blood cell type counts and ratios from the current and three previous blood tests are:

nlr lmr

I’ve trained my innate immune system every day for the past 19 years with yeast cell wall β-glucan because every disease is connected to the immune system. I also haven’t been sick even one day this decade.

Let’s start with high-specificity C-reactive protein (hsCRP). Bookend values show very low inflammation over the past 2.5 years. Missing and regular CRP <1 values were due to medical professionals ignoring my written instructions.

Next are innate immune system monocytes, counts of which haven’t changed over the past 2.5 years. There have been no viruses, bacteria, fungi, or parasites that survived initial defenses. So monocyte-derived dendritic cell and macrophage activity hasn’t changed.

Next are adaptive immune system lymphocyte (T cells, natural killer cells, and B cells) counts that had a steady 31% increase from 1.6 to 2.1. It would be interesting to see which lymphocyte subtypes responded to the various therapeutic regimes I’ve implemented over these past 2.5 years. But I won’t become a lab rat to find out.

Last are innate immune system neutrophil counts, which our bone marrow makes copious amounts every day to fight infections. Mine have undergone a 43% decrease over the past 2.5 years. My bone marrow apparently doesn’t have metabolic imperatives to produce more short-lived neutrophils, probably because there isn’t a health emergency to immediately defend against.

To summarize, focusing on white blood cell type counts rather than their ratios better serves health purposes. The CBC test has coarse measures, though, so more refinement could be achieved.


Here’s an epigenetic clock summary of this week’s metabolomic results:

2023 epigenetic age

This summary from 2.5 years ago used the same calculations:

2021 epigenetic age

Maybe the additional 5.6 year difference in this first measurement instead of an opposite 2.5 year change along with chronological age is a signal that I’m getting more healthy. Maybe it’s noise. Recent memories argue against phenotypic age having anywhere near the impact of chronological age.

Comparing my two results against people who didn’t positively change their healthspan and lifespan has limited value, although this could reduce their denominator’s influence. We each have our life at stake, and bad things will happen on their own. If we want good things to happen, we have to make them happen.


PXL_20231127_180605329

A good activity for bad weather days

A free educational series recorded in 2021-2022 available at https://drgoodenowe.com/dr-goodenowes-educational-seminars/ takes the viewer through underlying research and principles of Dr. Goodenowe’s approach to health. It’s advertised as lasting four hours, but took me two days to view.

The series’ discussions and references are background material to better understand later presentations and interviews. Points of interest included:

  • Seminar B100 shows that the metabolomic profile of people who regularly eat broccoli is different than others.
  • B109 clarifies how peroxisomal function is improved through resistance exercise and intermittent fasting.
  • C103 and C104 show how plasmalogens act against neurodegeneration (Parkinson’s disease and multiple sclerosis).

Texts below videos are additional information, not transcripts. C101 text is historically informative.


The B200 ProdromeScan tutorial will take more study. But unlike Labcorp tests, ordering a ProdromeScan requires using a practitioner in Dr. Goodenowe’s network.

I sent the following to Prodrome customer service earlier this month:

Please add me to your approved list for ProdromeScan.

Customer service replied:

“We only add health professionals to an approved list, not individuals.”

I responded:

Good morning. I looked at the websites of doctors who are associated with Dr. Goodenowe who are near me. All of them are too compromised for me to establish a doctor / patient relationship. But I’m glad they left up their blog posts from earlier this decade so I could see who they really were before I reached out to them.

I request an exception to the policy.

Customer service replied:

“There is no exception that can be made to this policy. You need to be a patient of a certified practitioner.”

I’ll escalate my request before my 90-day trial of Prodrome Glia and Neuro products ends so I can get an appropriate metabolomic status. Right now, I won’t involve someone I can’t trust just to know my ProdromeScan information that’s additional to next week’s Labcorp tests.

My treatment-result metabolomic data is probably not mature today on Day 29 of ProdromeGlia and ProdromeNeuro supplementation, resistance exercise, and intermittent fasting. I otherwise wouldn’t have experienced these two events:


I have a quibble with the series’ recommendations for taking N-acetyl cysteine. Relevant views and research:

Switch on your Nrf2 signaling pathway pointed out:

“We use NAC in the lab all the time because it stops an Nrf2 activation. So that weak pro-oxidant signal that activates Nrf2, you switch it off by giving a dose of NAC. It’s a potent antioxidant in that right, but it’s blocking signalling. And that’s what I don’t like about its broad use.”

If someone bombs themself everyday with antioxidants, they’re doing nothing to improve training of their endogenous systems’ defensive functions. What happens when they stop bombing? One example was a 2022 human study that found GlyNAC-induced improvements dissolved back to baseline after supplements stopped.

Also, Precondition your defenses with broccoli sprouts highlighted NAC’s deleterious effects on autophagy and lysosome functions:

“TFEB activity is required for sulforaphane (SFN)-induced protection against both acute oxidant bursts and chronic oxidative stress. SFN-induced TFEB nuclear accumulation was completely blocked by pretreatment of cells by N-acetyl-cysteine (NAC), or by other commonly used antioxidants. NAC also blocked SFN-induced mRNA expression of TFEB target genes, as well as SFN-induced autophagosome formation.”

If a secondary goal of taking NAC per is also necessary for the formation of glutathione, taurine can do that without an antioxidant bomb. Taurine supplementation will free up cysteine to do things other than synthesize taurine, like synthesize glutathione.


PXL_20231123_194849211.MP

Week 189 of Changing to a healthy phenotype with sprouts

1. I started eating 3-day-old microwaved Sango red radish sprouts ten weeks ago, but stopped two weeks ago due to stomach irritation. Earlier this year I tried them for a week using a different microwaving method, and found their glucoraphasatin pungency too much to stomach.

A technique of putting red radish sprouts in a bowl then into a Ziploc bag and using 40% power on my 1000W microwave for 10 seconds tamped their pungency down enough for a while. I use that technique every morning for a 3-day-old microwaved broccoli / red cabbage / mustard sprout mix.

I stopped eating Avena sativa oat sprouts in the evening because they don’t fit into a time-restricted eating regimen of ≤ 8 hours started last month. I still eat 3-day-old Avena sativa oat sprouts begun with 20 grams of hulled grains in the morning along with hulless Avena nuda oats.

I consider Avena nuda oats to be a sprouted grain food. After soaking 18-20 hours, about a quarter of the 82 g starting grains have visible sprouts when I eat them. 91% of Avena nuda oats visibly sprouted given a three-day germination period. So most of the Avena nuda oats that don’t show sprouts after soaking 18-20 hours have already started to germinate.

2. I’ve reduced food intake with TRE, and usually finish eating for the day before 4:00 p.m. This first item was reduced and the others deleted due to volume – too much food within 8 hours:

  • Advanced glycation end products-less chicken vegetable soup stretches for the prep day and three more days instead of two more days.
  • A daily avocado.
  • 85 g hard tofu.
  • 85 g precooked garbanzo / dark red kidney / pinto / black bean mix with untoasted sesame seeds. Will probably restart this the next time TPTB cause empty grocery store shelves.

I changed these two items after my sense of smell and taste improved:

  • I split 283 g of sliced white, crimini, portobello, and shitake mushrooms into the three leftover AGE-less chicken vegetable soup servings rather than into all four servings. Don’t need an umami bomb for prep day soup to taste good.
  • Stopped adding 3 g inulin daily to green tea. Don’t need a sweet taste.

Usually drink three cups of green tea and a cup of aluminum-free coffee before noon.

3. Supplements changed with TRE. Although the ProdromeNeuro loading dose and the 3-day-old broccoli / red cabbage / mustard sprout mix both have about 30-35 calories, I use the later mix as the start of TRE.

When I think an item’s desired results could be antagonized by having other items in the stomach, I’ll take it without eating anything else an hour before or an hour after. I’ll use meal numbers below rather than breakfast / lunch / dinner nomenclature as divisions among them are compressed.

Before Meal 1
– 3.2 g ProdromeNeuro, with nothing else an hour before or after
– 1.5 g yeast cell wall β-glucan (Glucan 300), with nothing else an hour before or after

Meal 1
– 3-day-old microwaved broccoli / red cabbage / mustard sprouts started from 10.7 g of seeds, with nothing else an hour before or after

Meals 2, 3, and 4
– 5 g total taurine
– 3.75 g total glucosamine hydroxychloride / 3 g total chondroitin sulfate, Kirkland Signature
– 3 g total acetyl-L-carnitine, Now
– 1.8 g total chondroitin sulfate, Now
– Hyaluronic acid, Nature’s Lab, 1 serving total
– 9 mg total boron, Swanson Triple Boron Complex

Meals 2 and 4
– Balance oil (total 1400 mg linoleic acid / 350 mg linolenic acid)
– 3 g total betaine anhydrous (TMG), Now
– 2 g total arginine alpha-ketoglutarate, Swanson

Meal 2 only
– Minerals and vitamins (RDA mainly), Kirkland Signature Daily Multi
– 25 mcg D3

Meal 3 only
– 56.7 g desalted capers
– 28.35 g walnuts
– 5 g creatine
– 600 mcg Vitamin K2 MK-7, Now

Meal 4 only
– 1.2 g lecithin, Now
– 30 mg zinc monomethionine / 0.3 mg copper, Now
– 25 mg lutein / 5 mg zeaxanthin
– 50 mcg D3

After Meal 4
– 3.2 g ProdromeGlia, with nothing else an hour before or after

4. I’ll get blood tests next week without involving medical professionals other than Labcorp employees. I’ll compare results to a May 2023 annual physical done in the week I started retirement to see whether I’ve changed my phenotype to be more healthy during these less-stressful past six months.


PXL_20231123_203116268

Eat broccoli sprouts to inhibit brain cancer

This 2023 rodent study by Our model clinical trial group investigated effects of broccoli seeds, 8-day-old sprouts, 95-day-old florets, and pure sulforaphane on glioma:

“This study employs a C6 rat glioma model to assess chemoprotective potential of aqueous extracts from broccoli seeds, sprouts, and inflorescences, all rich in sulforaphane (SFN), and pure SFN as positive control.

In plant material, seeds and sprouts exhibited a heightened concentration of aliphatic-type glucosinolates (GSLs), while broccoli heads showcased a more substantial amount of indole group GSLs. Similar to the GSL trend, the highest concentration of phenolic compounds was evident in sprouts, succeeded by seeds, with broccoli heads exhibiting a subsequent lower content.

seed-sprout-inflorescence

Within freeze-dried aqueous extracts obtained from plant material samples, seeds exhibited the most substantial SFN content, trailed by sprouts and inflorescences. This hierarchy aligns with precursor GSL content, specifically glucoraphanin (GRA). These outcomes imply that approximately 5% of GRA content converted into SFN.

Sinapic acid derivatives emerged as the primary category of phenolic compounds. Higher concentrations of these phenolic compounds were observed in inflorescences, succeeded by seeds, and lastly, broccoli sprouts.

sfn phenolics

Aqueous extracts from seeds, sprouts, and inflorescences were administered to rats over 30 days before the introduction of C6-glioma cells. This specific time frame corresponds to a critical risk factor and initiation of the tumor niche in humans. The objective was to assess whether this consumption could protect against tumor development.

Tumor volume within the control SS group significantly increased compared to the sprout group. Volume fluctuations observed in the seed and inflorescence groups did not demonstrate any statistically significant differences when compared to the control group.

1-s2.0-S0753332223015184-gr2_lrg

Subjects administered with 0.1 mg/kg of SFN displayed a notable decrease in tumor growth. A stark contrast is evident when compared to the corresponding control group (control OO) and the 0.7 mg/kg SFN-treated group.

These findings substantiate the notion that elevated doses of the pure compound might potentially assume a pro-oxidant role, while lower doses hold promise in fostering an environment rich in antioxidants and conducive to chemoprotection.

1-s2.0-S0753332223015184-gr4_lrg

All experimental groups developed gliomas. However, the group administered with aqueous extract of broccoli sprouts and the group treated with pure SFN at 0.1 mg/kg exhibited formation of diffuse low-grade gliomas. Conversely, the remaining groups exhibited malignant characteristics, and manifested development of thrombosed vessels.

Incorporating broccoli sprouts into one’s regular diet emerges as a highly promising strategy for averting onset of specific types of cancer. It is the most cost-effective option for society when contrasted with consumption of nutraceuticals. While achieving a standardized effective dose of SFN via food consumption, such as sprouts, poses challenges, forthcoming clinical studies are poised to determine an appropriate dosage for shaping human intervention trials.”

https://www.sciencedirect.com/science/article/pii/S0753332223015184 “The preventive effects of broccoli bioactives against cancer: Evidence from a validated rat glioma model”


This study’s Discussion section had a lot of hand waving regarding broccoli seeds’ failure to outperform broccoli sprouts despite its 1.06 mg/kg to 0.63 mg/kg sulforaphane advantage. Although not specifically referenced, hormetic effects described in Sulforaphane in the Goldilocks zone and subsequent studies probably account for pure sulforaphane’s dose / response findings that 0.1 mg/kg better inhibited glioma than did 0.7 mg/kg.

For those who think this post’s title is over-the-top:

  • Although eating non-patentable broccoli sprouts is safe and cheap, how many people will wait for clinical trials to determine whether these rodent findings translate to humans?
  • If today there was already human clinical trial evidence confirming translatable findings, how many people would still wait for incorruptible, morally upright, honest, and trusted medical authorities’ approvals?

ray liotta laugh


PXL_20231027_111038664

Plasmalogens, Part 3

The 2022 plasmalogen clinical trial mentioned in Parts 1 and 2 bypassed peroxisome metabolism of cognitively impaired people per discussion of the below diagram:

fcell-10-864842-g003

Increasing the body’s fasting state with time-restricted eating, and preventing muscle atrophy with resistance exercise, were offered as the two most important ways to improve peroxisomal function.

I didn’t find any relevant 2023 human studies (where I could access the full study) on different non-drug treatments that I was willing to do. A 2023 review outlined aspects of peroxisomes, to include a few older human studies:

“Peroxisomes are small, single-membrane-bound organelles, which are dynamic and ubiquitous. Peroxisomes directly interact with other organelles, such as endoplasmic reticulum, mitochondria, or lysosomes. Peroxisomes exert different functions in various cells through both catabolic and anabolic pathways.

The main functions of peroxisomes can be categorized as reactive oxygen species (ROS) metabolism, lipid metabolism, and ether-phospholipid biosynthesis. Peroxisomes also play important roles in inflammatory signaling and the innate immune response.”

1-s2.0-S2667325823001425-gr3_lrg

https://www.sciencedirect.com/science/article/pii/S2667325823001425 “Peroxisome and pexophagy in neurological diseases”


1. Since I haven’t recently tried the two main ways to improve peroxisomal function, I’ll give them a go over the next three months:

  • Expect to get my feeding timeframe to within eight hours. Don’t know about making it short like 6 hours, because my first meal of the day is 35 calories of microwaved cruciferous sprouts, then I wait an hour before eating anything else.
  • Resistance exercise progress should be measurable, as I recorded exercises during the first ten weeks of eating broccoli sprouts every day 3.5+ years ago.

2. Don’t know that I’ll recognize any cognitive improvements to the extent I did during Week 9.

  • I don’t have a young brain anymore, and I’m sure some decline could be measured in memory tests. But I’m not going to become a lab rat.
  • There’s an occasional annoyance that’s been going on for some time, especially when I’m distracted. It happens when I think of something to do, and it somehow becomes a short-term memory that I did it, instead of going into a Things To Do queue. It’s largely self-correcting. For example, regardless of what I paid, I’ll drive back to the grocery store self-checkout to retrieve a third bag that didn’t make it home. A pink-haired employee said young people leave their paid-for groceries behind all the time. It’s usually more of a reality disconnect for me than forgetfulness, because I have a memory that I performed the action. Definitely room for improvement.

3. Don’t know that I’d see biochemical changes such as some described in Part 1. Maybe I’ll move up an annual physical to compare it with the last one in May?

  • I already have very little oxidative stress, very little inflammation, low triglycerides, high HDL, and no major improvements are indicated on CBC / CMP / lipid panels.
  • Take supplements to ensure other things like acetylcholine neurotransmitter availability, one-carbon / methylation metabolism, vitamin / mineral adequacy.

4. I started the two Prodrome plasmalogen precursor supplements (ProdromeGlia and ProdromeNeuro) a week ago, and take their standard doses. My thought is that resultant plasmalogens won’t degrade very much if their primary use isn’t to immediately address oxidative stress and inflammation. That could give these extra plasmalogens a chance to make larger homeostatic contributions in myelin and membrane areas.

I don’t expect any particular effects to manifest. But I’m interested to see if these two areas would be affected:

  • My left ulnar nerve has been giving me problems for over five years, and several resistance exercises aggravate it. I’ve had two nerve continuity tests during that time to confirm. Numbness and pain are intermittent, though.
  • I still take acetaminophen several times a day for other pain.

None of the above treatments are specifically indicated. But if time-restricted feeding and/or extra plasmalogens have an effect on left ulnar or other pain, maybe I’ll be able to make better progress on resistance exercise.

Update #1 11/13/2023

Update #2 11/22/2023

Update #3 12/13/2023 comments

Update #4 1/30/2024

Update #5 3/31/2024

Dietary choline

Two 2023 papers on choline intake, beginning with an analysis of 14323 people:

“Choline is an essential ingredient that is required for many biological processes in the human body, including formation of cell membranes, preservation of liver and kidney function, and production of neurotransmitters. For humans, only a small amount of choline can be endogenously generated through the liver. It is vital to supplement it in the diet to prevent deficiency.

Mean dietary choline intake was 316.5 ± 164.1 mg/d, and incidence of cardiovascular disease (CVD) was 8.8% in study participants.

nutrients-15-04036-g002

New findings of our study are as follow:

  1. In contrast to previous studies, higher dietary choline intake was associated with a lower incidence of CVD, especially incidence of stroke, in this large, nationally representative US population.
  2. The protective role of higher dietary choline intake was accompanied by reduced inflammation and heart rate.
  3. In the subgroup study, higher dietary choline intake – in participants aged ≥60 years, and in participants with BMIs < 30 kg/m2 – was found to be a protective factor for the presence of CVD.

Our results suggest that adequate choline intake acts against CVD, and choline deficiency should be avoided.”

https://www.mdpi.com/2072-6643/15/18/4036 “Association between Dietary Choline Intake and Cardiovascular Diseases: National Health and Nutrition Examination Survey 2011–2016”


A randomized control trial investigated choline intake effects on resistance exercise training:

“Choline plays crucial roles in several physiological processes, such as:

  • Neurotransmission, muscle contraction, and force generation via synthesis of chemical messenger acetylcholine;
  • Lipid transport via lipoprotein synthesis; and
  • Methyl-group metabolism as a precursor to betaine.

It supports cell membrane integrity/function as a precursor to phosphatidylcholine. Choline may also affect muscle responses to exercise via betaine, which is important for gene expression/protein synthesis.

The present study determined effects of different amounts of choline intakes (approximately 50%, 70%, and 120% of Adequate Intake (AI)) on muscle responses to resistance exercise training (RET). Three groups of 50-to-69-year-old healthy adults underwent a 12-week RET program, and submitted >48 diet logs (>4x/week for 12 weeks). Participants were randomly assigned to one of three choline groups in a double-blind manner: zero additional egg yolk (low), one additional egg yolk (medium = med), or three additional egg yolks (high) per day. 

nutrients-15-03874-g003

  • We found that low choline intake (~51% of AI) resulted in diminished strength gains compared to choline intakes of ~68% or ~118% of AI.
  • We observed that a high choline intake (greater than AI) did not provide additional positive effects on RET responses.
  • Together with choline, betaine was independently associated with change (%) in composite strength, suggesting that multiple mechanisms are at work.
  • There was no effect of choline consumption on any blood lipids and lipoproteins, indicating that a moderately low choline intake may not negatively affect blood lipid profiles.
  • Dietary cholesterol did not contribute much to variability of strength gains.

The consistency of about 50% of AI is particularly significant, as much as 40% of the older population is consuming this low level of choline where there are no overt clinical signs of deficiency, and considering potential effects of choline on age-associated loss of muscle function. This research was supported by U.S. Poultry and Egg Association.”

https://www.mdpi.com/2072-6643/15/18/3874 “The Effect of Choline and Resistance Training on Strength and Lean Mass in Older Adults”


For over a decade, I supplemented phosphatidylcholine via a small amount of lecithin every day. I stopped that three years ago when I started supplementing betaine, thinking that I wouldn’t need as much choline oxidized to plentiful betaine.

Don’t have any choline blood tests to indicate whether or not that has been the right decision. It seems like there’s more risk than reward in continuing, though, so I’ll restart 1200 mg lecithin next week at $.07 a day. That provides about the same amount of choline as does one egg.


Rocket launch followed by telemetry plane

PXL_20231027_110928061

Activate Nrf2 to improve arthritis

This 2023 rodent study cited Eat broccoli sprouts for arthritis to test a Nrf2 activator’s effects on rheumatoid arthritis:

“We show that activation of Nrf2 efficiently improves arthritis of SKG mice, which develop T cell-mediated autoimmune arthritis by zymosan A injection. Oral administration of CDDO-Im, a representative chemical inducer of Nrf2, had effects of both prevention and treatment toward arthritis of SKG mice in an Nrf2-dependent manner.

1-s2.0-S0891584923005452-gr9_lrg

We also found that Nrf2 activation through myeloid-cell lineage-specific Keap1 disruption did not achieve significant improvement in arthritis of SKG mice. Systemic Nrf2 activation or Nrf2 activation in other lineage cells including T cells, B cells and fibroblast-like synoviocytes linage cells is important for improvement of rheumatoid arthritis.

We propose that Nrf2 activation is an efficient therapeutic approach for rheumatoid arthritis.”

https://www.sciencedirect.com/science/article/pii/S0891584923005452 “Nrf2 activation improves experimental rheumatoid arthritis”


PXL_20231025_111742952.TS_exported_17109_1698426337632

But their taste

Two 2023 human studies of cruciferous vegetables’ consumer acceptance, starting with five species’ 7-day-old sprouts and 17-day-old microgreens:

“Sensory chemistry of Brassicaceae species is complex, reaching gustatory, olfactory, and pain nerves and receptors. Among organosulfur compounds, glucosinolates, their hydrolysis compounds, and sulfur-volatile compounds are responsible for their taste, aroma, and trigeminal characteristics (mainly, bitter taste, sulfurous aroma, and pungency/spicy sensations, respectively).

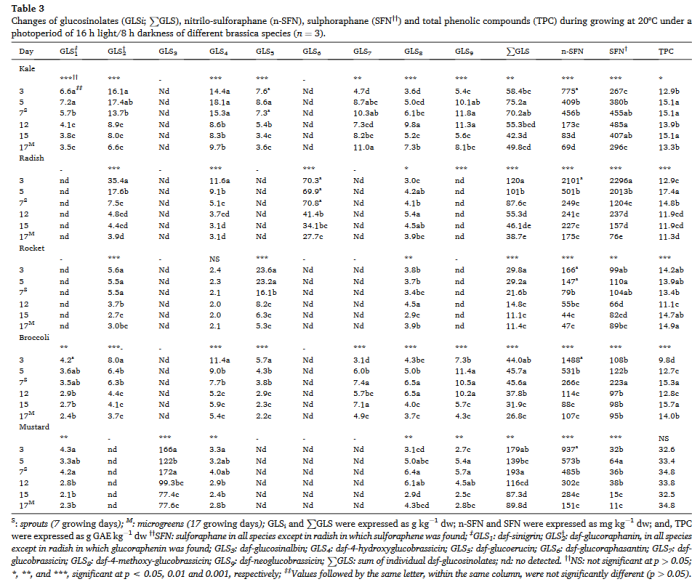
This work compared the sensory profiles and consumer acceptance between (S)prouts vs (M)icrogreens of the same species (kale, radish, rocket, broccoli, and mustard) under the same growing conditions, correlating them with phytochemical composition. On each sampling day (3, 5, 7, 12, 15, and 17 days), S&M were harvested, frozen, and freeze-dried for further analysis.

Previous studies reported the decrease of glucosinolates and sulforaphane from day 4 of germination. Previous studies also indicated that designing crop improvement strategies for sensory traits based on ∑GLS content would be flawed, as it does not consider relative differences in sensory characteristics of different GLSs and isothiocyanates, nor contributions from other GLS hydrolysis products.

table 3

Consumers tested 5 brassica species’ 7-day-old sprouts and 17-day-old microgreens. Each consumer was served ∼ 10 g of each sample coded with 3-digit numbers and the questionnaire. Water and unsalted crackers were provided between samples for palate cleaning.

Consumers were asked to taste each sample, express their overall liking and ‘attribute’ liking using a 9-point hedonic scale (1 = dislike extremely, 5 = neither like nor dislike, and 9 = like extremely). The question ‘How much do you like the ‘attribute’ of this sample?’ was used for global satisfaction/overall, and different attributes (appearance, leaves color, hypocotyl color, size, bitterness, spicy, astringency, herbal-vegetal and ID flavor).

  • Differences among samples depended more on brassica species than growing stage (S&M).
  • In rocket S&M, no attributes were found in the critical corner. RocketS and RocketM were also characterized by the lowest values of ∑GLS. RocketS presented the highest GLS5 glucoerucin content, which does not have bitter taste.
  • Although no differences were found in global, bitterness, and spicy consumer satisfaction degree between S&M of radish and mustard species, penalty analysis indicated a need to improve excess intensity of bitterness and spicy in RadishS and MustardS.

4 out of 5 sprout samples needed improvements, while only 2 out of 5 microgreens samples needed improvements. Sprouts are richer in organosulfur compounds than microgreens, although it depends on the species.

An interesting research line would be to study odor-active compounds of these products and link them with consumer preferences. Other vegetable crops could be included, such as cereals and legumes.”

https://www.sciencedirect.com/science/article/pii/S0925521423001722 “How does the phytochemical composition of sprouts and microgreens from Brassica vegetables affect the sensory profile and consumer acceptability?”


This study treated all conditions to 16 hours light/8 hours darkness throughout. If I wanted naturally developed sprouts at Day 7, I’d follow other studies’ methods and keep germinating seeds in darkness through Day 3 to simulate their natural below-ground conditions, then provide white or blue light after Day 3. So I consider this study’s 7-day-old and 17-day-old sprouts to be both microgreens because they got their leaves at Day 3.

Hadn’t thought of a pain aspect to eating sprouts before reading this study. I’d guess a consumer’s hedonic rating of “dislike extremely” would correspond.

I switched to equal starting weights of broccoli, red cabbage, and mustard seeds 2+ years ago during Week 56 to produce 3-day-old sprouts. That combination takes the edge off individually unpleasant attributes while preserving their beneficial effects.

Couldn’t do that with radish sprouts earlier this year. I might try again if my right thumb doesn’t stop hurting, after I find a tactic that tones down their intensity.


An association analysis of 2129 adults aged 40–80 years found:

“The proportion of participants who ate cruciferous vegetables over two days was 29.5% among bitter tasters, significantly lower than that (35.7%) among non-tasters (P = 0.04) after adjustment of age, gender, race/ethnicity, dietary energy intake, physical activity, education, smoking, and income levels.

cruciferous veg intake and obesity

Bitter taste sensitivity was associated with less consumption of cruciferous vegetables and a high likelihood of obesity, which may mediate its association with diabetes.”

https://pubs.rsc.org/en/content/articlelanding/2023/FO/D3FO02175K “Bitter taste sensitivity, cruciferous vegetable intake, obesity, and diabetes in American adults: a cross-sectional study of NHANES 2013–2014” (not freely available)


PXL_20231007_111348698

Bridging Nrf2 and autophagy

Three more 2023 papers that cited Precondition your defenses with broccoli sprouts, starting with a review:

“Examining crosstalk between Nrf2 antioxidant signaling and autophagy provides insights into how they are interconnected and proteins that mediate their communication. These factors are potential therapeutic targets for diseases with both autophagy dysfunction and oxidative stress.

A working model illustrates mechanisms of bridging factors (SQSTM1, TFEB, Sestrin2, TRIM16, Ca2+, and miRNAs) connecting autophagy (left) and the main antioxidant Nrf2-Keap1-ARE pathway (right) and feedback loops between these factors.

fcell-11-1232241-g003

  • A network forms that connects Nrf2, SQSTM1, TFEB, and mTOR.
  • Other non-canonical autophagy regulatory proteins like Sestrin2 and tripartite motif-containing protein 16 (TRIM16) also participate in regulation of Nrf2 and mTOR via direct or indirect interactions.
  • Ca2+ is the most widespread intracellular messenger whose role in autophagy has been studied extensively.
  • At post-transcriptional level, microRNAs have been reported to impact both the regulation of autophagy and Nrf2 antioxidant signaling.

Since these regulatory proteins seem intricately entangled, potential side effects in practical scenarios should also be taken into consideration. Further studies on understanding the complex crosstalk between autophagy and antioxidant pathways are yet to be conducted.”

https://www.frontiersin.org/articles/10.3389/fcell.2023.1232241/full “An update on the bridging factors connecting autophagy and Nrf2 antioxidant pathway”


A second review subject was improving autophagy:

Lysosomes are crucial degradative organelles that maintain cellular homeostasis. During the pathogenesis of neurodegenerative diseases and aging, functions of lysosomes are impaired, and lysosomal degradative capacity is consequently reduced.

Transcription factor EB-mediated lysosome biogenesis enhances autolysosome-dependent degradation, which subsequently alleviates neurodegenerative diseases. Small-molecule compounds that enhance TFEB activity and lysosome biogenesis are potential therapeutic agents.”

https://journals.lww.com/nrronline/fulltext/2023/11000/enhancement_of_lysosome_biogenesis_as_a_potential.7.aspx “Enhancement of lysosome biogenesis as a potential therapeutic approach for neurodegenerative diseases”


A third review tied mitochondrial participation into these processes:

“Mitochondria play an essential role in neural function, such as supporting normal energy metabolism, regulating reactive oxygen species, buffering physiological calcium loads, and maintaining the balance of morphology, subcellular distribution, and overall health through mitochondrial dynamics. Given recent technological advances in the assessment of mitochondrial structure and functions, mitochondrial dysfunction has been regarded as the early and key pathophysiological mechanism of cognitive disorders.

Mitochondrial dysfunction caused by acute and chronic brain injury is difficult to be distinguished because they may exhibit similar structural and functional impairments. Mitochondrial physiological function and morphology are integral, so when one is damaged, the other is also involved.

We recommend that all of the above methods can be used to explore mitochondrial dysfunction in different pathological pathways of cognitive disorders. Results may be related to special pathological pathways, sensitivity of the method, experiment cost, and degree of proficiency.”

https://journals.lww.com/nrronline/fulltext/2024/04000/latest_assessment_methods_for_mitochondrial.18.aspx “Latest assessment methods for mitochondrial homeostasis in cognitive diseases”


PXL_20231003_110600182

Ergothioneine dosing

Four 2023 papers that outlined or used different ergothioneine doses, starting with a human/rodent study:

“We found that cognitive function and hippocampal neurogenesis were lower in mice fed an ERGO-free diet than in those fed the control diet. Mice fed an ERGO-free diet were orally administered ERGO (0, 2, and 20 mg/kg) for two weeks which reversed these effects.

trkb ratio

Phosphorylated brain-derived neurotrophic factor receptor TrkB, the activated form of TrkB, was also detected in extracellular vesicles (EVs) derived from serum samples of 52 volunteers who had been orally administered ERGO-containing tablets (5 mg/day for 12 weeks). The ratio of serum EV-derived phosphorylated TrkB was significantly higher in the ERGO-treated group than in the placebo-treated group and was positively correlated with both serum ERGO concentrations and several cognitive domain scores from Cognitrax.

cognitrax

The ratio of p-TrkB to TrkB in serum EVs was proposed as a quantitative diagnostic marker of long-term ERGO-induced cognitive improvement.”

https://www.researchsquare.com/article/rs-2626422/v1 “TrkB phosphorylation in serum extracellular vesicles correlates with cognitive function enhanced by ergothioneine in humans”

Human equivalents of all rodent ergothioneine doses were higher than the 5 mg/day for 12 weeks 2020 human study, cited as Reference 21. I couldn’t access that paper, so here’s its Abstract:

Effect of ergothioneine on the cognitive function improvement in healthy volunteers and mild cognitive impairment subjects – a randomized, double-blind, parallel-group comparison study

“These results indicate that continuous intake of ergothioneine improves cognitive function in healthy subjects.”


A rodent study compared effects of a fermented product with 0.1 and 1.0 mg/g (human equivalent 6 mg (1 mg x .081) x  70 kg) ergothioneine doses:

“Our present study demonstrated for the first time the preventive effect of Rice-koji fermented extracts made by Aspergillus oryzae on anxiety, impaired recognition, and nociception using a psychophysically stressed model. Our results also demonstrated preventive effects of ergothioneine (EGT) on stress-induced anxiety- and pain-like behaviors.

Daily administration of High dose Rice-koji or 0.1 mg/kg EGT decreased anxiety- and pain-like behaviors. These findings suggest that inhibitory effects of Rice-koji on psychological stress might be mediated through the actions of EGT.”

https://www.mdpi.com/2072-6643/15/18/3989 “Preventive Roles of Rice-koji Extracts and Ergothioneine on Anxiety- and Pain-like Responses under Psychophysical Stress Conditions in Male Mice”


Here’s one of several reviews that cited a 2017 clinical trial (duplicately Reference 39 and 61 for some reason) of 5 and 25 mg ergothioneine doses:

“In this pharmacokinetic study, forty-five healthy humans received placebo, 5, or 25 mg encapsulated ergothioneine/d for 7 d and were followed up for an additional 4 weeks. Ergothioneine was rapidly absorbed and largely retained by the body, with large increases in plasma ergothioneine levels and only minimal increases (<4 %) in urinary excretion observed. While plasma levels of ergothioneine decreased when supplementation was withdrawn, levels in whole blood continued to increase in a dose–response fashion, reaching maximal levels 3 weeks after withdrawal of supplement, which were sustained at 4 weeks follow-up.

A large difference in basal concentrations of ergothioneine in whole blood was observed. Participants with the highest basal levels of ergothioneine also appeared to take up more of supplemented ergothioneine.”

https://www.cambridge.org/core/journals/british-journal-of-nutrition/article/ergothioneine-an-underrecognised-dietary-micronutrient-required-for-healthy-ageing/92CED7FF201A9FB23BEAFF0D3EAD7316 “Ergothioneine: an underrecognised dietary micronutrient required for healthy ageing?”


Wrapping up with a deep dive into seven mushroom varieties’ compounds:

“Mushrooms contain multiple essential nutrients and health-promoting bioactive compounds, including amino acid L-ergothioneine. We compared metabolomes of fresh raw white button, crimini, portabella, lion’s mane, maitake, oyster, and shiitake mushrooms using untargeted liquid chromatography mass spectrometry (LC/MS)-based metabolomics.

Results indicate significantly higher concentrations of L-ergothioneine in lion’s mane and oyster mushrooms compared to the remaining five mushroom varieties, which had concentrations ranging from 1.94 ± 0.55 to 5.26 ± 1.23 mg/100 g wet weight (mean ± SD). There was also variability in concentration of L-ergothioneine between mushroom varieties of the same farm. Different numbers denote significance (p < 0.05).

foods-12-02985-g008

Mushrooms and their bioactive extracts are considered functional foods. Mushrooms have several bioactive compounds, including polysaccharides, lectins, terpenoids, sterols, and alkaloids, among others, which may positively impact health.

Cell walls of mushrooms contain polysaccharides, including β-glucans and chitin, which positively affect health, through modulating the immune system and protecting the cardiovascular system through improvements in glucose and lipid metabolism. Effects on the cardiovascular system are also attributable to lovastatin and polyphenols, known for their lipid-lowering and antioxidant properties, respectively.

While the 1344 compounds in common among the seven mushroom varieties support some level of similarity, detection of hundreds of unique-to-mushroom-variety compounds and differences in amino acid profiles indicate that not all mushrooms are chemically comparable. Given detection of >400 unique-to-mushroom-variety compounds in lion’s mane, maitake, oyster, and shiitake mushrooms, we suggest further targeted investigations on compounds detected and potential health benefits.”

https://www.mdpi.com/2304-8158/12/16/2985 “Metabolomics Profiling of White Button, Crimini, Portabella, Lion’s Mane, Maitake, Oyster, and Shiitake Mushrooms Using Untargeted Metabolomics and Targeted Amino Acid Analysis”

I eat around 200 grams of mushrooms daily, having temporarily overridden the boredom of eating AGE-less chicken vegetable soup every day. I prep all the top package’s frozen umami bomb (283 grams) and half of the bottom’s fresh mushrooms (340 grams) into the soup:

PXL_20230921_193708552

It makes servings for three days, including one for prep day dinner. I’d guess from “concentrations ranging from 1.94 ± 0.55 to 5.26 ± 1.23 mg/100 g (mean ± SD)” that my daily mushroom ergothioneine dose is around 7 mg ((1.94 mg + 5.26 mg) / 2) = 3.6 mg per 100 grams x 2 (for 200 grams).

Continued in Part 2.

Chondroitin sulfate dosing

Four 2023 papers with different chondroitin sulfate doses, starting with a review:

“This article aims to provide an up-to-date view of current literature regarding biological effects and efficacy of chondroitin sulfate (CS), and discusses the quality of available CS supplements and the current direction in CS investigation.

A meta-analysis published in 2019 concluded that CS had small to moderate effectiveness in reducing osteoarthritis (OA)-related pain, with larger dosages (1200 mg/d) having greater benefits than smaller dosages. This meta-analysis concluded that CS had only a minimal effect on joint space narrowing and no effect on cartilage volume.

Chondroitin sulfate effects on osteoarticular tissues

cs effects on oa

GAG: glycosaminoaglycans; HA: hyalouronic acid; TIMP: tissue inhibitor of metalloproteinase; MMP: metalloproteinase; ROS: reactive oxygen species; RANKL: receptor activator of nuclear factor kappa-Β ligand; JNK: c-Jun N-terminal kinase; PGE2: prostaglandin E2; Erk: extracellular signal-regulated kinases

This review concludes that pharmacologic-grade CS supplements may have clinically significant benefits when properly standardized. However, high-quality evidence from properly designed clinical trials is still needed to draw definitive conclusions about clinical efficacy in OA.”

https://www.cureus.com/articles/162218-chondroitin-sulfate-supplements-for-osteoarthritis-a-critical-review#!/ “Chondroitin Sulfate Supplements for Osteoarthritis: A Critical Review”


A rodent study induced arthritis, then investigated treatment effects of daily glucosamine sulfate (GS, 300 mg), CS (300 mg, a human equivalent dose of 3.4 grams ((300 mg x .162) x 70 kg), and GS+CS = GC combination:

“Rheumatoid arthritis (RA) is an autoimmune disease that affects joints primarily, causing cartilage and bone degeneration as well as functional disability. This study found that both GS and CS could reduce symptoms of RA-related joint inflammation and swelling to some extent, with the effect of GC being more apparent, providing a theoretical foundation for expanding usage of GS and CS.

We discovered that gut bacteria enriched in the RA model were mostly strongly correlative with pro-inflammatory cytokines, right paw volume, and pathological score using correlation analysis. After GS, CS, and GC intervention, these bacteria enriched in the RA model recovered, with GC having the most apparent beneficial impact.

12986_2023_735_Fig1_HTML

Gut microbiota dysbiosis could be recovered before improvement of joint symptoms after intervention. Our findings also indicated that GC might inhibit LPS-producing bacteria and activation of the TLR-4/NF-κB pathway, alleviating RA-induced joint inflammation and ameliorating joint swelling and injury.”

https://nutritionandmetabolism.biomedcentral.com/articles/10.1186/s12986-023-00735-2 “Combined treatment with glucosamine and chondroitin sulfate improves rheumatoid arthritis in rats by regulating the gut microbiota”

A human equivalent of this study’s treatment duration using the maximum lifespan method is (36 days x 32.2) = 1159 days or 38.6 months.


A rodent study worked backwards from a 70 mg/kg daily human CS dose (70 mg x 70 kg = 4.9 grams):

“A female rat model of osteoporosis was established by feeding a low-calcium diet. Intestinal microbiota abundance, fecal and plasma metabolite expression levels of rats fed a basal diet (N), a low-calcium diet (C), a low-calcium diet plus calcium carbonate (Ca), and a low-calcium diet plus chondroitin sulfate (CS) were compared.

Results showed that compared with the low calcium group, calcium content and bone mineral density of femur were significantly increased in the calcium carbonate and chondroitin sulfate groups. In addition to estrogen, low testosterone bioavailability may also be more likely to lead to fracture. Levels of plasma testosterone and stearic content in normal feeding rats were significantly higher than those in the other groups, indicating that plasma testosterone and stearic content in feces of normal feeding rats were decreased due to long-term low calcium levels, and supplementation of calcium and CS could not be recovered.

testosterone

Chronic low-grade inflammation has been identified as the root cause of many diseases, including osteoporosis. We identified bacteria and metabolites behind this change, especially lipid metabolism, and discussed their relevance to bone health.

According to previous studies, as a human therapeutic agent, CS alone has low bioavailability, which is only about 0–13% of total oral intake. This study provides a new strategy to elucidate the molecular mechanism of osteoporosis and to search for potential biomarkers.”

https://nutritionandmetabolism.biomedcentral.com/articles/10.1186/s12986-023-00726-3 “Chondroitin sulfate alleviates osteoporosis caused by calcium deficiency by regulating lipid metabolism”

A human equivalent of this study’s treatment duration is (8 weeks x 32.2) = 257.6 weeks or 5 years.


A rodent study made old female rats out of young female rats by removing their ovaries, then tested different osteoporosis treatment effects:

“In this study, CS oligosaccharides (CSOs) were enzymatically prepared through the lysis of CS by a chondroitinase from Microbacterium sp. strain.

  • 12 weeks’ intragastric administration of Caltrate D (250 mg/kg/d), CS or CSOs (500 mg/kg/d, 250 mg/kg/d, 125 mg/kg/d) could regulate disorder of serum indices, recover mechanical strength and mineral content of bone, improve cortical bones’ density and the number and length of trabecular bones in OVX rats.
  • Both CS and CSOs in 500 mg/kg/d and 250 mg/kg/d could restore more efficiently serum indices, bone fracture deflection and femur Ca than Caltrate D.
  • As compared with CS at the same dosage, CSOs exhibited a more significant alleviating effect. The possible reason might be that the lower molecular weight of CSOs facilitated body absorption and thereafter bioactivity improvement.”

1-s2.0-S0753332223006844-ga1_lrg

https://www.sciencedirect.com/science/article/pii/S0753332223006844 “Enzymatic preparation of chondroitin sulfate oligosaccharides and its alleviating effect on ovariectomy-induced osteoporosis in rats”

A human equivalent of the above-pictured high CS 500 mg daily dose is (500 mg x .162) x 70 kg = 5.7 grams. A human equivalent of this study’s treatment duration is (12 weeks x 32.2) = 386.4 weeks or 7.4 years.


PXL_20230914_105240566.TS_exported_7700_1695054032361