Aging as an unintended consequence

The coauthors of 2018’s The epigenetic clock theory of aging reviewed progress that’s been made todate in understanding epigenetic clock mechanisms.

1. Proven DNA methylation features of epigenetic clocks:

  1. “Methylation of cytosines is undoubtedly a binary event.
  2. The increase in epigenetic age is contributed by changes of methylation profiles in a very small percent of cells in a population.
  3. The clock ticks extremely fast in early post-natal years and much slower after puberty.
  4. Clock CpGs have specific locations in the genome.
  5. It applies to prenatal biological samples and embryonic stem cells.

While consistency with all the five attributes does not guarantee veracity of a model, inconsistency with any one will signal the unlikely validity of a hypothesis.”

2. Regarding what epigenetic clocks don’t measure:

“The effects of

  • Telomere maintenance,
  • Cellular senescence,
  • DNA damage signaling,
  • Terminal differentiation and
  • Cellular proliferation

have all been tested and found to be unrelated to epigenetic ageing.”

3. Regarding cyclical features:

“Both the epigenetic and circadian clocks are present in all cells of the body, but their ticking rates are regulated. Both these clocks lose synchronicity when cells are isolated from tissues and grown in vitro.

These similarities compel one to ponder potential links between them.”

This was among the points that Linear thinking about biological age clocks missed.

4. The reviewers discussed 3 of the 5 treatment elements in Reversal of aging and immunosenescent trends:

“It is not known at this stage whether the rejuvenating effect is mediated through the regeneration of the thymus or a direct effect of the treatment modality on the body. Also, it is not known if the effect is mediated by all three compounds or one or two of them.

What we know at this stage does not allow the formation of general principles regarding the impact of hormones on epigenetic age, but their involvement in development and maintenance of the body argue that they do indeed have a very significant impact on the epigenetic clock.”

Not sure why they omitted 3000 IU vitamin D and 50 mg zinc, especially since:

“It is not known if the effect is mediated by all three [five] compounds or one or two of them.”

5. They touched on the specialty of Aging as a disease researchers with:

“Muscle stem cells isolated from mice were epigenetically much younger independently of the ages of the tissue / animal from which they were derived.

The proliferation and differentiation of muscle stem cells cease upon physical maturation. These activities are initiated in adult muscles only in response to injury.“

6. The reviewers agreed with those researchers in the Conclusion:

“Epigenetic ageing begins from very early moments after the embryonic stem cell stage and continues uninterrupted through the entire lifespan. The significance of this is profound as the question of why we age has been attributed to many different things, most commonly to ‘wear-and-tear.’

The ticking of the epigenetic clock from the embryonic state challenges this perspective and supports the notion that ageing is an unintended consequence of processes that are necessary for

  • The development of the organism and
  • Tissue homeostasis thereafter.”


https://journals.sagepub.com/doi/10.1177/1535370220918329 “Current perspectives on the cellular and molecular features of epigenetic ageing” (not freely available)

Linear thinking about biological age clocks

This 2020 review by a Hong Kong company’s researchers compared and contrasted measures of biological age:

“More than a dozen aging clocks use molecular features to predict an organism’s age, each of them utilizing different data types and training procedures. We offer a detailed comparison of existing mouse and human aging clocks, discuss their technological limitations and the underlying machine learning algorithms. We also discuss promising future directions of research.

Biomarkers placed on an intuitive plane of Accuracy vs Utility. Bubble size depends on the number of clocks based on a corresponding aging biomarker.

Currently, DNAm [DNA methylation] is the most accurate and the most frequently used biomarker in biohorology. However, it is harder to apply a DNAm clock compared to clocks based on clinical blood tests. Moreover, DNAm marks often take a long time to emerge in response to aging interventions.

Chromatin structure and telomeres, while intriguing, are too labor intensive and error-prone to be practical.”

https://www.sciencedirect.com/science/article/pii/S1568163719302582 “Biohorology and biomarkers of aging: current state-of-the-art, challenges and opportunities”


We think about chronological age linearly. The reviewers hinted at but didn’t directly assess the extent to which techniques such as linear regression may also influence people to think linearly about biological age.

We experience cyclical changes every day (like sleep), month, season, and longer periods. The reviewers didn’t mention techniques that incorporate our cyclical experiences or assess cyclical biological age.

1. The reviewers pointed out some biological age clock linearity flaws:

“Most aging clocks base their BA [biological age] definitions either on CA [chronological age] or mortality risk. Mortality risk in its turn is derived from demographic tables and can be assumed to be a function of CA in most animals, including human.

Thus, aging clocks are ultimately treating CA as a substitute BA with the caveat that deviations from the actual CA signify better or worse physical fitness when compared to age matched controls. Such a design has several flaws.”

2. They pointed out non-linear characteristics of chromosomal telomere length:

“DNA lesions caused by oxidative stress are repaired less efficiently in telomeric regions, which causes frailty and subsequent telomere shortening. Oxidative stress levels may fluctuate due to habitat, life style, inflammatory diseases – factors that do not necessarily represent replicative clock ticking.

Telomere length typically fluctuates within ±2-4% per month. This led scientists to hypothesize that telomere attrition is an oscillatory process.”

Since cell components show cyclical phases, why wouldn’t cells and each higher living structural level likewise demonstrate cyclical phases? That avenue wasn’t explored.

3. They mentioned the non-linearity of epigenetic clocks:

“If an organism’s DNAm profile is not directly linked to the thermodynamic root of aging [entropy] but instead is a downstream product of competing processes, the applicability of DNAm aging clock methodology is at risk. In this case different aging clocks may not be equally good for different experiment settings.

While genetic, pharmacological and dietary interventions with proven effect on life expectancy change the methylation state of the age-associated CpG sites, they do so in different ways. Caloric restriction is more efficient in preventing methylation loss at hypomethylated sites and methylation gain at hypermethylated sites than rapamycin.

These findings imply that DNAm profiles do not simply gravitate towards the average with age and that there is no single pathway through which all aging processes are imbued into an organism’s epigenetic landscape.”

4. Genetic and epigenetic regulatory pathways were presented with linear thinking:

“Protein structures encapsulating DNA and regulating its accessibility (chromatin and histones) have also been shown to change with age. Moreover, DNAm machinery and histone modifications are interlinked and change throughout aging concordantly.

For example, DNA methyltransferases are attracted by the H3K36me mark. With aging it is less tightly regulated, and thus, more sporadic DNAm occurs, which ultimately translates to epigenetic clock ticking.”


An individual’s capability to regulate their own aging phenotype wasn’t addressed, only externally applied “aging interventions.” Diseases were considered chronological-“age-associated.”

Biological aging was neither viewed as a disease nor as an unintended consequence. If these researchers don’t grasp the foundations of their field of study, why do they work in the biological aging field? It isn’t just math.

  • Could this paper reflect one company’s desire to frame arguments in favor of the company’s offered solution?
  • Could this paper reflect a “chronological age is the cause” meme that satisfied organizational imperatives for sponsors like the Buck Institute for Research on Aging?
  • Or could it be that the reviewers had other paradigms?

What do you think?

Broccoli sprouts oppose effects of advanced glycation end products (AGEs)

This 2020 Australian/UK review subject was AGEs:

“AGEs are formed during cooking and food processing or produced endogenously as a consequence of metabolism. Deleterious effects of AGEs are underpinned by their ability to trigger mechanisms well known to elicit metabolic dysfunction, including activation of inflammatory pathways, oxidative stress and impaired mitochondrial oxidative metabolism. They have been widely implicated in complications of diabetes affecting cardiovascular health, the nervous system, eyes and kidneys.

Reactive carbonyl groups are constantly being produced via normal metabolism and when production overrides detoxification, AGEs accumulate. AGE formation may take several days or weeks to complete in the body.

Factors affecting AGE content of food depends on composition of protein, fat, and sugar and types of processing and cooking methods employed, predominantly on temperature and duration of preparation. Circulating free-AGEs concentrations are a good marker for dietary AGE intake while plasma protein-bound AGEs better represent endogenously produced AGEs.

Receptor for Advanced glycation end products (RAGE) signals via transcription factor NF-kB increasing gene expression of inflammatory mediators and production of ROS (reactive oxygen species).”

https://onlinelibrary.wiley.com/doi/abs/10.1002/mnfr.201900934 “The Role of Dietary Advanced Glycation End Products (AGEs) in Metabolic Dysfunction” (not freely available)


Let’s use the Australian 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease as a reference for how sulforaphane may counter effects of AGEs:

1. “Activation of inflammatory pathways”

“Antioxidants in general and glutathione in particular can be depleted rapidly under conditions of oxidative stress, and this can signal inflammatory pathways associated with NF-κB. SFN [sulforaphane] has been shown to inhibit NF-κB in endothelial cells.

Two key inflammatory cytokines were measured at four time points in forty healthy overweight people [our model clinical trial, Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects]. Levels of both interleukin-6 (Il-6) and C-reactive protein (CRP) declined over the 70 days during which sprouts were ingested. These biomarkers were measured again at day 90, wherein it was found that Il-6 continued to decline, whereas CRP climbed again. When the final measurement was taken at day 160, CRP, although climbing, had not returned to its baseline value. Il-6 remained significantly below the baseline level at day 160.”

OMCL2019-2716870.010

2. “When production overrides detoxification”

“SFN significantly activates Nrf2 and as such has the potential to modulate the expression of genes associated with redox balance, inflammation, detoxification, and antimicrobial capacity, all key components of the upstream cellular defence processes.

Toxins presented to Phase 1 enzymes produce intermediate compounds which are sometimes more toxic to cells than the initial toxin. It is therefore important that Phase 2 is sufficiently active that intermediate products cannot accumulate in the cellular environment.

As a monofunctional inducer, SFN has been described as an ideal detoxifier, as its effect on Phase 1 is minimal compared with its significant activity on Phase 2.”

3. “Oxidative stress”

“As a mediator for amplification of the mammalian defence system against various stressors, Nrf2 sits at the interface between our prior understanding of oxidative stress and endogenous mechanisms cells use to deal with it. Diseases known to be underpinned by oxidative stress are proving to be more responsive to amplification of cellular defences via Nrf2 activation than by administration of direct-acting antioxidant supplements.

SFN, with absolute bioavailability of around 80%, is capable of increasing several endogenous antioxidant compounds via transcription factor Nrf2.”

4. “Complications of diabetes affecting cardiovascular health, the nervous system, eyes and kidneys”

“Nrf2 is ubiquitously expressed with highest concentrations (in descending order) in the kidney, muscle, lung, heart, liver, and brain. Nrf2 was shown to prevent endothelial cells from exhibiting a proinflammatory state. Nrf2 is required for protection against glucose-induced oxidative stress and cardiomyopathy in the heart.

Well in excess of 500 genes have been identified as being activated by SFN via the Nrf2/ARE [Antioxidant Response Element] pathway, and it is likely that this underestimates the number as others are being discovered. Of available SFN clinical trials associated with genes induced via Nrf2 activation, many demonstrate a linear dose-response. More recently, it has become apparent that SFN can behave hormetically with different effects responsive to different doses.

It [sulforaphane] is not only a potent Nrf2 inducer but also highly bioavailable so that modest practical doses can produce significant clinical responses. Other Nrf2 activators [shown in the above image] not only lack potency but also lack the bioavailability to be considered as significant intracellular Nrf2 activators.”


As mentioned in Changing an inflammatory phenotype with broccoli sprouts, per the above bolded part of section 3, I stopped taking N-acetyl-cysteine, the precursor to our endogenous antioxidant glutathione. I stopped taking curcumin last year due to no noticeable effects, probably because of its poor bioavailability. I may soon stop taking more vitamin E than the RDA, and β-carotene.

I changed my diet last summer to reduce AGEs, with mild effects. I expect stronger effects from also daily eating 60 grams of 3-day-old broccoli sprouts that yield 27 mg of sulforaphane after microwaving.

Reanalysis of findings from a senolytics clinical trial

To follow up Preliminary findings from a senolytics clinical trial:

“The central hypothesis tested in our article is that a brief course of the senolytic drug combination, Dasatinib plus Quercetin (D+Q), can reduce senescent cell abundance in humans, specifically focusing on targeting adipose tissue in subjects with diabetes and kidney dysfunction, a condition in which adipose tissue senescent cell burden is known to be increased.

Although we reported a statistically significant decrease in skin senescent cells in the 9 subjects whose skin data were reported in the original article, that conclusion did not hold up upon reanalysis.

The overall conclusion of our article that D+Q can target senescent cells in humans holds upon reanalysis of the data, at least in adipose tissue and as reflected by a composite of blood SASP [senescence-associated secretory phenotype] factors, but we have not shown this in skin here.”

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6994619/ “Corrigendum to ‘Senolytics decrease senescent cells in humans: Preliminary report from a clinical trial of Dasatinib plus Quercetin in individuals with diabetic kidney disease’”

Reviewing clinical trials of broccoli sprouts and their compounds

This 2020 Spanish review analyzed recent clinical trials that used broccoli sprouts and their compounds. Stringent criteria for study selection resulted in few trials being considered:

  • “We reduced the timeframe to the last years, from 2012 to the present.
  • We focused our work on the data of studies carried out with human adults with different pathologies.
  • Articles [that] did not provide us with specific information about consumption of cruciferous foods or ingredients derived from Brassicaceae products, documents based on healthy volunteers, and patients with pathologies unrelated to our objective of study were also not included in the analysis.”

None of the 15 analyzed clinical trials were unqualified successes. Some of the problems noted were summarized in this critique of the largest study:

“The authors presented the results that there was a risk for T2DM [type 2 diabetes mellitus] with the intake of cruciferous foods and glucosinolates. However, this study presented big limitations because:

  • It did not review or consider the cooking procedures,
  • It did not quantify the amount of vegetables consumed on a daily or weekly basis, and
  • It did not quantify the glucosinolate contents in the different vegetables consumed. Besides,
  • The population sample was homogenous, because all of the participants were health-area workers, and the results are not extrapolatable to the general population. Finally, it should be highlighted that
  • Other nutrients and confounding factors were not considered in the study, and they could affect the development of these pathologies.”

“Figure 1 – General scheme of the glucosinolates (GSLs) and common hydrolysis products. ESP: Epithiospecifer proteins.”

https://www.mdpi.com/1420-3049/25/7/1591/htm “The Role of Brassica Bioactives on Human Health: Are We Studying It the Right Way?”


The reviewers’ answer to the title’s question “Are We Studying It the Right Way?” was NO. The 15 analyzed trials lacked one or more clearly defined measurements related to their target diseases:

“It is crucial that the outcome measure is of biological relevance; biomarkers or risk factors measured must be associated to the latter development of a disease. The degree of progression of the disease greatly influences the response observed.”

So: Why not consider Aging as a disease for clinical trials with broccoli sprouts and their compounds?

  1. “Lack of cure goes hand in hand with inability to accept that this [aging] is disease. It used to be that, please do not diagnose that there’s bacterial meningitis, because there is no cure. Whatever else you can come up with, do it first. Now, diagnose it as fast as possible, so we can put patients on antibiotics immediately. The same will happen to aging.”
  2. Several of the clinical trials’ methodological and statistical problems could be resolved with recognizing aging as a disease. “Healthy” old people who have no other diseases may be scarce, but there are large populations to sample control groups from among healthy and unhealthy young people, and unhealthy old people.
  3. The reviewers already have experience in using “healthy” 46 ± 6 year-old people in a clinical trial of broccoli sprouts and their compounds.
  4. A wide range of epigenetic clocks are available to test the efficacy of broccoli sprouts and their compounds with respect to human aging phenotypes.

As far as I can tell, epigenetic clocks haven’t been used in the subject area thus far! The review’s reference [7] from 2015 didn’t mention them.

Reference [55] was the October 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease, which I’ve been using as the most current and comprehensive of the subject todate. Its references of broccoli sprouts and their compounds with respect to aging included:

“Nrf2 [nuclear factor erythroid 2-related factor 2] transcriptional activity declines with age, leading to age-related GSH [reduced glutathione] loss among other losses associated with Nrf2-activated genes. This effect has implications, too, for decline in vascular function with age. Some of the age-related decline in function can be restored with Nrf2 activation by SFN [sulforaphane].

A potent Nrf2 activator is capable of inducing hundreds of genes simultaneously. Of the phytochemicals with Nrf2 inducer capacity, Brassica-derived SFN is the most potent naturally occurring biomolecule known at this time.”

However, it had only one reference of DNA methylation, the 2015 The Role of Sulforaphane in Epigenetic Mechanisms, Including Interdependence between Histone Modification and DNA Methylation. Even that was a review rather than a study, and it had no mention of epigenetic clocks.

Maybe broccoli sprouts and their compounds’ effects on human aging is an area that just hasn’t drawn attention and funding?

Understanding a clinical trial’s broccoli sprout amount

To follow up Week 2 of Changing an inflammatory phenotype with broccoli sprouts, I contacted the model clinical trial’s corresponding coauthor to clarify a citation. Our correspondence was as follows:

Hello Dr.! Could you further describe Citation 11 of your 2018 clinical study Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects or say where it may be found? “Services, F. a. D. A. F. U. D. o. H. a. H., 2001.” was cited for 30 grams of fresh broccoli sprouts being a half-serving.


Ref. 11. Sulforaphane: translational research from laboratory bench to clinic CA Houghton, RG Fassett, JS Coombes – Nutrition reviews, 2013.

If you check in the table 2, about clinical trials, different studies using broccoli sprouts were establishing daily dosage around 60 g/day (e.g. 56 – 68, etc.). In a similar way, in our previous studies for bioavailability with broccoli sprouts (Domínguez-Perles et al.) we also considered 30 g and 60 g was 1/2 and 1 portion per day, respectively, of broccoli sprouts.

When we carried out tests with consumers, previous to the bioavailability studies (Domínguez-Perles et al., Baenas et al.), higher amounts per day, were not easy to consume and to get eaten by participants. The people or general public in Spain is not very familiar (yet) with these fresh sprouts as may be in USA, or UK, for example. That why we took a “realistic” amount of broccoli sprouts per day, to be incorporated in daily diet.

Of course, with higher amounts we could even probably see better results, but that would not be realistic for a food to be incorporated in daily diet – the purpose of the “prevention” perspective of this work.

I hope that I help you to understand why we selected that amount or the doubts about it. Thank you very much for your interest in the work.


Thank you very much Dr.! It’s encouraging that healthy people were the subjects of your 2018 clinical trial.

May I obtain your permission to use your excellent explanation as a follow up to my blog post?

I and several other people are using your study as the model to improve our health during this lockdown. There have been a lot of errors on my part, but our methods are improving.


Yes, you can use the information, of course. The participants were “healthy” overweight subjects (without medication or treatments of any disease, just adults with overweight). Please, keep safe and have a nice week.


Attached to the last email was his latest coauthored review The Role of Brassica Bioactives on Human Health: Are We Studying It the Right Way? published March 30, 2020, curated in Reviewing clinical trials of broccoli sprouts and their compounds.

“Figure 1 – General scheme of the glucosinolates (GSLs) and common hydrolysis products. ESP: Epithiospecifer proteins.”

Forcing people to learn helplessness

Learned helplessness is a proven animal model. Its reliably-created phenotype is often the result of applying chronic unpredictable stress.

As we’re finding out worldwide, forcing humans to learn helplessness works in much the same way, with governments imposing what amounts to martial law. Never mind that related phenotypes and symptoms include:

  • “Social defeat
  • Social avoidance behavior
  • Irritable bowel syndrome
  • Depression
  • Anxiety
  • Anhedonia
  • Increased hypothalamic-pituitary-adrenal (HPA)-axis sensitivity
  • Visceral hypersensitivity” [1]

Helplessness is both a learned behavior and a cumulative set of experiences. Animal models demonstrate that these phenotypes usually continue on throughout the subjects’ entire lifespans.

Will the problems caused in humans by humans be treated by removing the causes? Or will the responses be approaches such as drugs to treat the symptoms?


A major difference between our current situation and the situation depicted below is that during communism, most people didn’t really trust or believe what the authorities, newspapers, television, and radio said:

Image from Prague’s Memorial to the Victims of Communism


[1] 2014 GABAB(1) receptor subunit isoforms differentially regulate stress resilience curated in If research provides evidence for the causes of stress-related disorders, why only focus on treating the symptoms?

Week 2 of Changing an inflammatory phenotype with broccoli sprouts

To follow up Changing an inflammatory phenotype with broccoli sprouts:

1. My traveling companion used a kitchen scale to measure the weight of broccoli sprouts at Day 3. She started them from one tablespoon of broccoli seeds, and they weighed 60 grams!

The model clinical trial [1] used 30 grams to produce great results:

“The intervention consisted of a 10-week period which included daily consumption of a portion (30 g) of raw, fresh broccoli sprouts. This amount is consistent with a half-serving.”

I asked the study’s corresponding coauthor for clarification of “a half-serving.” Our conversation is at Understanding a clinical trial’s broccoli sprout amount.

Eating a 60 gram “full serving” of 3-day-old broccoli sprouts yielding 27 mg of sulforaphane after microwaving [2] fits [3]‘s guidelines:

“The daily SFN [sulforaphane] dose found to achieve beneficial outcomes in most of the available clinical trials is around 20-40 mg.”

2. My current microwaving time for 60 grams of 3-day-old broccoli sprouts in 100 ml of water with a 1000 W microwave on full power is 35 seconds. Their temperature gets up to 57°C. YMMV.

I immediately cool down the microwaved broccoli sprouts in a colander. See Enhancing sulforaphane content for changes. Go up to the 60°C cliff but don’t fall into the 70°C 65°C canyon:

cliff

The desired range [2]:

“In the temperature range of 50–60°C, a positive correlation was observed between GLR [glucoraphanin] or SFR [sulforaphane] contents and temperature. However, these two physiochemical contents were negatively correlated with temperature when it increased to 70°C.”

3. I had several days of failed crops during Week 2. I switched over to Russian-doll glass bowls with success:

I’d guess that failures were related to excess moisture, which broccoli sprouts hate, hate, hate! Look closely at the top left Day 0 tray below:

Notice concentric raised ribs that are about 1/16″ high. Their effects may have either kept broccoli seeds too wet over a 3-day period, or promoted bacterial growth (although I ran them through a dishwasher after Day 3).

4. I started to put items on the edge of my microwave’s carousel because they don’t heat evenly when placed in the center. I thought uneven heating was a problem that was solved a long time ago, but not for the microwave I bought (Sharp model SMC1131C, which was the least expensive at Best Buy on the day I needed a carousel microwave oven.)


[1] 2018 Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects curated in How much sulforaphane is suitable for healthy people?

[2] 2020 Microwave cooking increases sulforaphane level in broccoli curated in Microwave broccoli to increase sulforaphane levels and Growing a broccoli sprouts Victory Garden

[3] 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease curated in How much sulforaphane is suitable for healthy people?

Do early experiences of hunger affect our behavior, thoughts, and feelings today?

Reposted from five years ago.


A 2015 worldwide human study Hunger promotes acquisition of nonfood objects found that people’s current degree of hungriness affected their propensity to acquire nonfood items.

The researchers admitted that they didn’t demonstrate cause and effect with the five experiments they performed, although the findings had merit. News articles poked good-natured fun at the findings with headlines such as “Why Hungry People Want More Binder Clips.”

The research caught my eye with these statements:

“Hunger’s influence extends beyond food consumption to the acquisition of nonfood items that cannot satisfy the underlying need.

We conclude that a basic biologically based motivation can affect substantively unrelated behaviors that cannot satisfy the motivation.”


The concept of the quotes relates to a principle of Dr. Arthur Janov’s Primal Therapy – symbolic satisfaction of needs. Two fundamentals of Primal Therapy:

  1. The physiological impacts of our early unmet needs drive our behavior, thoughts, and feelings.
  2. The painful impacts of our unfulfilled needs impel us to be constantly vigilant for some way to fulfill them.

Corollary principles of Primal Therapy:

  • Our present efforts to fulfill our early unmet needs will seldom be satisfying. It’s too late.
  • We acquire substitutes now for what we really needed back then.
  • Acquiring these symbols of our early unmet needs may – at best – temporarily satisfy derivative needs.

But the symbolic satisfaction of derived needs – the symptoms – never resolves the impacts of early unfulfilled needs – the motivating causes:

  • We repeat the acquisition behavior, and get caught in a circle of acting out our feelings and impulses driven by these conditions.
  • The unconscious act-outs become sources of misery both to us and to the people around us.

As this study’s findings showed, there’s every reason for us to want researchers to provide a factual blueprint of causes for our hunger sensation effects, such as “unrelated behaviors that cannot satisfy the motivation.“

Hunger research objectives could include answering:

  • What enduring physiological changes occurred as a result of past hunger?
  • How do these changes affect the subjects’ present behaviors, thoughts, and feelings?

Hunger research causal evidence for the effect of why people acquire “items that cannot satisfy the underlying need” may include studying where to start the timelines for the impacts of hunger. The impacts potentially go back at least to infancy when we were completely dependent on our caregivers.

Infants can’t get up to go to the refrigerator to satisfy their hunger. All a hungry infant can do is call attention to their need, and feel pain from the deprivation of their need.

Is infancy far back enough, though, to understand the beginnings of potential impacts of hunger?

If people don’t stand up for their rights, their rights will be forgotten

YouTube took down this interview and a follow-on interview It was known to everybody that the lockdown would cause a catastrophe.


Here’s an interview last week with a German epidemiologist, Professor Wittkowski, who isn’t on a government payroll:

“First of all the elderly and fragile should be separated from the population where the virus is circulating. Everyone else, especially the children, should keep going to school, because they will be the primary impetus for herd immunity.

Flattening the curve prolongs the time a virus stays in the population. People staying indoors keeps the virus healthy.

Like every other respiratory disease, without government intervention, the pandemic would already be over like it’s over in China and South Korea. Except, both in China and South Korea, social distancing started very close to the peak. By keeping the virus from running its course, they are now having a second wave of cases. It will keep on if we don’t let it complete.

There’s nothing to be scared about. This is a flu epidemic like others, maybe more severe. What’s changed is the internet. People get their information in a few seconds, rather than a week.

Tracking a respiratory disease is impossible. Even in times of social distancing. Nature has ways to make sure we survive.

The standard for AIDS reporting, i.e., the date of infection separated from the date of reporting, is not being followed.

If we had herd immunity now, we wouldn’t have a second wave in the fall. Herd immunity typically lasts for a couple of years. If we prevent herd immunity, it is certain that a second wave will occur.

Testing doesn’t stop anything. Antibody testing will give us estimates of herd immunity, which would be useful.

We don’t die of the virus. We die of pneumonia.

The downside of starting containment is that we should not believe that we are more intelligent than mother nature when we were evolving. Mother nature was pretty good at making sure we were a good match for the diseases that we happened to see virtually every year.

I think people, especially in the United States, are more docile than they should be. People should talk with their politicians, question them, ask them to explain. Because if people don’t stand up to their rights, their rights will be forgotten.”

Changing an inflammatory phenotype with broccoli sprouts

This follow up to Growing a broccoli sprouts Victory Garden is what’s gone on during Week 1 of starting to grow broccoli sprouts for a “30 60 grams of fresh broccoli sprouts incorporated daily into the diet” [1] program. See Week 2 of Changing an inflammatory phenotype with broccoli sprouts for changes.

Day 0 – I’ve tried many things to cure chronic inflammation over the years, basing most of my actions on what’s proven to work for other people. These treatments have helped but haven’t completely worked for me. I’ve continued them with the hypothesis that they may have positive synergistic interactions with daily eating 60 grams of 3-day-old broccoli sprouts that yield 27 mg of sulforaphane after microwaving.

Day 0 treatments included two dozen supplements I’ve taken since turning 50, a diet low in advanced glycation end products started last year [2], and naproxen (a nonsteroidal anti-inflammatory drug). The chronically inflamed spots are the left thumb base (arthritis), tendons outside the left ankle (peroneal tendinosis), and left knee tendonitis, all probably consequences of playing golf for 40+ years.

Day 1 – The vertical farming equipment is a Deluxe Kitchen Crop 4-Tray Seed Sprouter Model VKP1200 made by VICTORIO Kitchen Products. I soak one tablespoon of organic broccoli seeds for 12 hours. Take them out of the stackable trays for a twice-daily rinsing, which is counter to directions of pouring water into the tower top. Microwave the Day 3 broccoli sprouts daily per [3]. Run its tray through the dishwasher (but no heat cycle). Put the tray back in rotation for Day 0.

Day 2 – Threw away one of my crutches, naproxen, as taking it had become more of a habit than a necessity. I’d been taking 220 mg twice daily for years until two weeks ago, when I switched to once daily.

“Sulforaphane increases several endogenous antioxidant compounds via the transcription factor Nrf2 [nuclear factor erythroid 2-related factor 2, discovered in 1994]. Of the phytochemicals with Nrf2 inducer capacity, Brassica-derived SFN [sulforaphane] is the most potent naturally occurring biomolecule known at this time.

Another transcription factor, NF-κB, which is associated with inflammatory pathways is downregulated by SFN. This dual action of SFN is especially intriguing in that Nrf2 and NF-κB interact via their own ‘cross talk’.” [4]

Day 3 – Stopped taking 2 mg of sulforaphane in the form of a broccoli sprout extract capsule, and 200 mg of a diindolylmethane (DIM) capsule daily. DIM was raised 195% from Day 0 to Day 70 after daily intake of broccoli sprouts in [1], noting:

“The anti-inflammatory effects observed with broccoli sprouts intake are likely due to the combined effects of all the hydrolysis products of glucosinolates.”

Don’t need either supplement when broccoli sprouts supply them.

The next supplement I’ll drop is N-acetyl-cysteine (NAC), the precursor to our endogenous antioxidant glutathione. I’ve taken a 600 mg capsule twice daily for fifteen years.

[4] goes on and on about sulforaphane / glutathione interactions. For example: “Several well-studied Nrf2-dependent target genes of possible relevance are those encoding synthesis of glutathione (GSH)” in Section 5.2. SFN as a Redox Modulator that included Figure 6 below, and in Section 6. SFN: Its Redox-Modulating Effects:

Day 4 – I’d seen studies of broccoli sprouts that ranged from 3-days old (the most frequent age) to 8-days old. Before [5], I hadn’t found analyses of broccoli sprout age differences in sulforaphane contents, and only a few studies of sulforaphane differences among broccoli sprout cultivated varieties.

Day 5 – I’ve eaten sprouts at 3 – 5 days old, and haven’t noticed a taste difference after microwaving per [3]. Here’s what they look like at Days 0, 1, 2, and 3:

Day 6 – Are you ready to change your phenotype?


References in order of citation:

[1] 2018 Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects

[2] 2016 Dr. Vlassara’s AGE-Less Diet: How a Chemical in the Foods We Eat Promotes Disease, Obesity, and Aging and the Steps We Can Take to Stop It

[3] 2020 Microwave cooking increases sulforaphane level in broccoli curated in Microwave broccoli to increase sulforaphane levels and Growing a broccoli sprouts Victory Garden

[4] 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease

[5] 2020 3-day-old broccoli sprouts have the optimal yields

3-day-old broccoli sprouts have the optimal yields

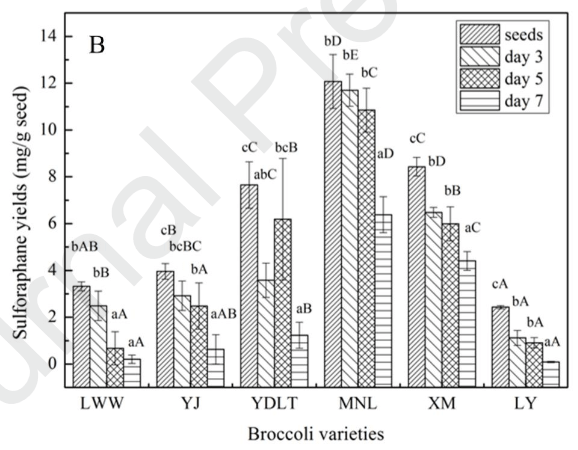
This 2020 Chinese study compared the contents of 3, 5, and 7-day-old broccoli sprouts:

“The objective of this study was:

  1. To optimize the extraction conditions of SF [sulforaphane] from seeds and sprouts at the same time to ensure the maximum SF yields from them;
  2. To compare the SF yields, total flavonoid (TF) contents, and total phenolic (TP) contents from broccoli seeds and sprouts (after 3, 5, and 7 days germination respectively) of six different cultivated varieties; and
  3. To evaluate and compare the the stability and bioaccessibility of SF, TF and TP from broccoli seeds and sprouts upon in vitro gastrointestinal digestion; total antioxidant activities of samples before and after digestion were also investigated in this section.

Most varieties obtained the maximum SF, TP and TF contents in sprouts on day 3. SF contents in sprouts were 46% – 97% of seeds, whereas TP and TF contents in sprouts were 1.12 – 3.58 times higher than seeds among varieties.

sprout ages 1B

After in vitro digestion, broccoli sprouts from MNL variety kept considerable SF, TF, and TP contents, as well as antioxidant capacities, with all values higher than seeds.

SF from seeds and sprouts both showed high bioaccessibility values of 0.91 and 1.00, respectively. The high bioaccessibility of SF in vitro experiments provide an additional evidence for its efficient utilization, as many previous researches have reported a high bioavailability of SF in vivo.”


This study provided higher measures of sulforaphane in vitro bioaccessibility compared with previous studies of in vivo bioavailability.

It was good to read a definitive study that addressed both broccoli sprout age and cultivated variety for optimizing sulforaphane. The need was there. As the study authors put it:

“From the perspective of comparison methods, broccoli varieties, and germination processes, there is still lack of a systematic comparison of SF yields and other bioactive compounds contents between broccoli seeds and sprouts.”

https://www.sciencedirect.com/science/article/pii/S0308814620300637 “Sulforaphane and its antioxidative effects in broccoli seeds and sprouts of different cultivars” (not freely available)

Growing a broccoli sprouts Victory Garden

To follow up How much sulforaphane is suitable for healthy people? I’ve started growing broccoli sprouts, and a “30 60 grams of fresh broccoli sprouts incorporated daily into the diet” [1] program. See Week 2 of Changing an inflammatory phenotype with broccoli sprouts for changes.

I loosely follow [2]‘s sprouting guidelines. One preparation difference is microwaving per [3]‘s findings as follows:

My current microwaving time for 60 grams of 3-day-old broccoli sprouts in 100 ml of water with a 1000 W microwave on full power is 35 seconds. The temperature gets up to 57°C. See Enhancing sulforaphane content for changes. I immediately dump the broccoli sprouts into a colander and spray with cold water to stop heating at the desired temperature.

The first batch of broccoli sprouts was a mild, cabbage-tasting side dish to the home-style chicken soup on page 238 of [4].

The a priori hypotheses:

    1. 30 grams of fresh broccoli sprouts will not have “51 mg (117 μmol)” of glucoraphanin [1] because they “Used the elicitor methyl jasmonate (MeJA) by priming the seeds as well as by spraying daily. MeJA at concentrations of 156 μM act as stressor in the plant and enhances the biosynthesis of the phytochemicals glucosinolates. Compared to control plants without MeJA treatment, the content of compounds as the aliphatic glucosinolate glucoraphanin was enhanced up to 70%.” 117 μmol / 1.70 = 69 μmol is the expected glucoraphanin amount in 30 grams weight of fresh broccoli sprouts. 69 x 2 = 138 μmol in 60 grams.
    2. One measurement [5] of how much sulforaphane is present in fresh broccoli sprouts before microwaving is 100 μmol / 111 g = .9 μmol / g. (.9 x 30 g) = 27 μmol is the expected sulforaphane amount in 30 grams of fresh broccoli sprouts. Changed assumption to 0 μmol sulforaphane due to 2013 Sulforaphane: translational research from laboratory bench to clinic “Broccoli sprouts are correctly described as releasing, generating, or yielding but not containing SFN [sulforaphane].”
    3. Last week a [3] coauthor agreed to make the data available to facilitate calculations. While I’m waiting… The study said the Figure 3 HL60 sulforaphane amount was 2.45 μmol / g. Eyeball estimate of the below Figure 3 control (raw broccoli florets) is a glucoraphanin amount of ~2.2 μmol / g. I assume that the broccoli florets and sprouts conversion would be the same at a 2.45 μmol / 2.2 μmol ≈ 1.11 ratio. I expect that microwaving the raw broccoli sprouts to 60°C will convert the 138 μmol of glucoraphanin to a 153 μmol amount of sulforaphane at this assumed 1.11 conversion ratio.
    4. The estimated sulforaphane weight per [6] would be (153 μmol / 5.64) = 27 mg which is comparable to clinical trial dosages listed in [7] and [8].
    5. I’ve been sitting around a lot since returning from Milano, Italy, on February 24, 2020, and probably weigh around 75 kg. The estimated dosage represents 153 μmol of sulforaphane / 75 kg = 2.04 μmol of sulforaphane / kg, compared to the 1.36 μmol of glucoraphanin / kg average of [1]. (The study provided the subjects’ mean weight in Table 1 as “85.8 ± 16.7 kg.” The average dosage per kg body weight was 117 μmol of glucoraphanin / 85.8 kg = 1.36 μmol of glucoraphanin / kg.)
    6. Don’t have a practical estimate of the amount of sulforaphane I metabolize from post-microwave glucoraphanin that would add to the calculated 153 μmol of sulforaphane. Both [7] and [8] cited a 2012 study that found: “Some conversion of GRN [glucoraphanin] to SFN can occur in response to metabolism by the gut microflora; however, the response is inefficient, having been shown to vary ‘from about 1% to more than 40% of the dose.’”
    7. Don’t have a practical estimate of the “internal dose” [8] that would result from 153+ μmol of sulforaphane.

I don’t have a laboratory in my kitchen 🙂 and won’t have quantified results. See Grow a broccoli sprouts Victory Garden today! for August 2020 practices.


References in order of citation:

[1] 2018 Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects

[2] 2017 You Need Sulforaphane – How and Why to Grow Broccoli Sprouts

[3] 2020 Microwave cooking increases sulforaphane level in broccoli curated in Microwave broccoli to increase sulforaphane levels

fsn31493-fig-0003-m

[4] 2016 Dr. Vlassara’s AGE-Less Diet: How a Chemical in the Foods We Eat Promotes Disease, Obesity, and Aging and the Steps We Can Take to Stop It

[5] 2016 Effect of Broccoli Sprouts and Live Attenuated Influenza Virus on Peripheral Blood Natural Killer Cells: A Randomized, Double-Blind Study

[6] 2020 https://pubchem.ncbi.nlm.nih.gov/compound/sulforaphane lists sulforaphane’s molecular weight as 177.3 g / mol. A 1 mg weight of sulforaphane equals a 5.64 μmol sulforaphane amount (.001 / 177.3).

[7] 2019 Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease

[8] 2019 Broccoli or Sulforaphane: Is It the Source or Dose That Matters? Note that a coauthor didn’t disclose their business’ conflict of interest for an effectively promoted commercial product.

How much sulforaphane is suitable for healthy people?

This post compares and contrasts two perspectives on how much sulforaphane is suitable for healthy people. One perspective was an October 2019 review from John Hopkins researchers who specialize in sulforaphane clinical trials:

Broccoli or Sulforaphane: Is It the Source or Dose That Matters?

These researchers didn’t give a consumer-practical answer, so I’ve presented a concurrent commercial perspective to the same body of evidence via an October 2019 review from the Australian founder of a company that offers sulforaphane products:

Sulforaphane: Its “Coming of Age” as a Clinically Relevant Nutraceutical in the Prevention and Treatment of Chronic Disease


1. Taste from a clinical trial perspective:

“Harsh taste (a.k.a. back-of-the-throat burning sensation) that is noticed by most people who consume higher doses of sulforaphane, must be acknowledged and anticipated by investigators. This is particularly so at higher limits of dosing with sulforaphane, and not so much of a concern when dosing with glucoraphanin, or even with glucoraphanin-plus-myrosinase.

Presence and/or enzymatic production of levels of sulforaphane in oral doses ranging above about 100 µmol, creates a burning taste that most consumers notice in the back of their throats rather than on the tongue. Higher doses of sulforaphane lead to an increased number of adverse event reports, primarily nausea, heartburn, or other gastrointestinal discomfort.”

Taste wasn’t mentioned in the commercial review. Adverse effects were mentioned in this context:

“Because SFN is derived from a commonly consumed vegetable, it is generally considered to lack adverse effects; safety of broccoli sprouts has been confirmed. However, use of a phytochemical in chemoprevention engages very different biochemical processes when using the same molecule in chemotherapy; biochemical behaviour of cancer cells and normal cells is very different.”

2. Commercial products from a clinical trial perspective:

“Using a dietary supplement formulation of glucoraphanin plus myrosinase (Avmacol®) in tablet form, we observed a median 20% bioavailability with greatly dampened inter-individual variability. Fahey et al. have observed approximately 35% bioavailability with this supplement in a different population.”

Avmacol appeared to be the John Hopkins product of choice, as it was mentioned 15 times in its clinical trials table. A further investigation of Avmacol showed that its supplier for broccoli extract, TrueBroc, was cofounded by a John Hopkins coauthor! Yet the review stated:

“The authors declare no conflict of interest.”

Please disclose easily discoverable ethical and commercial conflicts without prevarication. Other products were downgraded with statements such as:

“5 or 10 g/d of BroccoPhane powder (BSP), reported to be rich in SF, daily x 4 wks (we have assayed previously and found this not to be the case).”

They also disclaimed:

“We have indicated clinical studies in which label results have been used rather than making dose measurements prior to or during intervention.”

No commercial products – not even the author’s own company’s – were directly mentioned in a commercial perspective.

3. Dosage from a clinical trial perspective:

“Reporting of administered dose of glucoraphanin and/or sulforaphane is a poor measure of the bioavailable / bioactive dose of sulforaphane. As a consequence, we propose that the excreted amount of sulforaphane metabolites (sulforaphane + sulforaphane cysteine-glycine + sulforaphane cysteine + sulforaphane N-acetylcysteine) in urine over 24 h (2–3 half-lives), which is a measure of “internal dose”, provides a more revealing and likely consistent view of delivery of sulforaphane to study participants.

Only recently have there been attempts to define minimally effective doses in humans – an outcome made possible by development of consistently formulated, stable, bioavailable broccoli-derived preparations.”

Dosage from a commercial perspective:

“Of available SFN clinical trials associated with genes induced via Nrf2 activation, many demonstrate a linear dose-response. More recently, it has become apparent that SFN can behave hormetically with different effects responsive to different doses. This is in addition to its varying effects on different cell types and consequent to widely varying intracellular concentrations.

A 2017 clinical pilot study examined the effect of an oral dose of 100 μmol (17.3 mg) encapsulated SFN on GSH [reduced glutathione] induction in humans over 7 days. Pre- and postmeasurement of GSH in blood cells that included T cells, B cells, and NK cells showed an increase of 32%. Researchers found that in the pilot group of nine participants, age, sex, and race did not influence the outcome.

Clinical outcomes are achievable in conditions such as asthma with daily SFN doses of around 18 mg daily and from 27 to 40 mg in type 2 diabetes. The daily SFN dose found to achieve beneficial outcomes in most of the available clinical trials is around 20-40 mg.”

The author’s sulforaphane products are available in 100, 250, and 700 mg capsules of enzyme-active broccoli sprout powder.

4. Let’s see how these perspectives treated a 2018 Spanish clinical trial published as Effects of long-term consumption of broccoli sprouts on inflammatory markers in overweight subjects.

From a commercial perspective:

“In a recent study using 30 grams of fresh broccoli sprouts incorporated daily into diet, two key inflammatory cytokines were measured at four time points in forty healthy overweight [BMI 24.9 – 29.9] people. Levels of both interleukin-6 (Il-6) and C-reactive protein (CRP) declined over the 70 days during which sprouts were ingested.

These biomarkers were measured again at day 90, wherein it was found that Il-6 continued to decline, whereas CRP climbed again. When the final measurement was taken at day 160, CRP, although climbing, had not returned to its baseline value. Il-6 remained significantly below baseline level at day 160.

Sprouts contained approximately 51 mg (117 μmol) GRN [glucoraphanin], and plasma and urinary SFN metabolites were measured to confirm that SFN had been produced when sprouts were ingested.”


From a clinical trial perspective, glucoraphanin dosage was “1.67 (GR) μmol/kg BW.” This wasn’t accurate, however. It was assumed into existence by:

“In cases where authors did not indicate dosage in μmol/kg body weight (BW), we have made those calculations using a priori assumption of a 70 kg BW.”

117 μmol / 1.67 μmol/kg = 70 kg.

This study provided overweight subjects’ mean weight in its Table 1 as “85.8 ± 16.7 kg.” So its actual average glucoraphanin dosage per kg body weight was 117 μmol / 85.8 kg = 1.36 μmol/kg. Was making an accurate calculation too difficult?

A clinical trial perspective included this study in Section “3.2. Clinical Studies with Broccoli-Based Preparations: Efficacy” subsection “3.2.8. Diabetes, Metabolic Syndrome, and Related Disorders.” This was somewhat misleading, as it was grouped with studies such as a 2012 Iranian Effects of broccoli sprout with high sulforaphane concentration on inflammatory markers in type 2 diabetic patients: A randomized double-blind placebo-controlled clinical trial (not freely available).

A commercial perspective pointed out substantial differences between these two studies:

“Where the study described above by Lopez-Chillon et al. investigated healthy overweight people to assess effects of SFN-yielding broccoli sprout homogenate on biomarkers of inflammation, Mirmiran et al. in 2012 had used a SFN-yielding supplement in T2DM patients. Although the data are not directly comparable, the latter study using the powdered supplement resulted in significant lowering of Il-6, hs-CRP, and TNF-α over just 4 weeks.

It is not possible to further compare the two studies due to vastly different time periods over which each was conducted.”


The commercial perspective impressed as more balanced than the clinical trial perspective. The clinical trial perspective also had an undisclosed conflict of interest!

A. The clinical trial perspective:

  • Effectively promoted one commercial product whose supplier was associated with a coauthor;
  • Downgraded several other commercial products; and
  • Tried to shift responsibility for the lack of “minimally effective doses in humans” to commercial products with:

    “Only recently have there been attempts to define minimally effective doses in humans – an outcome made possible by the development of consistently formulated, stable, bioavailable broccoli-derived preparations.”

But unless four years previous is “recently,” using commercial products to excuse slow research progress can be dismissed. A coauthor of the clinical trial perspective was John Hopkins’ lead researcher for a November 2015 Sulforaphane Bioavailability from Glucoraphanin-Rich Broccoli: Control by Active Endogenous Myrosinase, which commended “high quality, commercially available broccoli supplements” per:

“We have now discontinued making BSE [broccoli sprout extract], because there are several high quality, commercially available broccoli supplements on the market.”

The commercial perspective didn’t specifically mention any commercial products.

B. The commercial perspective didn’t address taste, which may be a consumer acceptance problem.

C. The commercial perspective provided practical dosage recommendations, reflecting their consumer orientation. These recommendations didn’t address how much sulforaphane is suitable for healthy people, though.

The clinical trial perspective will eventually have to make practical dosage recommendations after they stop dodging their audience – which includes clinicians trying to apply clinical trial data – with unhelpful statements such as:

“Reporting of administered dose of glucoraphanin and/or sulforaphane is a poor measure of the bioavailable / bioactive dose of sulforaphane.”

How practical was their “internal dose” recommendation for non-researcher readers?


Here’s what I’m doing to answer how much sulforaphane is suitable for healthy people.

I’d like to posthumously credit my high school literature teachers Dorothy Jasiecki and Martin Obrentz for this post’s compare-and-contrast approach. They both required their students to read at least two books monthly, then minimally handwrite a 3-page (single-spaced) paper comparing and contrasting those books.

Each monthly assignment was individualized so that students couldn’t undo the assignment’s purpose – to think for yourself – with parasitical collaboration. This former practice remains a good measure of intentional dumbing-down of young people, the intent of which has become clearer.

You can see from these linked testimonials that their approach was in a bygone era, back when some teachers considered a desired outcome of public education to be that each individual learned to think for themself. My younger brother contributed:

“I can still remember everything Mr. Obrentz ever assigned for me to read. He was the epitome of what a teacher should be.”

Microwave broccoli to increase sulforaphane levels

This 2020 Chinese/USDA study investigated effects on sulforaphane amount from heating broccoli in water and microwaving at different power settings to different temperatures:

“Microwave treatment causes a sudden collapse of cell structure due to the increase in osmotic pressure difference over vacuole membrane. Mild heating could increase SFR [sulforaphane] level, possibly explained by the increased activity of MYR [the enzyme myrosinase] which can hydrolyze GLR [glucoraphanin] into SFR at high temperature (up to 60°C).

Microwave‐cooked broccoli had higher levels of these two compounds compared to broccoli heated in water. The broccoli sample without cooking as a control showed the least amount of GLR, indicating that microwave heating did help to release more GLR from the cell.

In the temperature range of 50–60°C, a positive correlation was observed between GLR or SFR contents and temperature. However, these two physiochemical contents were negatively correlated with temperature when it increased to 70°C.

The glucoraphanin (GLR) and sulforaphane (SFR) contents (μmol/g DW) in florets of broccoli during microwaving at 40, 50, 60, and 70°C using low power level (LL) or high power level (HL). Data are reported as the mean ± SD (n = 3). Values with different letters are significantly (p < .05) different.

[For example, sulforaphane levels of the control (raw), LL40, LL70, and HL40 conditions weren’t significantly different, and the HL70 level was significantly lower than those levels]. The microwave using high level at 60°C showed the greatest SFR level (2.45 µmol/g DW).”

Table S1 from the supporting material:

Temperature

(°C)

Time

(S)

Power level

(W)

Heating in water 40 185 NA
50 230
60 262
70 290
Microwave (HL) 40 65 950
50 90
60 108
70 120
Microwave (LL) 40 115 475
50 148
60 178
70 200

https://onlinelibrary.wiley.com/doi/10.1002/fsn3.1493 “Microwave cooking increases sulforaphane level in broccoli”


The researchers demonstrated a more effective method of increasing sulforaphane than did the cited and widely discussed 2004 Heating decreases epithiospecifier protein activity and increases sulforaphane formation in broccoli (not freely available). The older study methods were difficult to implement in kitchens, and evaluated heating temperature as the only factor.

The present study added microwave power level irradiation effects as a factor, and simplified heating temperature implementation. People can use Table S1 to maximize broccoli floret sulforaphane content in their kitchens. See Week 2 of Changing an inflammatory phenotype with broccoli sprouts for changes.

The study provided an optimal sulforaphane end result of “(2.45 µmol/g DW)”. I asked a study author for additional data, and they replied:

“The control GLR and SLR amount was 2.18 and 0.22 µmol/g DW, respectively, while the HL60 GLR amount was 2.78 µmol/g DW.”

Microwaving 10 grams of broccoli florets to 60°C (140°F) increased the sulforaphane amount by 1,114% (2.45 / .22)! That also increased the glucoraphanin amount by 27% (2.78 / 2.18) for further processing into sulforaphane after eating.

I replied: That’s an exciting result, increasing sulforaphane more than 11 times, while also increasing glucoraphanin! I haven’t found similar experiments with broccoli sprouts. Would you expect similar results?

The study author responded:

“We didn’t expect this result, and think microwave irradiation might help to release more conjugated forms of glucosinolates and then get hydrolyzed by released myrosinase. Further studies are being carried out.”


The study also measured broccoli stems:

“GLR and SFR were hardly detected in stems. Less than 52% of GLR was detected in the [50/50] mixture of florets and stems compared to florets.

Microwaved at 60°C, the florets had a concentration of GLR and SFR at 2.78 and 2.45 µmol/g DW, respectively, which was significantly higher than the levels detected in mixture of florets and stems (1.21 and 0.82 µmol/g DW, respectively).”

The 50% florets / 50% stems mixture’s glucoraphanin amount of 1.21 µmol was roughly comparable with the 1.08 µmol glucoraphanin amount of mature broccoli extract in item 2 below.

Reminders from Eat broccoli sprouts today:

  1. A 1 mg sulforaphane weight equals a 5.64 μmol sulforaphane amount.
  2. “Content of glucoraphanin in extract from broccoli sprouts was 16.6 μmol per gram of fresh weight. In contrast, mature broccoli extract contained 1.08 μmol per gram of fresh weight.”
  3. The bioavailability of sulforaphane in a broccoli sprout extract with the myrosinase enzyme 100 μmol gelcap was 36.1% which weighed 6.4 mg.
  4. The question of how much sulforaphane is suitable for healthy people remains unanswered.