A review of epigenetic transgenerational inheritance of reproductive disease

This 2015 Washington review of epigenetic transgenerational inheritance of reproductive disease defined transgenerational effects as follows:

“In considering transgenerational phenomena it is important to distinguish between direct exposure effects versus germline (sperm or egg) mediated transgenerational events.

When a gestating F0 generation female is exposed the F0 generation female, the F1 generation fetus and the germ cell (sperm or egg) that is inside the fetus and that will produce the F2 generation are all directly exposed. Any effects in the F0, F1 and F2 generations may be due to direct exposure toxicity or to environmentally induced epigenetic changes in the directly exposed cells. Examination of the F3 generation (great grand-offspring) is needed to determine if a transgenerational phenomenon has occurred, since the F3 generation has had no direct exposure effects.

In contrast, in the event an adult male or non-pregnant female is exposed, the F0 generation adult and the germ cells that will generate the F1 generation are directly exposed, such that examination of the F2 generation (grand-offspring) is required to demonstrate a transgenerational phenomenon.”


This review was an example of a government agency commissioning science that narrowly supported their view. NIEHS funded this review, and the authors interpreted “environment” in “Environmentally Induced Epigenetic Transgenerational Inheritance of Reproductive Disease” to fit this conduit of public funds.

The problem was that this interpretation of “environment” limited the subject to the categories pictured in this Venn diagram. The authors’ tailoring of “environmentally induced” to the government agency’s interests should have similarly restricted the title.

F3 sperm epimutations


Other interpretations of “environment” were in studies such as:

and their references. Such studies demonstrated both that:

  1. Environmental factors like stress and nutrition – especially in early life – cause diseases in later life; and
  2. These diseases may be inherited by the subjects’ descendants.

The authors elsewhere referred generally and specifically (nutrition) to studies of other environmental factors.

Have you ever heard that our children and then their children could possibly inherit our diseases caused by stressful environments? Wouldn’t that research be of equal to or greater importance in our lives than pesticides’ harmful effects?

http://www.bioone.org/doi/10.1095/biolreprod.115.134817 “Environmentally Induced Epigenetic Transgenerational Inheritance of Reproductive Disease”

Fetal exposure to sex hormones and female anxiety

This 2015 Swedish rodent study found:

“Women with polycystic ovary syndrome (PCOS) display high circulating androgen levels that may affect the fetus and increase the risk of mood disorders in offspring.

Although clinical data are inconsistent, there are indications that androgens play a crucial role in behavior and mood regulation in females.

Studies on the link between testosterone and anxiety behavior in males have generated inconsistent results.

Higher circulating testosterone has previously been reported in female rat PNA [prenatal androgen] offspring. This discrepancy may be a result of the higher doses of maternal testosterone (5 mg) used in the previous study compared with the present study (0.5 mg).

Although the anxiety-like behavior observed in the female PNA offspring in the present study cannot be directly explained by high circulating androgens, the reduced AR [androgen receptor] expression in the amygdala suggests a compensatory response to the high prenatal testosterone exposure, a result implicating the amygdala as the CNS site underlying the changes in anxiety in the PNA offspring. This idea is further strengthened by our experiment showing that subchronic testosterone exposure into amygdala is sufficient to produce anxiety-like behavior in adult females.

Maternal testosterone exposure causes anxiety-like behavior in female, and to a lesser extent male offspring, an effect that seems to occur during fetal life and to be mediated via AR in the amygdala, together with changes in ER [estrogen receptor] and in the serotonergic and GABAergic pathways in the amygdala and hippocampus of female PNA rats.”

The news coverage – too much testosterone caused anxiety-like symptoms in females whether they are adults or fetuses – was NOT what the study found. The headlines disregarded its caveat:

“The anxiety-like behavior observed in the female PNA offspring in the present study cannot be directly explained by high circulating androgens.”

I look forward to research on floor levels of testosterone, below which there are also adverse effects on females. There is such evidence, but would it play well with popular memes?

See Sex hormone exposure to the developing female fetus causes infertility in adulthood for another study that used the PCOS phenotype.

http://www.pnas.org/content/112/46/14348.full “Maternal testosterone exposure increases anxiety-like behavior and impacts the limbic system in the offspring”

A molecular study of the epigenetic regulation of memory

This 2015 Norwegian rodent study provided:

“New insights into the molecular underpinnings of synaptic plasticity.

We report the first global transcriptome [all RNA found in specific cells] analysis of in vivo synaptic plasticity, using the well-established model of LTP [long-term potentiation, an increase in synaptic strength that underlies memory] in the rat dentate gyrus [a region of the hippocampus where neurogenesis occurs].

We have identified a number of novel lncRNAs [long (more than 200 nucleotides) noncoding (non-protein coding) RNA] that are dynamically regulated in response to LTP. In addition, we also observed an altered expression of multiple classes of repeat elements [mobile DNA sequences often involved in mutations] including retrotransposons [a repeat element type formed by copy-and-paste mechanisms].

The results presented here reveal a vast extension of mRNAs [messenger RNA, a large RNA that carries codes for protein production] previously not associated with neuronal plasticity; the discovery of extensive, dynamic regulation of lncRNAs, repeat elements, and tRNA [transfer RNA that links mRNA and amino acids during protein production] following LTP induction in the adult rat brain.

These findings provide a broader foundation for elucidating the transcriptional and epigenetic regulation of synaptic plasticity.”

Regarding lncRNA:

“We annotate a total of 10,256 novel lncRNAs in the rat transcriptome.

To infer possible functions of lncRNAs, we correlated [71] differentially expressed lncRNAs with regulated protein coding genes.

There are no established rules for predicting the function of lncRNAs.”

Regarding repeat elements:

“It is intriguing to consider that expression of repeat elements during LTP is the first step toward retrotransposition and reshaping of the neuronal genome. A hypothetical mechanism for how these repeat elements could be linked to memory, would be that a certain stimuli, whether it is stress or a learning task (here LTP), deregulate the repression of repeat elements which are then rapidly and transiently transcribed. These elements reinsert themselves back into the genome of stimulated neurons where they influence the expression of neighboring genes.

The present work supports the intriguing hypothesis that dynamic retrotransposition may act as a molecular means to reprogram the neuronal genome as part of long-term synaptic plasticity and memory formation.”

See RNA as a proxy signal for context-specific biological activity for more about lncRNA.

http://journal.frontiersin.org/article/10.3389/fnins.2015.00351/full “Dynamic expression of long noncoding RNAs and repeat elements in synaptic plasticity”

Is the purpose of research to define opportunities for interventions?

In this 2014 review, a social scientist first presented an interpretive history of what he found to be important in the emergence of epigenetics. He proceeded into his ideas of “a possible agenda of the social studies of the life-sciences” in the “postgenomic age” with headings such as “Postgenomic biopolitics: “upgrade yourself” or born damaged for ever?”

This perspective included:

“The upgradable epigenome may become the basis for a new motivation to intervene, control and improve it through pharmacological agents or social interventions.

An important trend is the use of epigenetic and developmental findings in the so-called early-intervention programmes.

It is possible that epigenetic findings will become increasingly relevant in social policy strategies.”


In this blog I often highlight research that may help us understand details of how each of us is a unique individual. It’s my view that insofar as research helps each of us understand our unique, real self, we may be able to empathetically understand others’ unique qualities.

Click individual differences for a sample of how researchers explain away uniqueness in order to converge on a study’s desired objectives. There’s seldom an attempt to further understand what caused each subject to develop their unique qualities.

Why would this reviewer advocate that

  • Researchers,
  • People working in the social sciences,
  • People employed or involved in social services, and
  • Their sponsors and employers

intentionally disregard another individual’s unique qualities?

I’ll answer this question from a perspective that explains how this common, reflexive action derives from a person being unable to face the facts of their own life. Pertinent fundamentals of Dr Arthur Janov’s Primal Therapy are:

  1. Pain motivates a person’s unconscious act-outs of their underlying problems.
  2. The behavior that caused a problem is sometimes also the act-out behavior.
  3. Act-outs enable a person to re-experience the feelings of their historical struggles, in a vain attempt to resolve them.
  4. Due to pain barriers, people seldom become consciously aware of and – more importantly – address the causes for their own problematic behavior.
  5. “The patient has the power to heal himself.”

A consequent hypothesis is that a person will often glorify their unconscious act-outs and surround themself with justifications for these actions. For example, a person who can’t sit still may refer to their incessant activity with socially acceptable phrases such as “I’m always busy” or “I love to travel.” They’ll structure their life to enable their unconscious behavior, never questioning how they were attracted to an always-on-the-go occupation such as flight attendant, only vaguely feeling that they were made for it.

The behavior relevant to the current review may be exhibited by a person with a history of having no control over their own life. Following the above first two fundamentals, the pain of historically not having control over their life may motivate them to control other people’s lives.

Unfortunately for everyone who’s affected, such unconscious act-outs don’t resolve anything:

  1. The initiator may achieve some symbolic satisfaction by controlling others’ lives.
  2. This temporary satisfaction doesn’t make the initiator’s underlying problems less painful.
  3. The motivation impelling these unconscious act-outs isn’t thereby reduced.
  4. So the initiator soon repeats their controlling behavior, stuck in a loop of unresolved feelings.
  5. Since the self-chosen interests of someone who’s being controlled are lesser concerns to the initiator than exercising control, the controlled person may or may not be helped by the controller’s act-outs.

Research provides abundant evidence that we are unique individuals.

This is a strong indicator of who is best qualified to direct each of our unique lives.

A person who is driven to control others’ lives won’t accept epigenetic research as instructive for understanding, honoring, and respecting others as unique individuals. They’ll use research as a way to enable their own unconscious act-outs, and view it as offering opportunities for interventions into the lives of others.

This is the way that “pharmacological agents or social interventions” are often the intended “use of epigenetic and developmental findings.” Interventions receive justifications with “a possible agenda of the social studies of the life-sciences.”

Becoming aware of one’s own act-outs – and then individually addressing one’s own underlying problems – often take backseats to employment and other concerns to keep enabling one’s own behavior. That makes it likely that interventions justified by “epigenetic findings..in social policy” will continue, whether or not the subjects agree that they’re being helped.

For examples, take a look at a few of the YouTube presentations by people employed in the social sciences and social services on a topic of epigenetics. Compare them with the current state of epigenetic research in Grokking an Adverse Childhood Experiences (ACE) score.

What did you notice? How many presentations emphasized disrupted prenatal development – a period when problems can be prevented? Did you instead see that many more of the presentations emphasized controlling behavior?

http://journal.frontiersin.org/article/10.3389/fnhum.2014.00309/full “The social brain meets the reactive genome: neuroscience, epigenetics and the new social biology

Transgenerational epigenetic programming with stress and microRNA

This 2015 Pennsylvania rodent study found:

“Sperm miRs [microRNAs, a small non-coding RNA that has a role in gene expression] function to reduce maternal mRNA [messenger RNA, a large RNA that carries codes for protein production] stores in early zygotes, ultimately reprogramming gene expression in the offspring hypothalamus and recapitulating the offspring stress dysregulation phenotype.”

These researchers caused stress-induced changes at an early stage of embryonic development with microRNA injections. Resultant adverse effects weren’t observed until subjects were adults!

Most news coverage focused on it being a male’s stress, not a female’s, that affected a developing embryo. Either or both sexes can epigenetically disadvantage a fetus – okay.

Demonstrating how a damaging influence can begin immediately after conception, but symptoms didn’t present until adulthood made this study newsworthy.


Although the term “transgenerational” was used in the study’s title, abstract, and elsewhere, studied epigenetic effects were intergenerational rather than transgenerational. Per A review of epigenetic transgenerational inheritance of reproductive disease, for the term to apply, researchers need to provide evidence in at least the next 2 male or non-gestating female generations and/or 3 gestating female generations of:

“Altered epigenetic information between generations in the absence of continued environmental exposure.”


From a press release, a study coauthor who also coauthored How to make a child less capable even before they are born: stress the pregnant mother-to-be stated:

“Bale suspects that when a male experiences stress it may trigger the release of miRs contained in exosomes from epithelial cells that line the epididymis, the storage and maturation site for sperm between the testes and the vas deferens. These miRs may be incorporated into maturing sperm and influence development at fertilization.”

Not all stress-related gene expression in pituitary and adrenal glands differed.

http://www.pnas.org/content/112/44/13699.full “Transgenerational epigenetic programming via sperm microRNA recapitulates effects of paternal stress”

A review of the epigenetic basis for mental illness

This 2015 New York combined animal and human review of epigenetic studies noted:

“While genetic factors are important in the etiology of most mental disorders, the relatively high rates of discordance among identical twins, particularly for depression and other stress-related syndromes, clearly indicate the importance of additional mechanisms.

Environmental factors such as stress are known to play a role in the onset of these illnesses.

Exposure to such environmental insults induces stable changes in gene expression, neural circuit function, and ultimately behavior, and these maladaptations appear distinct between developmental versus adult exposures.

Increasing evidence indicates that these sustained abnormalities are maintained by epigenetic modifications in specific brain regions.”

Placing the “maladaptations” and “sustained abnormalities” phrases into their contexts:

  • A fetus biologically adapted to their environment – however toxic it was – in order to best survive.
  • These adaptations for survival were subsequently viewed as Disrupted Neurodevelopment and “maladaptations” from the perspectives of normal development and environments.
  • The “sustained abnormalities” caused within the earlier environments “are maintained by epigenetic modifications.” An improved environment wasn’t impetus enough to change developmental “maladaptations.”

Per the below link, it’s been a month since this review was published. Why has there been ZERO news coverage of it?

One reason may be that the Friedman Brain Institute, Icahn School of Medicine at Mount Sinai, didn’t issue a press release or otherwise publicize it. Another reason may be the groups that are opposed to its findings:

  • Parents who provided harmful environments for their children, beginning at conception;
  • People who feel threatened when scientific causal evidence resonates with what happened in their own lives, and in response, limit their empathetic understanding of others’ problems;
  • Social workers, psychologists, and others in industries whose paychecks depend on efforts that aren’t directed towards ameliorating the causes for these later-life effects;
  • Psychiatrists and medical personnel whose livelihoods depend on pharmaceutical and other treatments that only alleviate symptoms;
  • Researchers whose funding depends on producing non-etiologic findings.

Despite resistance to this review’s findings, a large number of people would benefit from publicizing evidence for:

“These sustained abnormalities are maintained by epigenetic modifications in specific brain regions.”

http://nro.sagepub.com/content/early/2015/09/24/1073858415608147 “Epigenetic Basis of Mental Illness”

Grokking an Adverse Childhood Experiences (ACE) score

What does it take to empathetically understand, to make a part of oneself, to grok an ACE score?

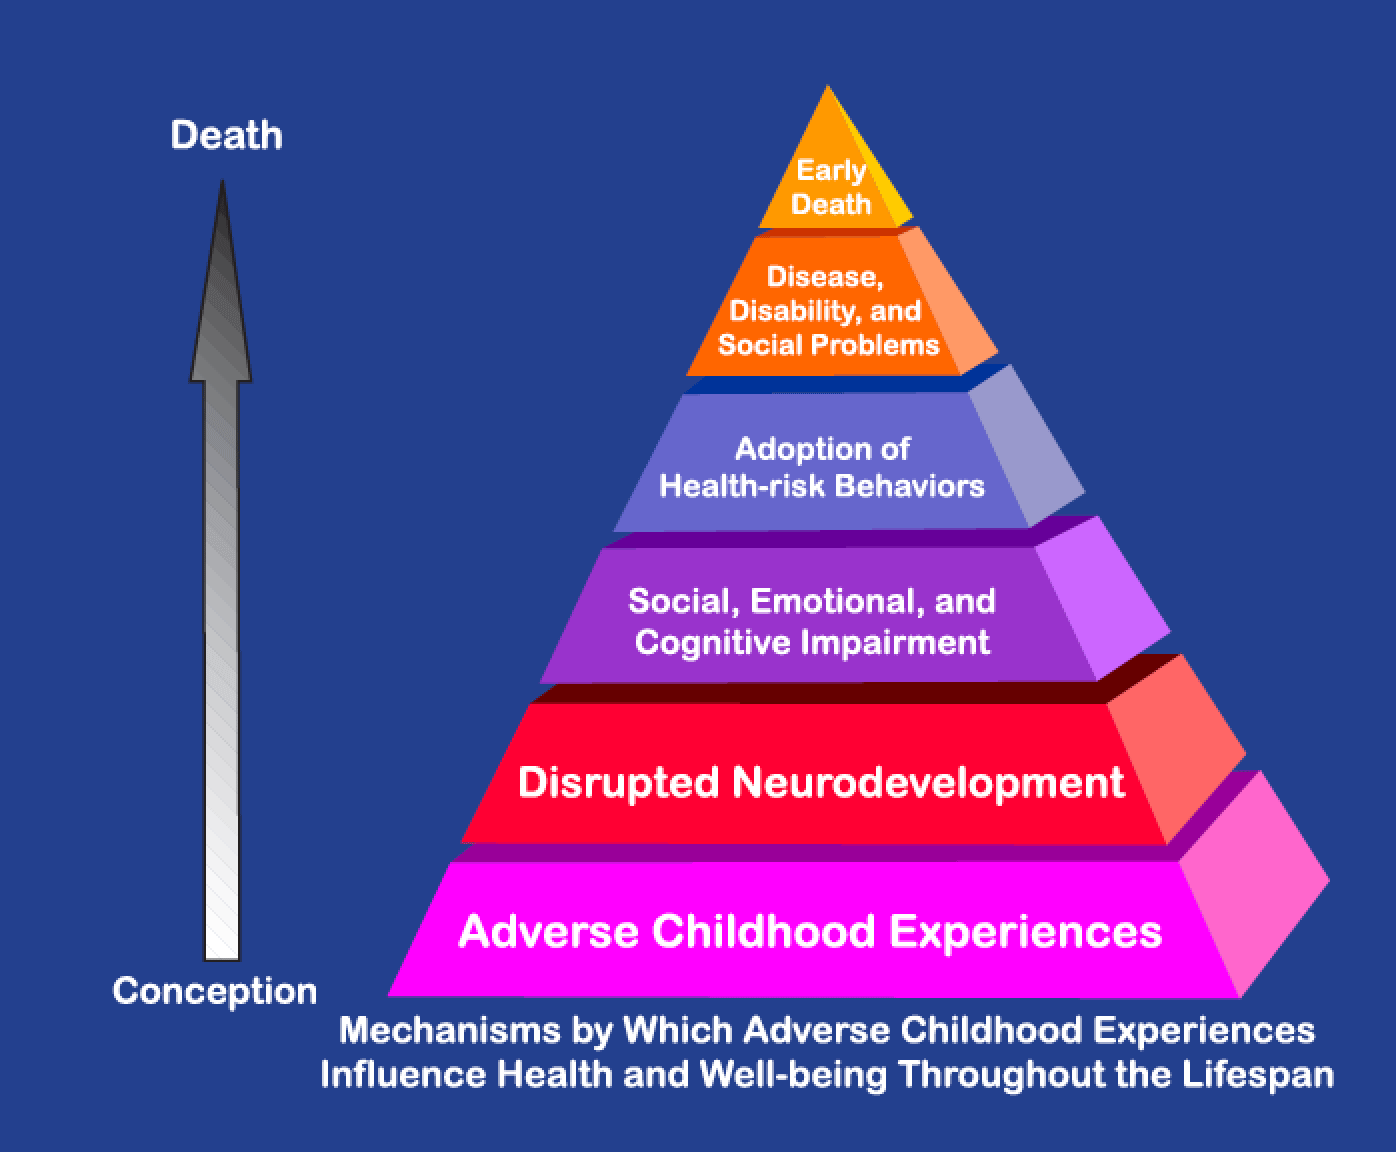
The ACE effort was initiated in 1985 in an era before epigenetics was well-studied. Its artifacts included the ACE pyramid:

The_ACE_PyramidThe historical ACE lifespan continuum on the left began at conception. The pyramid on the right promoted a limited view of ACE that assigned childhood as the pyramid’s base.

Current official depictions of the ACE pyramid assign an expanded view of ACE as the pyramid’s base. The viewer’s attention is directed to “Scientific Gaps” between pyramid layers, but the largest gap remains: the continuum starts at conception but the pyramid still starts at childhood. The narrative claims:

“To provide scientific information that would be useful for developing new and more effective prevention programs.”

The official ACE pyramid doesn’t accurately reflect current science documented in, for example, Epigenetic effects of early life stress exposure. By downplaying Disrupted Neurodevelopment that may begin at conception, governing agencies implicitly endorse approaches that fail to address prenatal causes for later-life adverse effects.


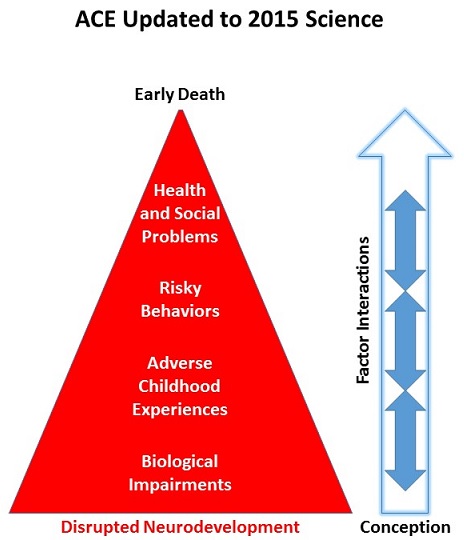
If the ACE diagram was drawn thirty years later in 2015 to incorporate evidence for epigenetics, Disrupted Neurodevelopment wouldn’t be a consequent layer to an ACE base. The potential start of Disrupted Neurodevelopment would coincide with conception:Updated for 2015 to show Disrupted Neurodevelopment

What’s an example of current ACE-related scientific evidence that wasn’t present three decades ago and also isn’t represented in the official ACE pyramid? Prenatal Disrupted Neurodevelopment may be considered today as a possible consequence of a “Yes” answer to half of the original ACE questions:

  • Were your parents were too drunk or high to take care of you or take you to the doctor?
  • Were your parents ever separated or divorced?
  • Was your mother often or very often pushed, grabbed, slapped, or had something thrown at her?
  • Did you live with anyone who was a problem drinker or alcoholic or who used street drugs?
  • Was a household member depressed or mentally ill?

These threats and other stresses cause a fetus to biologically adapt. When such adaptations occur during prenatal development, they may:

  • Have much larger impacts and
  • Cause Biological Impairments that
  • Don’t unassistedly disappear over time.

Emphasizing Disrupted Neurodevelopment that may begin at conception would encourage:

  • Research that’s directed toward producing causal evidence for adaptations that largely occur during the early periods of an individual’s lifespan; and
  • Research on how these adaptations consistently influence our later-life ideas, biology, and behavior.

The above recommendations for research are neither the current focus of ACE research nor the direction of related efforts to assist affected individuals. Relevant studies that I’ve curated on this blog often only produced symptomatic evidence:

  • If a study couched its findings in non-etiologic phrases such as “is associated with” or “is linked to” or “may relate to,” it didn’t address ACE originating causes.
  • “New and more effective prevention programs” seldom address Disrupted Neurodevelopment and Biological Impairments with efforts to reduce the source of the damage.
  • If a program’s presentation showed multivariate analyses with ACE score probabilities and percentages, it didn’t address originating causes.

Here’s a YouTube search of ACE + adverse. Evaluate the current focus of ACE efforts by people employed in the social sciences and services. What did you notice?

How many presentations emphasized prenatal Disrupted Neurodevelopment, a period during which problems may be prevented by addressing causes? Did you instead see that these were outnumbered by many more presentations that emphasized Health and Social Problems symptom interventions?


So, what does it take to empathetically understand, to make a part of oneself, to grok a person’s ACE score?

Regarding empathy – it’s best to avoid the advice of studies such as:

People who are helped may not recognize it at first, but over time, they’ll sense whether the helper’s empathy is genuine.

Regarding understanding – I feel that people first need to ameliorate the origins of their own problems. Then they may be able to help others therapeutically address causes for ACE symptoms.

Need proof? Think of someone you’ve met whose thoughts and feelings and behavior were caught up in and motivated by their own problems:

  • Did you feel they could empathetically understand others?
  • Wasn’t the welfare of the people who may have been helped truly incidental and secondary to someone who was acting out their own problems?

Stress-induced epigenetic DNA modifications may be inherited

This 2015 Australian plant summary study made several points:

“Non-transmission of epigenetic marks through meiosis may be regarded as an epigenetic modification in itself. We should understand the implications for plant evolution in the context of both selection for and selection against transgenerational epigenetic memory.

Both epigenetic inheritance and resetting are mechanistically directed and targeted. Stress-induced epigenetic modifications may buffer against DNA sequence-based evolution to maintain plasticity, or may form part of plasticity’s adaptive potential.

In some cases the signature of the stress experience remains in the epigenome after relief from the stress, providing a “memory.” If this memory conditions the response to stress during subsequent development, the organism is said to be epigenetically primed. If the memory of the stress experienced by a parent conditions the response of its progeny, this epigenetic priming may be transgenerational.

Epigenetic and genetic variation co-evolve. Epigenetic plasticity does not completely buffer evolvability and reduce the correlation between fitness and genotype, slowing selection.”

One of the summarized studies found that a transgenerational epigenetic change eventually silenced itself after the 40th copy!

The Are stress-induced epigenetic changes to DNA inherited across generations? study was cited, although it argued for the opposing viewpoint.

http://journal.frontiersin.org/article/10.3389/fpls.2015.00699/full “Transgenerational inheritance or resetting of stress-induced epigenetic modifications: two sides of the same coin”

Inflexible behavior may be a byproduct of stress

This 2015 German human study found:

“15-mo-old infants exposed to stress thereafter kept performing a previously effective action, even after the action suddenly became ineffective.

Infants in a no-stress control group flexibly adjusted their behavior by disengaging from the newly ineffective action in favor of exploring an alternative action.

This finding demonstrates that stress impairs infants’ ability to adjust their behavior to changing circumstances.”

The primary measurement of stress levels was cortisol. Stressful conditions were:

  • A stranger sat down next to them;
  • A dancing robot played loud music and moved around;
  • The infant’s caregivers left the room for up to four minutes.

News coverage stated that the study’s design was an adaptation of experiments that produced the same findings in adults. But would adult humans be stressed by being left alone for four minutes?

It’s likely that animal studies were the basis for some of this study’s experiments, as in the If research provides evidence for the causes of stress-related disorders, why only focus on treating the symptoms? study:

“Maternal separation in rodents is a useful model of early-life stress that results in enduring physiological and behavioral changes that persist into adulthood.”

A study limitation was that it involved just 26 infants.

http://www.pnas.org/content/112/41/12882.full “Stress impairs cognitive flexibility in infants”

A study that provided evidence for basic principles of Primal Therapy

This 2015 Northwestern University rodent study found:

“Fear-inducing memories can be state dependent, meaning that they can best be retrieved if the brain states at encoding and retrieval are similar.

Memories formed in a particular mood, arousal or drug-induced state can best be retrieved when the brain is back in that state.

‘It’s difficult for therapists to help these patients,’ Radulovic said, ‘because the patients themselves can’t remember their traumatic experiences that are the root cause of their symptoms.’

The best way to access the memories in this system is to return the brain to the same state of consciousness as when the memory was encoded.”

The study demonstrated one method of activating neurobiological pathways with a drug to remove a hippocampal memory’s protection, which played a part in enabling subjects to relive their remembered experiences. This rodent study’s methods weren’t designed to therapeutically access similarly protected memories with humans.

From the Northwestern press release:

“There are two kinds of GABA [gamma-Aminobutyric acid] receptors. One kind, synaptic GABA receptors, works in tandem with glutamate receptors to balance the excitation of the brain in response to external events such as stress.

The other population, extra-synaptic GABA receptors, are independent agents.

If a traumatic event occurs when these extra-synaptic GABA receptors are activated, the memory of this event cannot be accessed unless these receptors are activated once again.

‘It’s an entirely different system even at the genetic and molecular level than the one that encodes normal memories,’ said lead study author Vladimir Jovasevic, who worked on the study when he was a postdoctoral fellow in Radulovic’s lab.

This different system is regulated by a small microRNA, miR-33, and may be the brain’s protective mechanism when an experience is overwhelmingly stressful.

The findings imply that in response to traumatic stress, some individuals, instead of activating the glutamate system to store memories, activate the extra-synaptic GABA system and form inaccessible traumatic memories.”

I’d point out that “can’t remember” and “inaccessible traumatic memories” phrases used above were in reference to what’s usually called “memory” i.e., a recall initiated by the cerebrum.


The study’s findings should inform memory-study researchers if they care to understand how emotional memories can be formed and re-experienced.

The study provided evidence for fundamentals of Dr. Arthur Janov’s Primal Therapy, such as:

  • Experiences associated with pain can be remembered below our conscious awareness.
  • The retrieval and re-experiencing of emotional memories can engage our lower-level brain areas without our higher-level brain areas’ participation.

The obvious nature of this study’s straightforward experimental methods made me wonder why other researchers hadn’t used the same methods decades ago.

Use of this study’s methodology could have resulted in dozens of informative follow-on study variations by now, and subsequently found whether subjects’ physiological, behavioral, and epigenetic measurements differed from control group subjects, as in:

“miR-33 is downregulated in response to gaboxadol [the drug used to change subjects’ brain state] and modulates its effects on state-dependent fear.”


See Resiliency in stress responses for abstracts of three follow-on papers by these researchers.

http://www.nature.com/neuro/journal/v18/n9/full/nn.4084.html “GABAergic mechanisms regulated by miR-33 encode state-dependent fear”

MP3 with lead researcher Dr. Jelena Radulovic: http://www.thenakedscientists.com/HTML/specials/show/20150825/

Leaky gates, anxiety, and grocery store trips without buying list items

An interview with Jeff Link, the editor of Dr. Arthur Janov’s 2011 book “Life Before Birth: The Hidden Script that Rules Our Lives” with Ken Rose:

“Even further confirmation for some of the views of Janov, that maybe weren’t widely accepted for a time, it’s new research now being done into memory and what a lot of scientist are seeing, a lot of different studies is that memory reactivates the same neuroimpulses that were initially firing off when the event happened.

So a traumatic event when you remember it, the act of remembering it is actually creating a neuromirror of what went on initially.

In a lot of ways that is what Primal Therapy is attempting to do; is to go back to that place and reconnect, or as it’s sometimes referred to, reconsolidate the brain state so that real healing can take place.”

Transcript (part 4 of 6): http://cigognenews.blogspot.com/2015/09/ken-rose-on-life-before-birth-part-46.html

MP3: http://www.pantedmonkey.org/podcastgen/download.php?filename=2011-12-15_1300_what_now_jeff_link.mp3

A hippocampal protein that increases when stress increases

This 2015 Michigan human/rodent study found:

“Gene expression profiling in postmortem human brain and studies using animal models have implicated the fibroblast growth factor (FGF) family in affect regulation and suggest a potential role in the pathophysiology of major depressive disorder (MDD).

We show that FGF9 expression is up-regulated in the hippocampus of individuals with MDD, and that FGF9 expression is inversely related to the expression of FGF2.”

The researchers went down the evolutionary scale from human findings to replicate many of the findings with rodents:

“We found that chronic social defeat stress, an animal model recapitulating some aspects of MDD, leads to a significant increase in hippocampal FGF9 expression.

Collectively, these results suggest that high levels of hippocampal FGF9 play an important role in the development or expression of mood and anxiety disorders.”

http://www.pnas.org/content/112/38/11953.full “Fibroblast growth factor 9 is a novel modulator of negative affect”

Adverse effects of inflammation and stress on hippocampal synapses

This dense and highly-jargoned 2015 rodent study found:

“The suppression of BDNF [brain-derived neurotrophic factor] signaling, LTP [long-term potentiation], and memory may be driven by an increased sensitivity to IL-1β [the proinflammatory cytokine interleukin 1β] that occurs directly at synapses.”

The researchers reversed the adverse effects of IL-1β after they induced stress and inflammation. Blocking IL-1β when there wasn’t stress or inflammation, however, also caused adverse effects:

“Interestingly, administration of AS1 [the compound that blocked the proinflammatory responses] in the absence of LPS [the bacterial compound used to stress the subjects’ immune systems] treatment also impaired OLM [the object location memory test where control group rodents exhibited a preference for a novel location over a familiar location].

This finding is consistent with the notion that endogenous IL-1β at physiologically low levels may be essential for hippocampal memory function.”


The researchers asserted:

“Our data reveal a previously unidentified mechanism that explains the age-related vulnerability of hippocampal function to impairment by inflammation.”

Instead of couching their findings with a non-causal “age-related” term, could the researchers have specifically identified causes?

“IL-1β activates different pathways via AcP (proinflammatory) or AcPb (prosurvival) IL-1 receptor subunits.

This study demonstrates that the IL-1 receptor subunit system undergoes an age-dependent reconfiguration in hippocampal synapses.

This previously undescribed reconfiguration, characterized by an increase in the AcP/AcPb ratio, is responsible for potentiating impairments of synaptic plasticity and memory by IL-1β.”

What were the underlying causes for the relatively increased AcP activation over AcPb activation? The researchers didn’t say. Their explanations were left hanging at a correlated-but-not-causal “age-dependent” level rather than a “mechanism that explains.”

http://www.pnas.org/content/112/36/E5078.full “Synapse-specific IL-1 receptor subunit reconfiguration augments vulnerability to IL-1β in the aged hippocampus”

Who’s responsible for your physical and emotional health?

This 2015 Houston human study measured 575 metabolites in 72 biochemical pathways. The researchers used “nontargeted metabolomics” with next-generation gene sequencing to:

“Take account of human individuality in genes, environment, and lifestyle for early disease diagnosis and individualized therapy.”

The 80 subjects were 45 men and 35 women, average age of 54, in “normal health with complete medical records and three-generation pedigrees.” The subjects all had college degrees, and were members or spouses of members of an upper-level socioeconomic organization.

The study’s range of 575 metabolites certainly cast a shadow over studies such as Running a marathon, cortisol, depression, causes, effects, and agendas that singled out 1 metabolite and tortured its data until it confessed a relationship that supported the preferred agenda.


Limitations of this study that weren’t mentioned by the researchers included:

  1. There were no specific target levels for each metabolite, which could lead to a misinterpretation that a “healthy” blood plasma level of a metabolite would always be the norm of the 80 subjects. This interpretation of each metabolite’s ideal level could be reinforced by the study calculating z-scores and P values of each individual’s measurement’s position within the cohort. The researchers stated:

    “The identification of abnormal metabolic signatures was restricted by the relatively small number of subjects in the cohort.”

    but that limitation wasn’t the flip side of omitted optimal levels.

  2. The metabolite measurements were mainly a one-time event although a series of measurements may have been more appropriate. Many of these metabolite levels vary with the time of day, what each individual had recently eaten, what each individual’s recent stress levels were, etc. This limitation may have been one of the sources for what the researchers noted:

    “Statistical analysis revealed a considerable range of variation and potential metabolic abnormalities across the individuals in this cohort.”

  3. There was no assessment of the relative contributions of epigenetic and genetic factors when discussing possible genetic impacts.

Regarding 1. above:

  • It may be interesting to compare an individual to their peers and to other sources of information. However, when it comes time for “individualized therapy” because of a metabolic measurement that’s an outlier compared to these other sources, an individual’s history also matters.
  • Each individual’s history could be used as a guide for optimal levels of some metabolites. For example, an optimal goal for “individualized therapy” for low testosterone levels of each of the 54-year old male subjects could be each individual’s previous higher levels of three decades earlier. It wouldn’t make sense for a 54-year old male to start testosterone therapy with a goal of raising his low levels to the non-therapeutic, low-level norm of other 54-year old males.

Regarding 2. above:

Regarding 3. above:

  • As an example of unconsidered epigenetic factors, there was a discussion of acetaminophen metabolites because:

    “The identification of at-risk populations could improve therapeutic options for individual patients and prevent adverse clinical outcomes.”

    The researchers specifically compared and contrasted two subjects with the highest levels of acetaminophen metabolites, and concluded:

    “These observations may suggest that volunteer 3976 was sensitive to acetaminophen-induced liver injury, whereas volunteer 3958 could tolerate acetaminophen well. This difference may relate to their cellular capability to maintain GSH [reduced glutathione] levels in response to acetaminophen. We searched for a genetic basis of this variation in acetaminophen degradation/toxic metabolism without success.”

  • The researchers shouldn’t have left the discussion hanging at this point. There’s no reason in 2015 for researchers to not investigate the contribution of epigenetic factors to:

    “Take account of human individuality in genes, environment, and lifestyle.”


I was put off by the researchers statement:

“The volunteer’s cardiologist was informed of this observation to monitor possible drug interaction or toxicity.”

It appeared that the researchers bypassed one subject and informed the subject’s doctor directly when the subject was doing something the researchers considered detrimental to the subject’s health. I don’t know if the subject gave prior consent to be bypassed, though, because I didn’t see either study’s consent terms in the below linked material.


A few concluding questions:

  • If it’s alright for personal health information to be transmitted without the consent of highly-educated, upper-level socioeconomic subjects, what can the rest of the population expect?
  • Is “individualized therapy” best done through individual choices, or by forcing an individual to conform to expert opinion?
  • Who is responsible for an individual’s physical and emotional health?

http://www.pnas.org/content/112/35/E4901.full “Plasma metabolomic profiles enhance precision medicine for volunteers of normal health”

http://www.pnas.org/content/110/42/16957.full “Personalized genomic disease risk of volunteers” (2013 original study with the same subjects)

Reflections on my four-year anniversary of spine surgery

At age 55, I found out that I’d suffered for maybe 45 to 50 years from a childhood injury, and I didn’t know anything about it. It still seems unbelievable to me that I was physically ill for decades before I received a diagnosis.

As explained to me by two surgeons, the cause of my spondylolisthesis between L5 and S1 was a sudden injury sometime between ages 5 and 10. Here’s a further explanation:

“In children, spondylolisthesis usually occurs between the fifth bone in the lower back (lumbar vertebra) and the first bone in the sacrum (pelvis) area. It is often due to a birth defect in that area of the spine or sudden injury (acute trauma).

Other causes of spondylolisthesis include bone diseases, traumatic fractures, and stress fractures (commonly seen in gymnasts). Certain sport activities, such as gymnastics, weight lifting, and football, put a great deal of stress on the bones in the lower back. They also require that the athlete constantly overstretch (hyperextend) the spine.”

I played a lot of baseball when I was a kid growing up in Miami. I didn’t suffer from a birth defect or bone disease, play football before I was a teenager, do gymnastics, or lift weights.

I don’t remember a specific “sudden injury (acute trauma)” per the above explanation. Maybe I incurred the acute trauma that started my spondylolisthesis sliding into bases playing baseball. Maybe I incurred it playing in the other rough-and-tumble activities that I did as a boy.


Please stop at the first hint of any pain that you feel while reading the rest of this post. I don’t want to cause you pain.

I re-experienced while in Primal Therapy a day when I was seven or eight years old. A most exhilarating day, one that filled me with light and joy.

What brought on my elevated mood? It was the day I finally ran faster than my father did, and he couldn’t catch me to give me a beating as I ran out of the house.

My father never beat me on the sidewalk, the street, or the front yard anyway. That would make the abuse public.

My father’s job was assistant principal/dean of boys at West Miami Junior High School. He whipped boys with a thick belt or paddled them daily as part of his job requirements.

My father kept a wooden paddle with holes in it at home. For me.

I don’t remember that my three siblings ever received a paddling or belting, although they were spanked. I’ve remembered while in Primal Therapy that my younger sister and brother were spanked for crying.

I re-experienced the dread of waiting (in an exact place with visual details), waiting for my father to come home to administer a spanking or belting or paddling to me for some “transgression” my mother observed. She had dozens of rules of conduct for her children.

I re-experienced my early childhood feelings that my father’s punishments depended more on my mother’s mood than on what I did.

I re-experienced my early childhood feelings that I didn’t deserve the beatings. I didn’t deserve any beatings, not one!

My father continued, though, until I was around age 11 or so. I’m sure that the beatings were a factor in how I felt at age 12:

Suicidal. Needing to escape from my life.

When I was a child, I needed my parents’ love.

I re-experienced many times while in Primal Therapy the overwhelming hopelessness, helplessness, worthlessness, and betrayal when the people I needed to love me were cruel to me instead.


My parents knew what they did was wrong. Neither one of them ever told me that, though.

My father never apologized for beating me so much before he died 19 years ago. Even before he retired, 17 years before he died, the Miami-Dade County public school system stopped him and the rest of their employees from spanking, whipping, beating, and paddling children.

What could he even tell me to take away those experiences?

  • That he beat me as a child because he himself was beaten as a child?
  • That he couldn’t help it?
  • That how he and my mother frequently went out of their way to help me along in life after my childhood somehow made up for the beatings?

I’m certain that my father was beaten as a child. I bring this up not as a defense for what he did, but as part of my history, too.

It wasn’t enough for my father’s mother to beat me while she was babysitting my siblings and me at our parents’ house. I re-experienced crying as a five-year old when I was required to go cut off palm fronds from the tree in front of our house for her to use as a switch, and bring them to her.

It was a mark of my grandmother’s cruelty that she threatened to beat me with a broom handle when I tried to not participate in my own torment. I re-experienced exact places of my legs where she switched me with the palm fronds, giving me even more when I cried during the punishment.


These wounds left scars that haven’t gone away.

Run your hand down your spine until you reach the top of your sacrum. That’s the area on which I had surgery four years ago, where I now have a titanium cage, replacement disc, and two rods to keep the area stable.

I received a lot of beatings pretty close to that area. Maybe my boyhood activities didn’t cause the “sudden injury (acute trauma).”


I write frankly about my parents because that’s my history: the realities of who they were.

And the realities of who I needed them to be.

I express it because getting well has to address reality.

From Dr. Arthur Janov’s book, Primal Healing, page 133:

“Another cognitive technique is to help the patient understand and forgive his parents. ‘After all, your parents did the best they could. They had a pretty tough childhood too.’ ‘Oh yes, I understand. They did have it tough and I do forgive’ comes forth from the left side. Still, of course, the right side is crying out its needs and its pain, and will go on with its silent scream for the rest of our lives.

There is no way around need.

‘Forgiveness’ is an idea that has no place in therapy.

We are not here to pardon parents; we are here to address the needs of patients, and what the lack of fulfillment did to them.

I regret to say that much of current therapy and particularly cognitive therapy is about a moral position; well hidden, couched in psychological jargon, but, at bottom, moralizing. The therapist becomes the arbiter of correct behavior.

After all, the therapist is trying to change the patient’s behavior toward some preconceived goal. That goal has a sequestered moral position.”