Failed aging paradigms

A 2024 paper with 81 coauthors presented different views of aging:

“This article highlights the lack of consensus among aging researchers on fundamental questions such as the definition, causes, and onset of aging as well as the nature of rejuvenation. Our survey revealed broad disagreement and no majority opinion on these issues.

We obtained 103 responses (∼20% of which were submitted anonymously). The respondents included 29.8% professors, 25% postdoctoral fellows, 22.1% graduate students, 13.5% industry professionals, and 9.6% representing other categories (a total of eight additional groups).

When does aging begin? At 20 years (22%), gastrulation (18%), conception (16.5%), gametogenesis (13%), 25 years (11%), birth (8%), 13 years (5%), and 9 years (4%). Nobody chose the only remaining option (30 years).

m_pgae499f3

It is clear from responses that aging remains an unsolved problem in biology. While most scientists think they understand the nature of aging, apparently their understanding differs. Where some may stress the importance of targeting underlying mechanisms, others focus on ameliorating the phenotypes.”

https://academic.oup.com/pnasnexus/article/3/12/pgae499/7913315?login=false “Disagreement on foundational principles of biological aging”


I’ll assert that these researchers were unable to incorporate information outside of their chosen paradigm. This would explain why only 18% understood the embryonic stage of gastrulation as aging’s start, although the 2022 paper Epigenetic profiling and incidence of disrupted development point to gastrulation as aging ground zero in Xenopus laevis provided epigenetic clock evidence that:

“It is not birth, marriage, or death, but gastrulation which is truly the most important time in your life.”


I’ve cited Josh Mitteldorf’s work about aging a few times. His paradigm of aging is in his 2017 book Cracking the Aging Code: The New Science of Growing Old – And What It Means for Staying Young that:

“Aging has an evolutionary purpose: to stabilize populations and ecosystems.”

However, there isn’t evidence of such causal inheritance mechanisms that would begin an organism’s aging during embryogenesis, i.e., that an embryo’s development of aging elements at gastrulation is causally affected by population and ecosystem factors.


Dr. Goodenowe recently had a casual conversation Episode 8 – Perpetual Health, Exploring The Science Behind Immortality where he asserted items such as:

“What we’re all fighting is entropy. Entropy is the tendency of all things to reach a level of randomness. Aging is not a disease. It’s just apathy and entropy. The body just doesn’t care – people don’t pay attention.

This notion that we are programmed for death is wrong. We’re not programmed to die. We actually teach ourselves to die. The body learns how to die, so as your function decreases, it adjusts. It appears to be programmed because of the association with chronological age.”

I haven’t seen any of his papers that put these and his other assertions up for review. For example, I doubt the entropy-caused randomness assertion would survive peer review per Stochastic methylation clocks?:

“Entropic theories of aging have never been coherent, but they are nevertheless experiencing a resurgence in recent years, primarily because neo-Darwinist theories of aging are all failing. I find this ironic, because the neo-Darwinist theories arose precisely because scientists realized that the Second Law of Thermodynamics does not apply to living systems.”


The funny thing about failed aging paradigms is that quite a few of their treatments improve healthspan, but not lifespan. If they don’t “target aging underlying mechanisms” they “ameliorate aging phenotypes.” None so far have positively affected both human healthspan and lifespan.

PXL_20241129_174732711.MP~2

An elevator pitch for plasmalogen precursors

An excerpt from the latest video at Dr. Goodenowe’s Health Matters podcast, Episode 7 “The Truth about Parkinson’s”, starting at 50:30:

“What’s exciting about this community medicine focus that we’ve switched to which basically says: How do we develop technologies in a way that they can be incorporated into a community model versus a pharmaceutical drug model? People can actually do I would say self-experiment just the way you self-experiment with your own diet because these are fundamentally dietary nutrition molecules.

Could you give me an elevator pitch because there are probably people listening who are thinking what is this plasmalogen precursor and for sure how is it having this dramatic effect?

Plasmalogens are the most important nutrient that nobody knows about. Normally you don’t know about it because the body is usually pretty good at making them. What makes plasmalogens unique is that your body makes them kind of like cannon fodder, the first group of people that go into war. Your body throws them out for destruction. They absorb oxidative stress and get destroyed in the process.

They’re stored in your cell membranes. 50% of the membranes of your heart are these plasmalogen molecules. When your heart gets inflamed, what your heart does is it dumps these plasmalogens out of its membranes to douse the flame of inflammation. After inflammation is under control, your body naturally builds these things back up again.

But if you have an inability to make enough plasmalogens, these inflammation events knock you down and keep you down. So plasmalogen precursors are critical for maintaining high levels of plasmalogens across your body, not just in your brain (30% of the lipids in your brain) but in your heart, your lungs, your kidneys.”


PXL_20241117_185248742~2

Sulforaphane in a tablet?

A 2024 randomized placebo-controlled human study by the product manufacturer investigated enteric-coated sulforaphane:

“The safety, tolerability, and pharmacokinetics of an enteric-coated tablet formulation of SFX-01 were evaluated in a randomized, double-blind, placebo-controlled, dose-escalation study [300 mg once daily (46.2 mg sulforaphane (SFN)), 300 mg twice daily or 600 mg once daily (92.4 mg SFN)] over 7 days in healthy male participants. Treatment-emergent adverse events occurred in 94% of participants who received SFX-01 and were most commonly gastrointestinal events.

The observed peak blood concentration (Cmax) for the sum of SFN and metabolites (total thiol) across all treatment cohorts ranged from 0.43 to 2.12 µmol/L in 3–6 hours. Urinary excretion of SFN and individual metabolites ranged from < 1 to 41%, and the proportion excreted did not appear to be influenced by the dose.

12325_2024_3018_Fig2_HTML

Pharmacokinetic analyses demonstrated that the behavior of SFX-01 enteric-coated tablets was in line with expectations (i.e., rapid absorption following a lag phase attributed to the enteric coating on the tablet formulation), and individual Cmax and AUC values for combined SFN and metabolites were within the range required for pharmacological activity based on in vitro data. Future studies in relevant patient populations/disease indications will look to evaluate pharmacodynamics and target engagement.”

https://link.springer.com/article/10.1007/s12325-024-03018-1 “A Phase 1 Randomized, Placebo-Controlled Study Evaluating the Safety, Tolerability, and Pharmacokinetics of Enteric-Coated Stabilized Sulforaphane (SFX-01) in Male Participants”


This study’s referenced a 2017 study for:

“The proportion excreted via the urine in this study (15–60%) broadly agreed with a 2017 report in which 10 patients were administered 200 µmol of SFN in a 1:1 alpha-cyclodextrin solution, and a mean excretion of 62.3% of the administered dose was measured.”

I’ve curated that 2017 study several times, such as in the second discussion topic of Microwave broccoli seeds to create sulforaphane.

I’m sure these researchers feel that they did a good job for their sponsor. But this current study didn’t address items that would advance science past the 2017 study done at a lower 35 mg dose. For example:

  1. Why did subject bioavailability vary from < 1 to 41% as measured by urinary excretion of sulforaphane and metabolites? The 62.3% average of the 2017 study was meaningless considering those subjects varied from 86.9% to 19.5% (> 400% higher).
  2. Why did subject peak blood concentration vary from 2.12 to 0.43 µmol/L (almost 500% higher)? These researchers knew that would happen as the 2017 study subjects varied from 2.032 to 0.359 μmol (over 500% higher).
  3. Why did almost all (94%) subjects have adverse reactions to the 46.2 to 92.4 mg sulforaphane doses? 60% of the 2017 study subjects also had adverse reactions to a lower 35 mg dose. In what normal situation would people want to take tablets that made them nauseous?

PXL_20241101_192705828

Do broccoli sprouts help treat colonic inflammation?

A 2024 human study investigated broccoli sprouts’ effects as an adjunct to ulcerative colitis treatment:

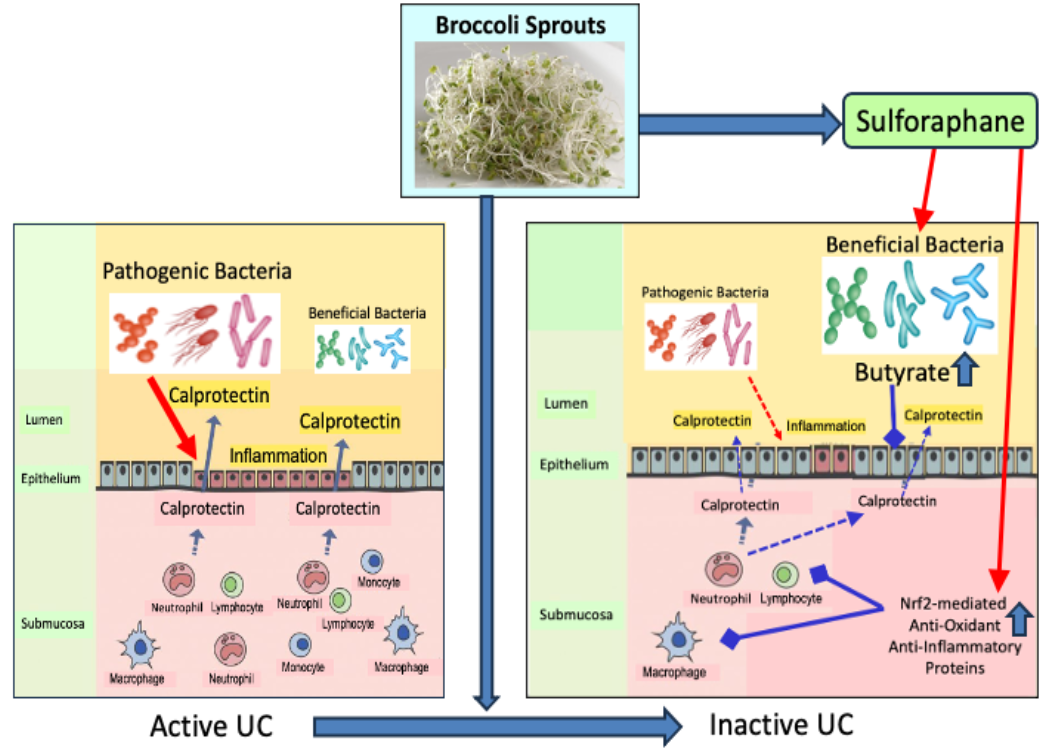
“A dietary approach with sulforaphane (SFN)-rich broccoli sprouts (BS) mitigates colonic inflammation in human ulcerative colitis (UC) patients treated with mesalazine. Subjects were instructed to take 20 g of raw BS or alfalfa sprouts (AS) daily for 8 weeks, with BS containing 4.4 mg/g glucoraphanin, a precursor of sulforaphane, and AS containing no glucoraphanin.

Our findings indicate that the positive effects of SFN-rich BS may be driven by activation of the Nrf2-dependent antioxidant system, which helps combat chronic oxidative stress.

broccoli sprouts and ulcerative colitis

Instead of using glucoraphanin tablets, we used raw BS in our study. Most of the glucoraphanin in BS is converted to biologically active SFN by myrosinase activity in raw BS during chewing BS in the oral cavity. The rest of the glucoraphanin is converted into biological active SFN by myrosinase activity in intestinal microbiota.

Oral intake of BS induces much higher concentrations of systemic SFN compared to taking the same amount of oral glucoraphanin tablets. Another clinical trial using pure SFN, such as via glucoraphanin tablets, instead of using BS, must be conducted.”

https://www.ffhdj.com/index.php/ffhd/article/view/1440/4044 “Dietary intake of sulforaphane-rich broccoli sprouts decreases fecal calprotectin levels in patients with ulcerative colitis”


This study’s daily 20 grams of broccoli sprouts and 88 mg (4.4 mg x 20) glucoraphanin is about what I take, with red cabbage sprouts (which also contain glucoraphanin) and mustard sprouts comprising the other two thirds of total 60-65 grams. Sulforaphane amounts weren’t calculated, as they depend on whether sprouts were eaten with other foods (I’ve eaten them alone since Week 19), how thoroughly sprouts were chewed (I chew each mouthful for at least a minute before swallowing), the presence of certain gut microbiota, sprout age, and other factors.

PXL_20241006_161510628

Brain restoration with plasmalogens, Part 2

This September 2024 presentation adds data points and concepts to Part 1:

supplementation

  1. “Your brain is dynamically connected to and adaptively responsive to its environment.
  2. You are in control of this environment (nutrition, stimulation, adversity).
  3. Need to measure the environment (lab testing, physiology) and adaptive response to the environment (MRI) to optimize your environment (nutrition, lifestyle) to achieve optimal brain structure, function, health, and longevity.

neurovascular

From a global cortical volume and thickness perspective, 17 months of high dose plasmalogens reversed about 15 years of predicted brain deterioration. 31 months reversed almost 20 years. So you can get more out of life.”

https://drgoodenowe.com/immortal-neurology-building-maintaining-an-immortal-brain/


Dr. Goodenowe also added case studies of two patients:

1. A 50-year-old woman with MS who had been legally blind in one eye for 32 years who regained sight in that eye after eight months of supplementation.

“This is the adaptability of the human brain. Her eye is not actually impaired. What’s impaired is the ability, the adaptability of the brain to the signal of light, to actually start interpreting what that light signal is.”

2. A 61-year-old man with dementia from firefighting work for the U.S. Navy in a toxic environment with head injuries after nine months of supplementation.

“The brain can heal itself is the point of the story. His executive function skills in everyday life are getting better.”

Activate Nrf2 to reduce biological age

A 2024 primate study investigated effects of an off-patent drug on age-related changes:

“We evaluated geroprotective effects of metformin on adult male cynomolgus monkeys. The study encompassed a comprehensive suite of physiological, imaging, histological, and molecular evaluations, substantiating metformin’s influence on delaying age-related phenotypes at the organismal level.

monkey nrf2

Results highlighted a significant slowing of aging indicators, notably a roughly 6-year regression in brain aging. Metformin exerts a substantial neuroprotective effect, preserving brain structure and enhancing cognitive ability.

Geroprotective effects on primate neurons were partially mediated by activation of Nrf2, a transcription factor with anti-oxidative capabilities.”

https://www.cell.com/cell/abstract/S0092-8674(24)00914-0 “Metformin decelerates aging clock in male monkeys” (not freely available). Thanks to Dr. Pradeep Reddy for providing a copy.


From this study’s Nrf2 activation findings:

“Metformin treatment resulted in increased nuclear phosphorylated Nrf2, accompanied by up-regulation of Nrf2 target genes like HO-1, NQO-1, SOD3, GPX2, and GPX1, which were generally suppressed and typically down-regulated during human neuron senescence.

Genes pivotal for neuronal function, such as dendrite morphogenesis/extension and synapse assembly (e.g., GSK3B, GRID2, and NRG3), were down-regulated during aging in excitatory neurons (ExN), inhibitory neurons (InN), oligodendrocytes (OL), oligodendrocyte progenitor cells (OPC), microglia, and astrocyte but were restored by metformin treatment. By contrast, pathways that were up-regulated during aging, including activation of the immune response, complement activation, and regulation of the TGF-b receptor signaling pathway, were reset to lower levels by metformin treatment.

metformin neuronal gene pathways

We verified that markers associated with brain aging and progression of neurodegenerative diseases were restored by metformin treatment to levels similar to those observed in young monkeys. Additionally, we observed that reduced myelin sheath thickness, a characteristic of aged monkeys, was rebuilt to a younger state following metformin treatment.

These findings align with the levels of nuclear-localized phosphorylated Nrf2, suggesting that Nrf2 pathway activation is a key mechanism in metformin’s role in delaying human neuronal aging and, by extension, brain aging. Consistent with our in vitro findings, Nrf2 pathway activation was also detected across multiple tissues in metformin-treated monkeys, including frontal lobe neurons.


At last count, I’ve curated 250+ papers this decade on cruciferous vegetables, and many of these explored relationships with Nrf2 activation. Basically, eating a clinically-relevant daily dose of 3-day-old cruciferous sprouts and taking off-patent metformin both induce Nrf2 activation effects.

Don’t expect to see many researchers highlighting this equivalency. They’d rather wait another decade to nitpick other studies with not-enough-subjects / not-exactly replicated / other nitpicks before expressing opinions urging caution from their nursing home beds.

But even then, they won’t get their facts straight. For example, a contemporaneous opinion article https://www.nature.com/articles/d41586-024-02938-w “The brain aged more slowly in monkeys given a cheap diabetes drug” attempted to summarize this study, and flubbed two points:

1. The study said: “We conducted a proof-of-concept study involving male cynomolgus monkeys (Macaca fascicularis) aged between 13 and 16 years, roughly equivalent to approximately 40–50 years in humans. Monkeys adhered to this regimen for a period of 1,200 days, approximately 3.3 years, which corresponds to about 10 years in humans.”

The opinion claimed: “Animals took the drug for 40 months, which is equivalent to about 13 years for humans.”

2. The opinion quoted a New York City researcher involved in a separate metformin study and employed at a medical school for:

“Research into metformin and other anti-ageing candidates could one day mean that doctors will be able to focus more on keeping people healthy for as long as possible rather than on treating diseases.”

This statement is a big break from the realities of medical personnel daily actions at least so far this decade, which is when I started to pay close attention:

  • Doctors have very little diet and exercise training in medical school. There’s no way they can give health advice. There’s no way that a “keeping people healthy” paradigm will emerge from the current medical system.
  • Fixing a disease doesn’t restore a patient’s health. Dr. (PhD) Goodenowe cites several examples in his talks, such as a study that compared colorectal cancer therapy with post-operation patient health.
  • If you listen to yesterday’s two-hour-long podcast, the currently injured person in the first hour gave plenty of contrary evidence of doctors’ focuses: behaviors of trying to blame and gaslight the patient, thinly-disguised punitive actions, CYA etc., all of which they will be sued for one day. The doctor in the second hour provided an example of the quoted researcher in her explanation of how doctors higher in the hierarchy either can’t see or can’t admit realities of doctor/patient interactions, and what therapies have actually benefited or harmed a patient.

The largest cause of coincidences

Good luck finding reporting of this September 2024 medical malpractice (first hour) outside of uncensored social media. Followed in the second hour by how common this type of hospital care is.

1:04:30 Interviewee, who risked her career for stating the truth about what she saw: “Sometimes I don’t even have words.” Interviewer: “For how stupid it is.”

See Part 2 for a longer interview with Dr. Suzanne Humphries.


PXL_20240908_181153475

Eat broccoli sprouts to help repair nerve damage

A 2024 rodent study investigated sulphoraphane’s capability to enhance injured peripheral nerve regeneration:

“We provide in vivo evidence for the regenerative potency of sulforaphane (SFN) for peripheral nerve injury. This effect appears to be predominantly based on the ability of SFN to activate the Nrf2 transcription factor and its versatile downstream effector, HO-1, in cells of the peripheral nerve, in particular Schwann cells.

With regard to translational implications, we chose a dosage of SFN in our mouse model that corresponds to a human equivalent dose of approximately 50–100 mg per day. This dosage of SFN is well achievable with commercially available dietary supplements.

nrf2 and ho-1 expression

Regenerative benefits of Nrf2/HO-1 activation in the peripheral nerve were previously established in a study using dimethyl fumarate (DMF). Due to the immunosuppressive effects of DMF and its potential side effects such as gastrointestinal effects and flushes, this drug can only be used to a limited extent to promote nerve regeneration.

Given the ubiquitous expression and versatile actions of HO-1, our findings suggest that SFN may also be beneficial for neuropathies in general. As a downstream effector of IL-10, the protective and regenerative potency of HO-1 may also apply to inflammatory neuropathies in particular.

SFN sustains the Nrf2/HO-1 pathway, promoting nerve regeneration and facilitating Schwann cell functions, which may include survival, proliferation, and autophagy for myelin debris clearance. These findings suggest that SFN could serve as a valuable therapeutic approach for addressing peripheral nerve injuries, neuropathies, and inflammatory neuropathies, potentially offering renewed prospects for patients contending with these debilitating conditions.”

https://www.mdpi.com/2076-3921/13/9/1038 “Enhancement of Heme-Oxygenase 1 in the Injured Peripheral Nerve Following Sulforaphane Administration Fosters Regeneration via Proliferation and Maintenance of Repair Schwann Cells”


A human-equivalent to this study’s daily 10 mg sulforaphane dose is (10 mg x .081) x 70 kg = 57 mg, albeit the mouse dose was injected intraperitoneally. These researchers apparently hedged their human equivalent of “approximately 50–100 mg per day” to account for administration method differences in bioavailability between oral and intraperitoneal.

PXL_20240628_093554057

Fourteen cruciferous microgreens

A 2024 study investigated beneficial properties of cruciferous microgreens grown for 12 days:

“Fourteen microgreens were ranked morphologically, phytochemically, and sensorially: (A) watercress, (B) broccoli, (C) pak choi, (D) red cabbage, (E) tatsoi, (F) red mizuna, (G) green mizuna, (H) white mustard, (I) red mustard, (J) purple-top white globe turnip, (K) red globe radish, (L) cauliflower, (M) white cabbage, (N) rocket.

12 cruciferous microgreens

  • Watercress and pak choi microgreens had the highest levels of phenolic compounds.
  • Red mustard and red cabbage microgreens revealed the major content of glucosinolates.
  • Cauliflower microgreens had the highest ascorbic acid, TPC, and consumer acceptance.
  • Radish and cauliflower microgreens topped the quality indices ranking.”

https://www.sciencedirect.com/science/article/abs/pii/S0963996924008822 “Optimal Brassicaceae family microgreens from a phytochemical and sensory perspective” (not freely available) Thanks to Dr. Florencia Alloggia for providing a copy.


This study determined “optimal” in a very broad sense, which didn’t lend itself to specific recommendations. For example:

  • A twelve-day growing duration and individual cultivars were selected with no references to how they were chosen as optimal;
  • Measurements weren’t taken along the way to discover informative compositional changes from a phytochemical and sensory perspective; and
  • Measurements such as ascorbic acid and phenolics after twelve days also didn’t reflect several of these compounds’ reactivities and purposes in earlier plant growth phases.

PXL_20240729_101428384

A heterochromatin loss theory of aging? Or just an unhealthy system?

A 2024 rodent study investigated epigenetic effects of loosening compacted chromatin:

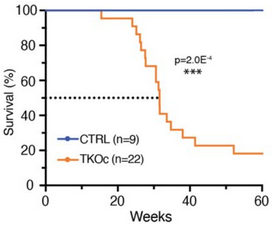
“We show using a novel mouse strain, (TKOc), carrying a triple knockout of three methyltransferases responsible for H3K9me3 deposition, that the inducible loss of H3K9me3 in adulthood results in premature aging. TKOc mice exhibit:

  • Reduced lifespan;
  • Lower body weight;
  • Increased frailty index;
  • Multi-organ degeneration;
  • Transcriptional changes with significant upregulation of transposable elements; and
  • Accelerated epigenetic age.

TKOc survival

Through simultaneous depletion of Setdb1 and Suv39h1/2 methyltransferases, crucial to formation of constitutive heterochromatin, our model analyzes consequential transcription changes including a potential source of genomic instability by activation of endogenous mobile genetic elements, specifically transposable elements.

These findings reveal the importance of epigenetic regulation in aging, and suggest that interventions targeting epigenetic modifications could potentially slow down or reverse age-related decline.”

https://www.biorxiv.org/content/10.1101/2024.07.24.604929v1.full “Loss of H3K9 trimethylation leads to premature aging”


Many of these findings could be restated without viewing them as age-related, i.e.: failure to maintain an adult’s methyltransferase system results in a loss of health. For example, an unhealthy methyltransferase system indicated by parameters like homocysteine levels (not mentioned) can be reversed to healthy function regardless of age. Healthy vs. unhealthy system function wasn’t the paradigm these researchers operated under, though.


PXL_20240726_101120498

Eat broccoli sprouts to reduce knee pain?

A 2024 preprint published results of feasibility trial NCT03878368:

“High glucosinolate broccoli soup is a novel approach to managing osteoarthritis (OA) that is widely accessible and can be used on a large scale. This study shows that it is an acceptable way of delivering dietary bioactives and has potential for therapeutic benefit.

Limitations of the study:

1. COVID-19 curtailed data collection and restricted sample size below that originally planned, however we remained able to derive meaningful interpretation and meet our original study aims.

2. The study had a short time scale (12 weeks). A longer study would be useful to understand how a long-term intervention might be accepted, important for chronic conditions such as OA.

3. The full sample size fell short of the number anticipated, therefore we were unable to use the data to provide a reliable estimate of sample size for a full trial.

4. Participants were excluded if they did not like broccoli to maximise compliance and retention, and so a food intervention should account for this in future developments. While most patients tolerated the soups well, two patients withdrew because they did not like the soup.”

https://www.medrxiv.org/content/10.1101/2024.06.20.24309233v1.full-text “The BRoccoli In Osteoarthritis (BRIO study) – A randomised controlled feasibility trial to examine the potential protective effect of broccoli bioactives, (specifically sulforaphane), on osteoarthritis”


The glucoraphanin dose used was the highest of three tested in 2017 via NCT02300324:

“This study seeks to quantify the exposure of human tissues to glucoraphanin and sulforaphane following consumption of broccoli with contrasting Myb28 genotypes. Myrosinases are intentionally denatured during soup manufacture. Threefold and fivefold higher levels of sulforaphane occur in the circulation following consumption of Myb28V/B and Myb28V/V broccoli soups, respectively.

6b

Myb28V/V and Myb28B/V broccoli soups contained 452 ± 10.6 μmoles glucoraphanin per 300 mL portion and 280 ± 8.8 μmoles glucoraphanin per 300 mL portion respectively, approximately five- and threefold greater glucoraphanin levels compared to Myb28B/B broccoli soup that contained 84 ± 2.8 μmoles glucoraphanin per 300 mL.

The percentage of sulforaphane excreted in 24 h relative to the amount of glucoraphanin consumed varies among volunteers from 2 to 15%, but does not depend on the broccoli genotype.”

https://onlinelibrary.wiley.com/doi/10.1002/mnfr.201700911 “Bioavailability of Glucoraphanin and Sulforaphane from High-Glucoraphanin Broccoli”


Unlike these two papers, I don’t depend primarily on my gut microbiota for results. Microwaving 3-day-old broccoli sprouts to 60°C to create 80% bioavailable sulforaphane then immediately eating it is way more efficient. If depending on an individual’s gut microbiota to convert glucoraphanin into sulforaphane, the best that can be expected is 15% bioavailability.

Don’t think an osteoarthritis clinical trial that depends on a person’s gut microbiota could have steady, predictable results when there could be more than 700% variability (2% to 15%) among subjects’ sulforaphane conversions. If a treatment subject doesn’t have relief from knee pain, there would have to be additional methods to detect that subject’s effective sulforaphane dose based on their gut microbiota conversion ability. Would these researchers suggest that subject change their gut microbiota? What study has reliable results for that?

PXL_20240628_095215629

Astaxanthin and aging

A 2023 rodent study investigated two NRF2-activating compounds for their effects in increasing median and maximum lifespan:

“In genetically heterogeneous (UM-HET3) mice, the Nrf2 activator astaxanthin (Asta) extended the median male lifespan by 12%. Astaxanthin (Asta) is a naturally occurring xanthophyll carotenoid that is an efficient Nrf2 activator, with potent antioxidant activity, broad health applications, and excellent safety.

Asta is distributed systemically and incorporated into cellular membranes, where it spans and stabilizes the lipid bilayer and reduces lipid peroxidation. Asta localizes in mitochondria and protects against mitochondrial dysfunction.

It has anti-inflammatory properties, showing equivalent efficacy to prednisolone in an animal model. Geroprotective mechanisms of Asta regulate FOXO3, Nrf2, Sirt1, and Klotho, and the influence of Asta on autophagy via modulation of AMPK (a direct upstream regulator of mTOR), PI3K/Akt, and MAPK (JNK and p38) signaling pathways.

The present Interventions Testing Program (ITP) study is the first evaluation of Asta in a mammalian lifespan model, so the target dose of 4000 ppm in the diet is based on chronic mammalian studies other than lifespan. Despite the fact that the average diet contained 1840 ppm Asta (only 46% of the target), median lifespans of male UM-HET3 mice were significantly improved.astaxanthin male survival

Asta and dimethyl fumarate (DMF) are both Nrf2 inducers; while both had low concentrations sometimes in the diet, we used about 30 times more Asta, which may explain why it increased the lifespan in males while DMF had no effect. Amounts of DMF in the diet averaged 35% of the target dose, which may explain the absence of lifespan effects.”

https://link.springer.com/article/10.1007/s11357-023-01011-0 “Astaxanthin and meclizine extend lifespan in UM‑HET3 male mice; fisetin, SG1002 (hydrogen sulfide donor), dimethyl fumarate, mycophenolic acid, and 4‑phenylbutyrate do not significantly affect lifespan in either sex at the doses and schedules used”


This study repeated an astaxanthin supplier’s claims without investigating its low bioavailability issues mentioned in Astaxanthin bioavailability. No explanations were forthcoming for unintentional low doses of astaxanthin and DMF in the treatment chows.

A human equivalent for the intended astaxanthin dose was 22 mg (4000 ppb x .081 x 70 kg), whereas the actual dose human equivalent was 10 mg (1840 ppb x .081 x 70 kg). Dose/response studies weren’t performed, so no conclusions could be drawn as to whether the target dose or other astaxanthin doses may be optimal for increasing lifespan.

A previous ITP study of another commercial NRF2 activator (PB125) found no lifespan benefits. Maybe one day, ITP or others will come around to testing sulforaphane that has 80% bioavailability (regardless of sex) and dose/response studies, which should end the uncertainty about NRF2’s anti-aging effects.

How to choose your medical professional

Two+ decades ago (before smart phones) I wrote a series of short books entitled How To Choose Your  Lawyer, ..Accountant, ..Financial Advisor. My customers were mainly public libraries.

This is a short post on choosing doctors, although I’ve fired all my doctors and don’t have one. Everything that’s happened this decade has made me wonder why I trusted doctors in the first place.

1. It takes certain behavioral quirks for doctors to assert they know better than you do about what is good for you. These behaviors usually have nothing to do with these doctors’ patients, but patients somehow believe doctors.

These behaviors are almost always doctors’ act-outs of early-life traumas of unfulfilled needs. Pain keeps people from feeling their actual histories, though, so we don’t deal with our real histories therapeutically until we absolutely have to.

If your doctor listens to you at all, it’s only because they are constantly vigilant for some way to fulfill their own unsatisfied needs. But that neither resolves anything for them, as an early need can’t be satisfied years later, nor has anything to do with what you need from a medical professional.

2. If you’ve read extensively about an area and have questions, a doctor may know less than you. That won’t keep them from gaslighting you due to 1. above, but it does keep you from getting what you need from them. Discussing facts you know with a medical professional who is intentionally ignorant about a medical subject gets you nowhere.

3. If your doctor has not publicly disclaimed their advocacy of this decade’s misguided genetic therapy, they are compromised and can’t be trusted. It doesn’t matter what else they said, because they weren’t honest about what they knew or should have known, as revealed by their actions or inactions.

For example, two studies published in June 2024 established that:

  • Neurologic issues (68% increase in depression, and a 44% increase in anxiety / dissociative / stress-related / somatoform disorders) followed COVID gene therapy: https://www.nature.com/articles/s41380-024-02627-0 “Psychiatric adverse events following COVID-19 vaccination: a population-based cohort study in Seoul, South Korea” (2,027,353 people)
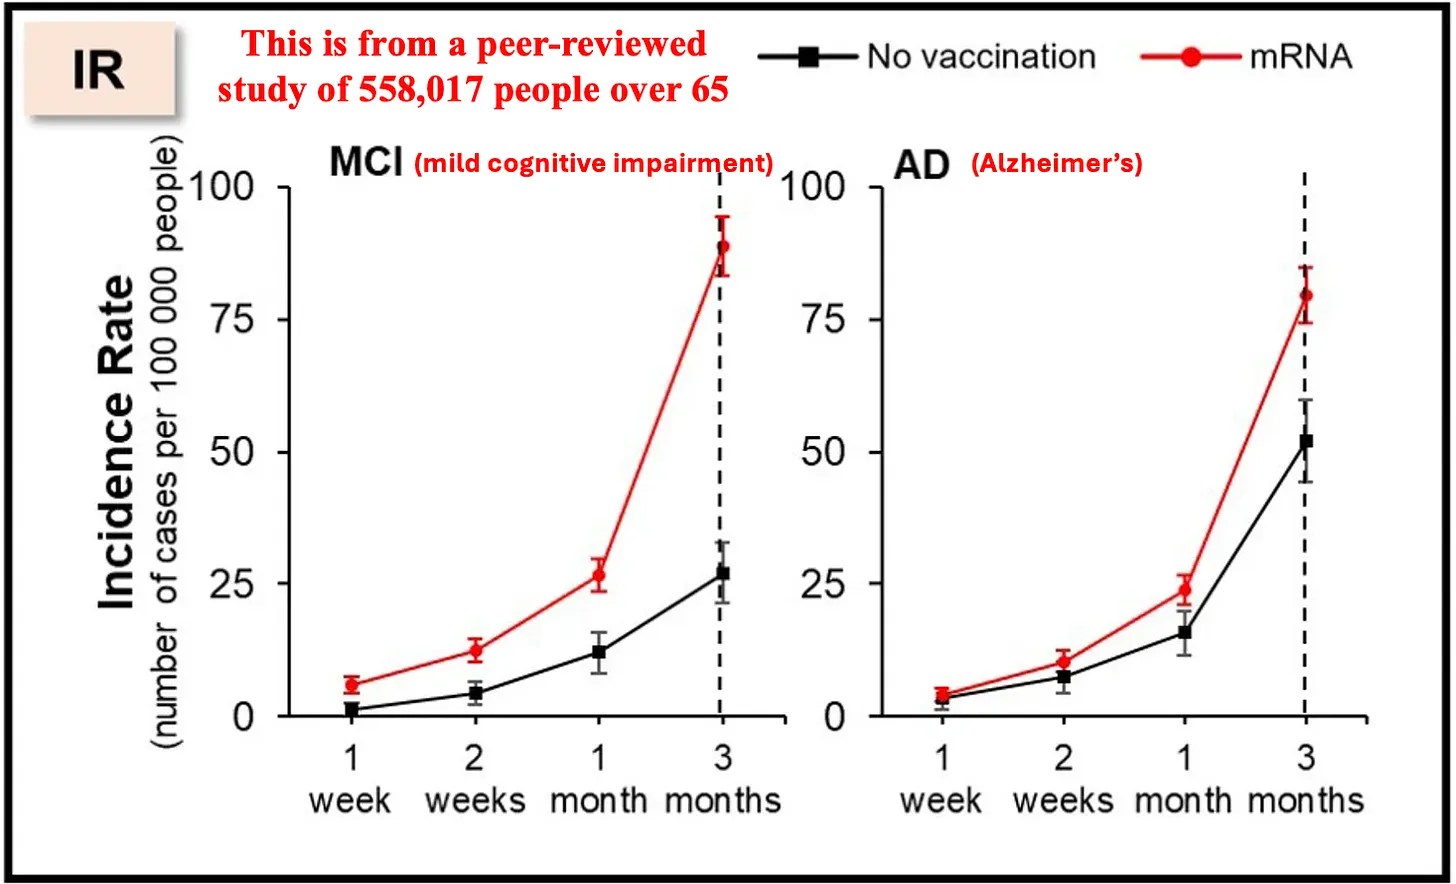
  • COVID gene therapy increased the risk of mild cognitive impairment 138% and the risk of Alzheimer’s by 23%: https://academic.oup.com/qjmed/advance-article-abstract/doi/10.1093/qjmed/hcae103/7684274 “A potential association between COVID-19 vaccination and development of Alzheimer’s disease” (558,017 people). These graphics showed rapidly increasing MCI and AD incidences. The study’s analysis showed incidence increases could not have happened by chance.

ea3f75cb-a071-4cc9-9bd8-0609d0ad8961_1466x890

A doctor’s only honest response to this malfeasance is to publicly apologize, and tell their trusting patients they will make it up to them by providing free healthcare to help mitigate results of their unprofessional conduct. If they tell you something else, it’s a distraction from consequences that are beyond words.

Eat broccoli sprouts to support muscle growth

A 2024 rodent study investigated sulforaphane’s effects on skeletal muscle:

“Sulforaphane (SFN) shows a promising application in skeletal muscle protection and recovery from muscle atrophy and damage. However, limited work has focused on the role of SFN in maintaining the balance of protein and lipid metabolism in skeletal muscle.

The current work investigates effects of SFN at an everyday consumption level on protein and lipid metabolism in skeletal muscle. Investigating SFN at lower levels over an extended period more closely resembles human consumption habits. Four-week-old mice received SFN at a dosage of 1 mg per kilogram of body weight per day (1 mg/kg/d BW) using i.p. injection (SFN1 group) and 3 mg/kg/d BW (SFN3 group) for eight weeks, equivalent to concentrations of 0.14 μM and 0.42 μM.

Histological analysis was performed for the Longissimus dorsi [the largest back muscle]. LD muscle fiber diameter and cross-section area was significantly increased in the SFN3 group, not in the SFN1 group.

SFN muscle growth

The levels of triglycerides and total cholesterol in the LD muscle were found to be decreased in both SFN groups.

This study reported, for the first time, that SFN administration increased peroxisome activity and enhanced the peroxisomal protein shuttle, which supports enhanced peroxisomal fatty acid β-oxidation. SFN redirects the flux of fatty acid to be utilized through β-oxidation in peroxisomes and mitochondria to support muscle growth. Furthermore, SFN treatment influenced lipid and protein metabolism related pathways including AMPK signalling, fatty acid metabolism signalling, cholesterol metabolism signalling, PPAR signalling, peroxisome signalling, TGFβ signalling, and mTOR signalling.”

https://portlandpress.com/bioscirep/article/doi/10.1042/BSR20240084/234562/Sulforaphane-enhanced-muscle-growth-by-promoting “Sulforaphane enhanced muscle growth by promoting lipid oxidation through modulating key signaling pathways”


A human equivalent to this study’s 3 mg daily dose is (3 mg x .081) x 70 kg = 17 mg, albeit doses were intraperitoneally injected. An oral 17 mg is a common sulforaphane floor dose in human studies, and is approximately what I get from eating 60 grams of a microwaved broccoli / red cabbage / mustard 3-day-old sprouts mix daily.

PXL_20240618_094022451

Consequences of perinatal stress

A 2024 rodent study followed up earlier studies of perinatal stress:

“Stress is a multisystemic and multiscale reaction experienced by living beings in response to a wide range of stimuli, encompassing a highly complex order of biological and behavioral responses in mammals, including humans. In the present study, we evaluated changes in mRNA levels in 88 regions of interest (ROIs) in male rats both exposed to perinatal stress and not exposed.

Depending on critical life stage (e.g., perinatal life, infancy, childhood, adolescence, aging), duration, and type of stressor, different effects can be detected by examining behavioral and physiological functions. Stress is related to several cognitive processes, including spatial and declarative memory (involving the hippocampus), fear and memories of emotionally charged events (involving the amygdala), and executive functions and fear extinction (involving the prefrontal cortex).

This PRS paradigm is a well-characterized animal model in which offspring is exposed to stress during pregnancy and after birth because of receiving defective maternal care. Offspring exhibit behavioral hyperreactivity, as well as increased susceptibility to drug addiction and decreased risk-taking behavior.

Starting from day 11 of gestation until delivery, pregnant females were subjected to restraint in a transparent plastic cylinder and exposed to bright light during three daily sessions of 45 min. Since gestational stress induces a <40% reduction of maternal behavior in stressed mothers, we refer to the whole procedure as Perinatal Stress.

Intercorrelation between the orbitofrontal cortex (OFC) and various brain regions such as the thalamus and amygdala were found disrupted in the PRS group. These functional correlations appear to be associated with regulation of executive functions, goal-directed behavior, and directed attention. Also, discrete functional links between the OFC and limbic regions and striatum were lost in the PRS group.

Decreased expression of the Homer1a gene across multiple brain regions after perinatal stress exposure may derange normal architecture of glutamatergic synapses during neurodevelopment and after birth. Changes at the glutamatergic synapse have been considered pivotal in adaptive stress behaviors.

Our results show that PRS preferentially reinforces the centrality of subcortical nodes, resulting in increased centrality of structures such as amygdala, caudate-putamen, and nucleus accumbens, suggestive of reduced cortical control over these regions. In conclusion, when analyzing Homer gene expression after stress exposure not only in terms of quantitative changes compared to the control group, but also as a basis for conducting brain connectivity graph analysis, we observed that perinatal stress could significantly affect the functional connectivity of brain regions implicated in modeling pathophysiology of severe psychiatric disorders.”

https://www.sciencedirect.com/science/article/pii/S0278584624001003 “Perinatal stress modulates glutamatergic functional connectivity: A post-synaptic density immediate early gene-based network analysis”


PXL_20240528_094419674