Reversing hair greying, Part 2

Three papers that cited the 2021 Reversing hair greying study, starting with a 2024 rodent study:

“External treatment with luteolin, but not that with hesperetin or diosmetin, alleviated hair graying in model mice. Internal treatment with luteolin also mitigated hair graying.
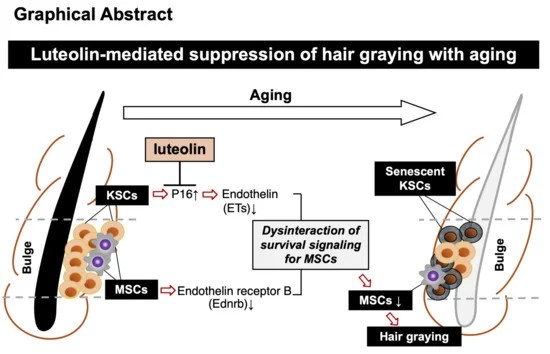
Both treatments suppressed the increase in p16ink4a-positive cells in bulges [senescent keratinocyte stem cells (KSCs)]. Both treatments also suppressed decreases in expression levels of endothelins in KSCs and their receptor (Ednrb) in melanocyte stem cells (MSCs), and alleviated hair graying in mice.”

https://www.mdpi.com/2076-3921/13/12/1549 “Anti-Graying Effects of External and Internal Treatments with Luteolin on Hair in Model Mice”

This study treated subjects internally and externally with luteolin and hesperetin, which are ranked #7 (effective treatment) and #14 (not an effective treatment) per Nrf2 activator rankings. I wonder what these researchers would have found if they used the #1 ranked Nrf2 activator, sulforaphane.


A 2024 review managed to cover the Nrf2 activation subject without mentioning sulforaphane:

“Certain types of hair graying can be prevented or treated by enhancing MSC maintenance or melanocyte function, reducing oxidative stress, and managing secretion and action of stress hormones.

Tactical approaches to pursue this goal may include a selective activation of the p38 MAPK–MITF axis, enhancing cellular antioxidant capacity through activating NRF2, and modulating the norepinephrine–β2AR–PKA signaling pathway.”

https://www.mdpi.com/2076-3417/14/17/7450 “Intrinsic and Extrinsic Factors Associated with Hair Graying (Canities) and Therapeutic Potential of Plant Extracts and Phytochemicals”

This reviewer also avoided citing the 2021 Sulforaphane and hair loss, although hair loss was mentioned multiple times. I suspect that institutional politics was involved, as both papers are from South Korea.


Reference 32 of this review was a 2023 review that covered mainly unintentional hair greying reversal as a side effect noted when people had pharmaceutical treatments for various diseases:

“Hair graying is a common and visible sign of aging resulting from decreased or absence of melanogenesis. It has long been thought that reversal of gray hair on a large scale is rare. However, a recent study reported that individual gray hair darkening is a common phenomenon, suggesting the possibility of large-scale reversal of gray hair.

All these treatments rely on the presence of a sufficient population of active McSCs. Maintaining a healthy population of McSCs is also an urgent problem that needs to be addressed.”

https://www.ijbs.com/v19p4588.htm “Reversing Gray Hair: Inspiring the Development of New Therapies Through Research on Hair Pigmentation and Repigmentation Progress”


I published A hair color anecdote two months into eating broccoli sprouts every day when I first noticed dark hair growing in. Since it’s been over 4 years that I’ve continued eating broccoli sprouts daily, I think it’s alright to stop referring to my continuing reversal of hair greying as an anecdote.

But it was apparently too late to address hair loss, which started before I turned 30. So now you know what to do. 🙂
A sulforaphane review

Here’s a 2025 review where the lead author is a retired researcher whose words readers might interpret as Science. As a reminder, unlike study researchers, reviewers are free to:

  • Express their beliefs as facts;
  • Over/under emphasize study limitations; and
  • Disregard and misrepresent evidence as they see fit.

Reviewers also aren’t obligated to make post-publication corrections for their errors and distortions. For examples:

1. After the 7. Conclusions section, there’s an 8. Afterword: I3C and DIM section. The phrase “As detailed in our earliest work on broccoli sprouts..” indicated a belief carried over from last century of the low importance of those research subjects.

Then, contrary to uncited clinical trials such as Our model clinical trial for Changing to a youthful phenotype with broccoli sprouts and Eat broccoli sprouts for DIM, “Broccoli sprouts had next to no indole glucosinolates.” And in the middle of downplaying I3C and DIM research, they stated: “There are 149 clinical studies on DIM and 11 on I3C listed on clinicaltrials.gov, suggesting a good safety profile. Potential efficacy and mode of action in humans are a subject of intense current investigation, though definitive answers will not come for some time.” 🧐

2. In the 3. Sulforaphane section, they asserted: “Glucosinolates such as glucoraphanin are ‘activated’ or converted to isothiocyanates such as sulforaphane by an enzyme called myrosinase, which is present in that same plant tissue (e.g., seed, sprout, broccoli head, or microgreen) and/or in bacteria that all humans possess in their gastrointestinal tracts.” and cited a 2016 book they coauthored that I can’t access.

The first 2021 paper of Broccoli sprout compounds and gut microbiota didn’t assert that “all humans” had certain gut microbiota that converted glucosinolates to isothiocyanates. That paper instead stated: “Human feeding trials have shown inter-individual variations in gut microbiome composition coincides with variations in ITC absorption and excretion, and some bacteria produce ITCs from glucosinolates.”

3. Nearly half of their cited references were in vitro cancer papers. I rarely curate those types of studies because of their undisclosed human-irrelevant factors. For example, from the second paper of Polyphenol Nrf2 activators:

Bioavailability studies reveal that maximum concentrations in plasma typically do not exceed 1 µM following consumption of 10–100 mg of a single phenolic compound, with the maximum concentration occurring typically less than 2 h after ingestion, then dropping quickly thereafter. In the case of the in vitro studies assessed herein, and with few exceptions, most of the studies employed concentrations >10 µM with some studies involving concentrations in the several hundred µM range, with the duration of exposure typically in the range of 24–72 h, far longer duration than the very short time interval of a few minutes to several hours in human in vivo situations.

applsci-15-00522-g001-550

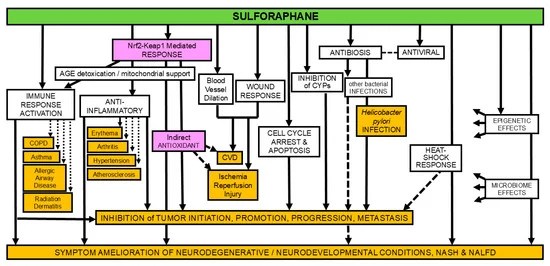
https://www.mdpi.com/2076-3417/15/2/522 “The Impact of Sulforaphane on Sex-Specific Conditions and Hormone Balance: A Comprehensive Review”

Nrf2 activator rankings

A 2024 cell study compared and contrasted findings of previous plant compound Nrf2 inducer studies with a newer assay type:

“Various plants have been reported to contain compounds that promote transcriptional activity of Nuclear factor erythroid 2-related factor 2 (Nrf2) to induce a set of xenobiotic detoxifying enzymes, such as NAD(P)H-quinone acceptor oxidoreductase 1 (NQO1), via the antioxidant response element (ARE). An ARE luciferase reporter assay was recently developed to specifically assess Nrf2 induction potency of compounds.

33 compounds were sorted in the order of their transcriptional activity of Nrf2. CD value is the concentration of a compound required to double the basal activities of individual enzymes or luciferase activity.

nrf2 induction

This study is the first to examine consistency of the transcriptional activity of Nrf2 evaluated using ARE reporter and NQO1 assays for multiple compounds. Future comparisons of CD values by each assay across cell types may be used to demonstrate consistency between the assays, as well as to reveal the factors that influence Nrf2 induction potency.”

https://bmcresnotes.biomedcentral.com/articles/10.1186/s13104-024-07038-6 “Nrf2 induction potency of plant-derived compounds determined using an antioxidant response element luciferase reporter and conventional NAD(P)H-quinone acceptor oxidoreductase 1 activity assay”


A 2019 ranking of sulforaphane with 18 other Nrf2 activators was curated in Part 2 of Rejuvenation therapy and sulforaphane, and pointed out bioavailability differences:
OMCL2019-2716870.006

It [sulforaphane] is not only a potent Nrf2 inducer but also highly bioavailable [around 80%], so that modest practical doses can produce significant clinical responses. Other Nrf2 activators [shown in the above image] not only lack potency, but also lack the bioavailability to be considered as significant intracellular Nrf2 activators.”

This study attempted to explain differences in the two assay findings with numerous “may” and “could” statements. Okay.

But if you want to activate your body’s endogenous detoxification and antioxidant systems with a natural plant compound, sulforaphane remains the number one choice.

PXL_20241223_185836159

Polyphenol Nrf2 activators

Two 2024 reviews by the same group that published Sulforaphane in the Goldilocks zone investigated dietary polyphenols’ effects as “hormetic nutrients”:

“Polyphenols display biphasic dose–response effects by activating at a low dose the Nrf2 pathway resulting in the upregulation of antioxidant vitagenes [see diagram]. We aimed to discuss hormetic nutrients, including polyphenols and/or probiotics, targeting the Nrf2 pathway and vitagenes for the development of promising neuroprotective and therapeutic strategies to suppress oxidative stress, inflammation and microbiota deregulation, and consequently improve cognitive performance and brain health.

antioxidants-13-00484-g001

Hormetic nutrition through polyphenols and/or probiotics targeting the antioxidant Nrf2 pathway and stress resilient vitagenes to inhibit oxidative stress and inflammatory pathways, as well as ferroptosis, could represent an effective therapy to manipulate alterations in the gut microbiome leading to brain dysfunction in order to prevent or slow the onset of major cognitive disorders. Notably, hormetic nutrients can stimulate the vagus nerve as a means of directly modulating microbiota-brain interactions for therapeutic purposes to mitigate or reverse the pathophysiological process, restoring gut and brain homeostasis, as reported by extensive preclinical and clinical studies.”

https://www.mdpi.com/2076-3921/13/4/484 “Hormetic Nutrition and Redox Regulation in Gut–Brain Axis Disorders”


I’m not onboard with this study’s probiotic assertions because most of the cited studies contained unacknowledged measurement errors. Measuring gut microbiota, Part 2 found:

“The fecal microbiome does not represent the overall composition of the gut microbiome. Despite significant roles of gut microbiome in various phenotypes and diseases of its host, causative microbes for such characteristics identified by one research fail to be reproduced in others.

Since fecal microbiome is a result of the gut microbiome rather than the representative microbiome of the GI tract of the host, there is a limitation in identifying causative intestinal microbes related to these phenotypes and diseases by studying fecal microbiome.”

These researchers also erroneously equated isothiocyanate sulforaphane’s Nrf2-activating mechanisms with polyphenols activating Nrf2.


This research group did better in clarifying polyphenols’ mechanisms in a review of hormetic dose-response effects of the polyphenol rosmarinic acid:

“This article evaluates whether rosmarinic acid may act as a hormetic agent, mediating its chemoprotective effects as has been shown for similar agents, such as caffeic acid, a derivative of rosmarinic acid.

Rosmarinic acid enhanced memory in institute of cancer research male mice in the Morris water maze (escape latency).

untitled

Of importance in the evaluation of rosmarinic acid are its bioavailability, metabolism, and tissue distribution (including the capacity to affect and/or cross the BBB and its distribution and half-life within the brain). In the case of polyphenols, including rosmarinic acid, they are typically delivered at low doses in the diet and, in most instances, they do not escape first-pass metabolism, with the prominent chemical forms being conjugates of glucuronides and sulfates, with or without methylation.

These conjugated metabolites are chemically distinct from the parent compound, showing considerable differences in size, polarity, and ionic form. Their biological actions are quite different from the parent compound.

Bioavailability studies reveal that maximum concentrations in plasma typically do not exceed 1 µM following consumption of 10–100 mg of a single phenolic compound, with the maximum concentration occurring typically less than 2 h after ingestion, then dropping quickly thereafter. In the case of the in vitro studies assessed herein, and with few exceptions, most of the studies employed concentrations >10 µM with some studies involving concentrations in the several hundred µM range, with the duration of exposure typically in the range of 24–72 h, far longer duration than the very short time interval of a few minutes to several hours in human in vivo situations.

We strongly recommend that all experiments using in vitro models to study biological responses to dietary polyphenols use only physiologically relevant flavonoids and their conjugates at appropriate concentrations, provide evidence to support their use, and justify any conclusions generated. When authors fail to do this, referees and editors must act to ensure that data obtained in vitro are relevant to what might occur in vivo.”

https://www.degruyter.com/document/doi/10.1515/med-2024-1065/html “The chemoprotective hormetic effects of rosmarinic acid”

Failed aging paradigms

A 2024 paper with 81 coauthors presented different views of aging:

“This article highlights the lack of consensus among aging researchers on fundamental questions such as the definition, causes, and onset of aging as well as the nature of rejuvenation. Our survey revealed broad disagreement and no majority opinion on these issues.

We obtained 103 responses (∼20% of which were submitted anonymously). The respondents included 29.8% professors, 25% postdoctoral fellows, 22.1% graduate students, 13.5% industry professionals, and 9.6% representing other categories (a total of eight additional groups).

When does aging begin? At 20 years (22%), gastrulation (18%), conception (16.5%), gametogenesis (13%), 25 years (11%), birth (8%), 13 years (5%), and 9 years (4%). Nobody chose the only remaining option (30 years).

m_pgae499f3

It is clear from responses that aging remains an unsolved problem in biology. While most scientists think they understand the nature of aging, apparently their understanding differs. Where some may stress the importance of targeting underlying mechanisms, others focus on ameliorating the phenotypes.”

https://academic.oup.com/pnasnexus/article/3/12/pgae499/7913315?login=false “Disagreement on foundational principles of biological aging”


I’ll assert that these researchers were unable to incorporate information outside of their chosen paradigm. This would explain why only 18% understood the embryonic stage of gastrulation as aging’s start, although the 2022 paper Epigenetic profiling and incidence of disrupted development point to gastrulation as aging ground zero in Xenopus laevis provided epigenetic clock evidence that:

“It is not birth, marriage, or death, but gastrulation which is truly the most important time in your life.”


I’ve cited Josh Mitteldorf’s work about aging a few times. His paradigm of aging is in his 2017 book Cracking the Aging Code: The New Science of Growing Old – And What It Means for Staying Young that:

“Aging has an evolutionary purpose: to stabilize populations and ecosystems.”

However, there isn’t evidence of such causal inheritance mechanisms that would begin an organism’s aging during embryogenesis, i.e., that an embryo’s development of aging elements at gastrulation is causally affected by population and ecosystem factors.


Dr. Goodenowe recently had a casual conversation Episode 8 – Perpetual Health, Exploring The Science Behind Immortality where he asserted items such as:

“What we’re all fighting is entropy. Entropy is the tendency of all things to reach a level of randomness. Aging is not a disease. It’s just apathy and entropy. The body just doesn’t care – people don’t pay attention.

This notion that we are programmed for death is wrong. We’re not programmed to die. We actually teach ourselves to die. The body learns how to die, so as your function decreases, it adjusts. It appears to be programmed because of the association with chronological age.”

I haven’t seen any of his papers that put these and his other assertions up for review. For example, I doubt the entropy-caused randomness assertion would survive peer review per Stochastic methylation clocks?:

“Entropic theories of aging have never been coherent, but they are nevertheless experiencing a resurgence in recent years, primarily because neo-Darwinist theories of aging are all failing. I find this ironic, because the neo-Darwinist theories arose precisely because scientists realized that the Second Law of Thermodynamics does not apply to living systems.”


The funny thing about failed aging paradigms is that quite a few of their treatments improve healthspan, but not lifespan. If they don’t “target aging underlying mechanisms” they “ameliorate aging phenotypes.” None so far have positively affected both human healthspan and lifespan.

PXL_20241129_174732711.MP~2

An elevator pitch for plasmalogen precursors

An excerpt from the latest video at Dr. Goodenowe’s Health Matters podcast, Episode 7 “The Truth about Parkinson’s”, starting at 50:30:

“What’s exciting about this community medicine focus that we’ve switched to which basically says: How do we develop technologies in a way that they can be incorporated into a community model versus a pharmaceutical drug model? People can actually do I would say self-experiment just the way you self-experiment with your own diet because these are fundamentally dietary nutrition molecules.

Could you give me an elevator pitch because there are probably people listening who are thinking what is this plasmalogen precursor and for sure how is it having this dramatic effect?

Plasmalogens are the most important nutrient that nobody knows about. Normally you don’t know about it because the body is usually pretty good at making them. What makes plasmalogens unique is that your body makes them kind of like cannon fodder, the first group of people that go into war. Your body throws them out for destruction. They absorb oxidative stress and get destroyed in the process.

They’re stored in your cell membranes. 50% of the membranes of your heart are these plasmalogen molecules. When your heart gets inflamed, what your heart does is it dumps these plasmalogens out of its membranes to douse the flame of inflammation. After inflammation is under control, your body naturally builds these things back up again.

But if you have an inability to make enough plasmalogens, these inflammation events knock you down and keep you down. So plasmalogen precursors are critical for maintaining high levels of plasmalogens across your body, not just in your brain (30% of the lipids in your brain) but in your heart, your lungs, your kidneys.”


PXL_20241117_185248742~2

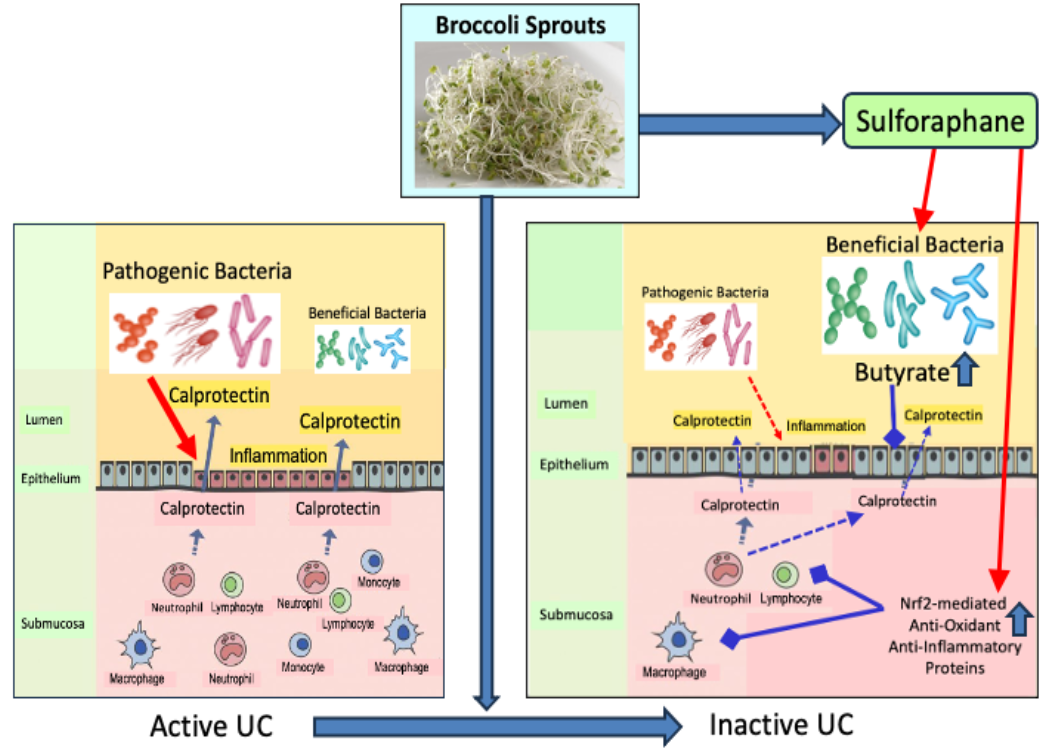
Do broccoli sprouts help treat colonic inflammation?

A 2024 human study investigated broccoli sprouts’ effects as an adjunct to ulcerative colitis treatment:

“A dietary approach with sulforaphane (SFN)-rich broccoli sprouts (BS) mitigates colonic inflammation in human ulcerative colitis (UC) patients treated with mesalazine. Subjects were instructed to take 20 g of raw BS or alfalfa sprouts (AS) daily for 8 weeks, with BS containing 4.4 mg/g glucoraphanin, a precursor of sulforaphane, and AS containing no glucoraphanin.

Our findings indicate that the positive effects of SFN-rich BS may be driven by activation of the Nrf2-dependent antioxidant system, which helps combat chronic oxidative stress.

broccoli sprouts and ulcerative colitis

Instead of using glucoraphanin tablets, we used raw BS in our study. Most of the glucoraphanin in BS is converted to biologically active SFN by myrosinase activity in raw BS during chewing BS in the oral cavity. The rest of the glucoraphanin is converted into biological active SFN by myrosinase activity in intestinal microbiota.

Oral intake of BS induces much higher concentrations of systemic SFN compared to taking the same amount of oral glucoraphanin tablets. Another clinical trial using pure SFN, such as via glucoraphanin tablets, instead of using BS, must be conducted.”

https://www.ffhdj.com/index.php/ffhd/article/view/1440/4044 “Dietary intake of sulforaphane-rich broccoli sprouts decreases fecal calprotectin levels in patients with ulcerative colitis”


This study’s daily 20 grams of broccoli sprouts and 88 mg (4.4 mg x 20) glucoraphanin is about what I take, with red cabbage sprouts (which also contain glucoraphanin) and mustard sprouts comprising the other two thirds of total 60-65 grams. Sulforaphane amounts weren’t calculated, as they depend on whether sprouts were eaten with other foods (I’ve eaten them alone since Week 19), how thoroughly sprouts were chewed (I chew each mouthful for at least a minute before swallowing), the presence of certain gut microbiota, sprout age, and other factors.

PXL_20241006_161510628

Activate Nrf2 to reduce biological age

A 2024 primate study investigated effects of an off-patent drug on age-related changes:

“We evaluated geroprotective effects of metformin on adult male cynomolgus monkeys. The study encompassed a comprehensive suite of physiological, imaging, histological, and molecular evaluations, substantiating metformin’s influence on delaying age-related phenotypes at the organismal level.

monkey nrf2

Results highlighted a significant slowing of aging indicators, notably a roughly 6-year regression in brain aging. Metformin exerts a substantial neuroprotective effect, preserving brain structure and enhancing cognitive ability.

Geroprotective effects on primate neurons were partially mediated by activation of Nrf2, a transcription factor with anti-oxidative capabilities.”

https://www.cell.com/cell/abstract/S0092-8674(24)00914-0 “Metformin decelerates aging clock in male monkeys” (not freely available). Thanks to Dr. Pradeep Reddy for providing a copy.


From this study’s Nrf2 activation findings:

“Metformin treatment resulted in increased nuclear phosphorylated Nrf2, accompanied by up-regulation of Nrf2 target genes like HO-1, NQO-1, SOD3, GPX2, and GPX1, which were generally suppressed and typically down-regulated during human neuron senescence.

Genes pivotal for neuronal function, such as dendrite morphogenesis/extension and synapse assembly (e.g., GSK3B, GRID2, and NRG3), were down-regulated during aging in excitatory neurons (ExN), inhibitory neurons (InN), oligodendrocytes (OL), oligodendrocyte progenitor cells (OPC), microglia, and astrocyte but were restored by metformin treatment. By contrast, pathways that were up-regulated during aging, including activation of the immune response, complement activation, and regulation of the TGF-b receptor signaling pathway, were reset to lower levels by metformin treatment.

metformin neuronal gene pathways

We verified that markers associated with brain aging and progression of neurodegenerative diseases were restored by metformin treatment to levels similar to those observed in young monkeys. Additionally, we observed that reduced myelin sheath thickness, a characteristic of aged monkeys, was rebuilt to a younger state following metformin treatment.

These findings align with the levels of nuclear-localized phosphorylated Nrf2, suggesting that Nrf2 pathway activation is a key mechanism in metformin’s role in delaying human neuronal aging and, by extension, brain aging. Consistent with our in vitro findings, Nrf2 pathway activation was also detected across multiple tissues in metformin-treated monkeys, including frontal lobe neurons.


At last count, I’ve curated 250+ papers this decade on cruciferous vegetables, and many of these explored relationships with Nrf2 activation. Basically, eating a clinically-relevant daily dose of 3-day-old cruciferous sprouts and taking off-patent metformin both induce Nrf2 activation effects.

Don’t expect to see many researchers highlighting this equivalency. They’d rather wait another decade to nitpick other studies with not-enough-subjects / not-exactly replicated / other nitpicks before expressing opinions urging caution from their nursing home beds.

But even then, they won’t get their facts straight. For example, a contemporaneous opinion article https://www.nature.com/articles/d41586-024-02938-w “The brain aged more slowly in monkeys given a cheap diabetes drug” attempted to summarize this study, and flubbed two points:

1. The study said: “We conducted a proof-of-concept study involving male cynomolgus monkeys (Macaca fascicularis) aged between 13 and 16 years, roughly equivalent to approximately 40–50 years in humans. Monkeys adhered to this regimen for a period of 1,200 days, approximately 3.3 years, which corresponds to about 10 years in humans.”

The opinion claimed: “Animals took the drug for 40 months, which is equivalent to about 13 years for humans.”

2. The opinion quoted a New York City researcher involved in a separate metformin study and employed at a medical school for:

“Research into metformin and other anti-ageing candidates could one day mean that doctors will be able to focus more on keeping people healthy for as long as possible rather than on treating diseases.”

This statement is a big break from the realities of medical personnel daily actions at least so far this decade, which is when I started to pay close attention:

  • Doctors have very little diet and exercise training in medical school. There’s no way they can give health advice. There’s no way that a “keeping people healthy” paradigm will emerge from the current medical system.
  • Fixing a disease doesn’t restore a patient’s health. Dr. (PhD) Goodenowe cites several examples in his talks, such as a study that compared colorectal cancer therapy with post-operation patient health.
  • If you listen to yesterday’s two-hour-long podcast, the currently injured person in the first hour gave plenty of contrary evidence of doctors’ focuses: behaviors of trying to blame and gaslight the patient, thinly-disguised punitive actions, CYA etc., all of which they will be sued for one day. The doctor in the second hour provided an example of the quoted researcher in her explanation of how doctors higher in the hierarchy either can’t see or can’t admit realities of doctor/patient interactions, and what therapies have actually benefited or harmed a patient.

A heterochromatin loss theory of aging? Or just an unhealthy system?

A 2024 rodent study investigated epigenetic effects of loosening compacted chromatin:

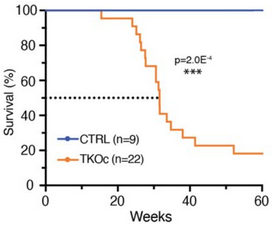
“We show using a novel mouse strain, (TKOc), carrying a triple knockout of three methyltransferases responsible for H3K9me3 deposition, that the inducible loss of H3K9me3 in adulthood results in premature aging. TKOc mice exhibit:

  • Reduced lifespan;
  • Lower body weight;
  • Increased frailty index;
  • Multi-organ degeneration;
  • Transcriptional changes with significant upregulation of transposable elements; and
  • Accelerated epigenetic age.

TKOc survival

Through simultaneous depletion of Setdb1 and Suv39h1/2 methyltransferases, crucial to formation of constitutive heterochromatin, our model analyzes consequential transcription changes including a potential source of genomic instability by activation of endogenous mobile genetic elements, specifically transposable elements.

These findings reveal the importance of epigenetic regulation in aging, and suggest that interventions targeting epigenetic modifications could potentially slow down or reverse age-related decline.”

https://www.biorxiv.org/content/10.1101/2024.07.24.604929v1.full “Loss of H3K9 trimethylation leads to premature aging”


Many of these findings could be restated without viewing them as age-related, i.e.: failure to maintain an adult’s methyltransferase system results in a loss of health. For example, an unhealthy methyltransferase system indicated by parameters like homocysteine levels (not mentioned) can be reversed to healthy function regardless of age. Healthy vs. unhealthy system function wasn’t the paradigm these researchers operated under, though.


PXL_20240726_101120498

Eat broccoli sprouts to reduce knee pain?

A 2024 preprint published results of feasibility trial NCT03878368:

“High glucosinolate broccoli soup is a novel approach to managing osteoarthritis (OA) that is widely accessible and can be used on a large scale. This study shows that it is an acceptable way of delivering dietary bioactives and has potential for therapeutic benefit.

Limitations of the study:

1. COVID-19 curtailed data collection and restricted sample size below that originally planned, however we remained able to derive meaningful interpretation and meet our original study aims.

2. The study had a short time scale (12 weeks). A longer study would be useful to understand how a long-term intervention might be accepted, important for chronic conditions such as OA.

3. The full sample size fell short of the number anticipated, therefore we were unable to use the data to provide a reliable estimate of sample size for a full trial.

4. Participants were excluded if they did not like broccoli to maximise compliance and retention, and so a food intervention should account for this in future developments. While most patients tolerated the soups well, two patients withdrew because they did not like the soup.”

https://www.medrxiv.org/content/10.1101/2024.06.20.24309233v1.full-text “The BRoccoli In Osteoarthritis (BRIO study) – A randomised controlled feasibility trial to examine the potential protective effect of broccoli bioactives, (specifically sulforaphane), on osteoarthritis”


The glucoraphanin dose used was the highest of three tested in 2017 via NCT02300324:

“This study seeks to quantify the exposure of human tissues to glucoraphanin and sulforaphane following consumption of broccoli with contrasting Myb28 genotypes. Myrosinases are intentionally denatured during soup manufacture. Threefold and fivefold higher levels of sulforaphane occur in the circulation following consumption of Myb28V/B and Myb28V/V broccoli soups, respectively.

6b

Myb28V/V and Myb28B/V broccoli soups contained 452 ± 10.6 μmoles glucoraphanin per 300 mL portion and 280 ± 8.8 μmoles glucoraphanin per 300 mL portion respectively, approximately five- and threefold greater glucoraphanin levels compared to Myb28B/B broccoli soup that contained 84 ± 2.8 μmoles glucoraphanin per 300 mL.

The percentage of sulforaphane excreted in 24 h relative to the amount of glucoraphanin consumed varies among volunteers from 2 to 15%, but does not depend on the broccoli genotype.”

https://onlinelibrary.wiley.com/doi/10.1002/mnfr.201700911 “Bioavailability of Glucoraphanin and Sulforaphane from High-Glucoraphanin Broccoli”


Unlike these two papers, I don’t depend primarily on my gut microbiota for results. Microwaving 3-day-old broccoli sprouts to 60°C to create 80% bioavailable sulforaphane then immediately eating it is way more efficient. If depending on an individual’s gut microbiota to convert glucoraphanin into sulforaphane, the best that can be expected is 15% bioavailability.

Don’t think an osteoarthritis clinical trial that depends on a person’s gut microbiota could have steady, predictable results when there could be more than 700% variability (2% to 15%) among subjects’ sulforaphane conversions. If a treatment subject doesn’t have relief from knee pain, there would have to be additional methods to detect that subject’s effective sulforaphane dose based on their gut microbiota conversion ability. Would these researchers suggest that subject change their gut microbiota? What study has reliable results for that?

PXL_20240628_095215629

Astaxanthin and aging

A 2023 rodent study investigated two NRF2-activating compounds for their effects in increasing median and maximum lifespan:

“In genetically heterogeneous (UM-HET3) mice, the Nrf2 activator astaxanthin (Asta) extended the median male lifespan by 12%. Astaxanthin (Asta) is a naturally occurring xanthophyll carotenoid that is an efficient Nrf2 activator, with potent antioxidant activity, broad health applications, and excellent safety.

Asta is distributed systemically and incorporated into cellular membranes, where it spans and stabilizes the lipid bilayer and reduces lipid peroxidation. Asta localizes in mitochondria and protects against mitochondrial dysfunction.

It has anti-inflammatory properties, showing equivalent efficacy to prednisolone in an animal model. Geroprotective mechanisms of Asta regulate FOXO3, Nrf2, Sirt1, and Klotho, and the influence of Asta on autophagy via modulation of AMPK (a direct upstream regulator of mTOR), PI3K/Akt, and MAPK (JNK and p38) signaling pathways.

The present Interventions Testing Program (ITP) study is the first evaluation of Asta in a mammalian lifespan model, so the target dose of 4000 ppm in the diet is based on chronic mammalian studies other than lifespan. Despite the fact that the average diet contained 1840 ppm Asta (only 46% of the target), median lifespans of male UM-HET3 mice were significantly improved.astaxanthin male survival

Asta and dimethyl fumarate (DMF) are both Nrf2 inducers; while both had low concentrations sometimes in the diet, we used about 30 times more Asta, which may explain why it increased the lifespan in males while DMF had no effect. Amounts of DMF in the diet averaged 35% of the target dose, which may explain the absence of lifespan effects.”

https://link.springer.com/article/10.1007/s11357-023-01011-0 “Astaxanthin and meclizine extend lifespan in UM‑HET3 male mice; fisetin, SG1002 (hydrogen sulfide donor), dimethyl fumarate, mycophenolic acid, and 4‑phenylbutyrate do not significantly affect lifespan in either sex at the doses and schedules used”


This study repeated an astaxanthin supplier’s claims without investigating its low bioavailability issues mentioned in Astaxanthin bioavailability. No explanations were forthcoming for unintentional low doses of astaxanthin and DMF in the treatment chows.

A human equivalent for the intended astaxanthin dose was 22 mg (4000 ppb x .081 x 70 kg), whereas the actual dose human equivalent was 10 mg (1840 ppb x .081 x 70 kg). Dose/response studies weren’t performed, so no conclusions could be drawn as to whether the target dose or other astaxanthin doses may be optimal for increasing lifespan.

A previous ITP study of another commercial NRF2 activator (PB125) found no lifespan benefits. Maybe one day, ITP or others will come around to testing sulforaphane that has 80% bioavailability (regardless of sex) and dose/response studies, which should end the uncertainty about NRF2’s anti-aging effects.

How to choose your medical professional

Two+ decades ago (before smart phones) I wrote a series of short books entitled How To Choose Your  Lawyer, ..Accountant, ..Financial Advisor. My customers were mainly public libraries.

This is a short post on choosing doctors, although I’ve fired all my doctors and don’t have one. Everything that’s happened this decade has made me wonder why I trusted doctors in the first place.

1. It takes certain behavioral quirks for doctors to assert they know better than you do about what is good for you. These behaviors usually have nothing to do with these doctors’ patients, but patients somehow believe doctors.

These behaviors are almost always doctors’ act-outs of early-life traumas of unfulfilled needs. Pain keeps people from feeling their actual histories, though, so we don’t deal with our real histories therapeutically until we absolutely have to.

If your doctor listens to you at all, it’s only because they are constantly vigilant for some way to fulfill their own unsatisfied needs. But that neither resolves anything for them, as an early need can’t be satisfied years later, nor has anything to do with what you need from a medical professional.

2. If you’ve read extensively about an area and have questions, a doctor may know less than you. That won’t keep them from gaslighting you due to 1. above, but it does keep you from getting what you need from them. Discussing facts you know with a medical professional who is intentionally ignorant about a medical subject gets you nowhere.

3. If your doctor has not publicly disclaimed their advocacy of this decade’s misguided genetic therapy, they are compromised and can’t be trusted. It doesn’t matter what else they said, because they weren’t honest about what they knew or should have known, as revealed by their actions or inactions.

For example, two studies published in June 2024 established that:

  • Neurologic issues (68% increase in depression, and a 44% increase in anxiety / dissociative / stress-related / somatoform disorders) followed COVID gene therapy: https://www.nature.com/articles/s41380-024-02627-0 “Psychiatric adverse events following COVID-19 vaccination: a population-based cohort study in Seoul, South Korea” (2,027,353 people)
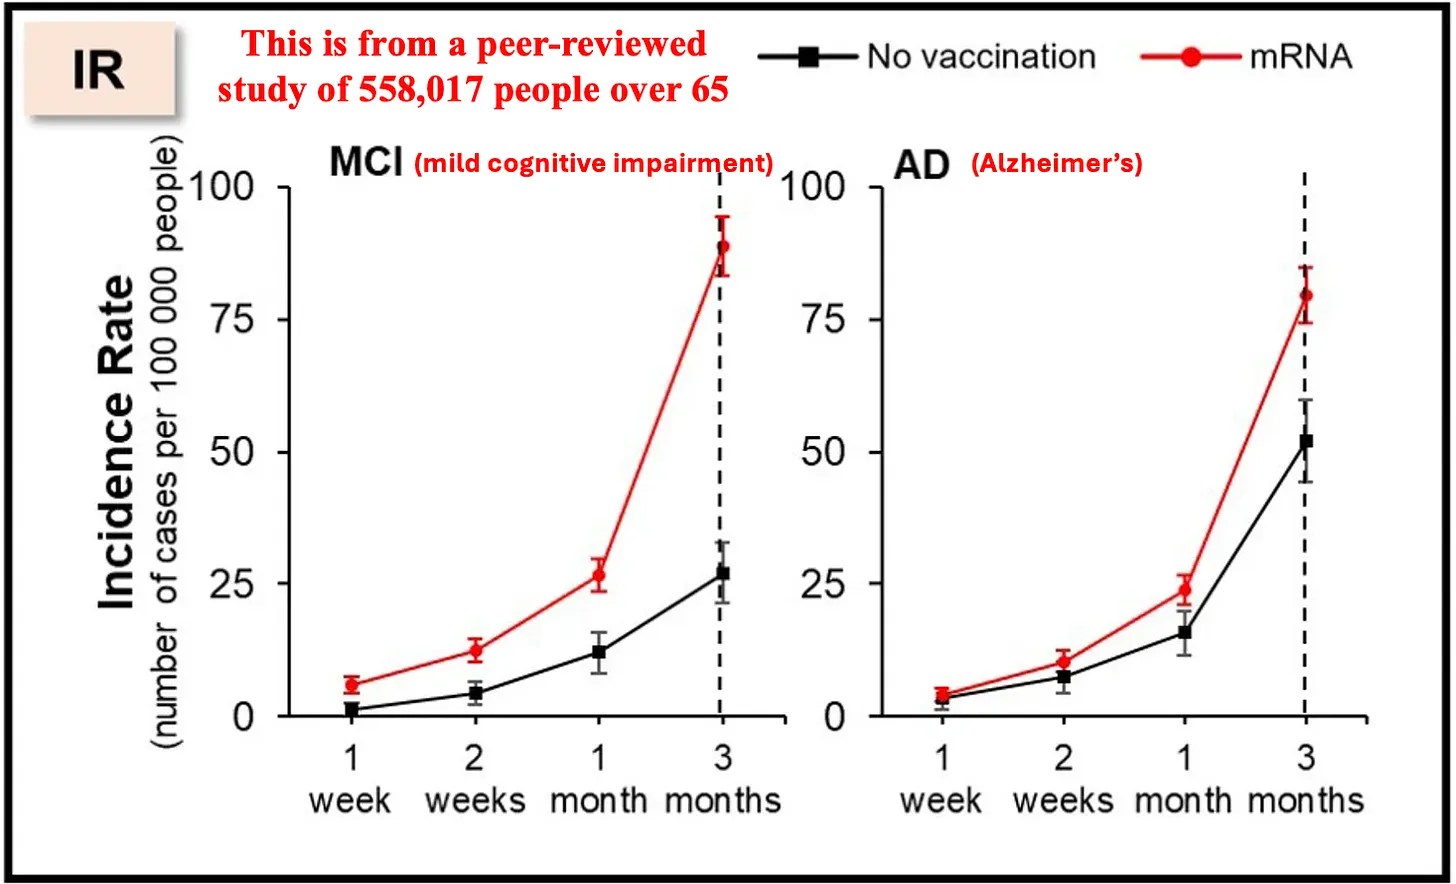
  • COVID gene therapy increased the risk of mild cognitive impairment 138% and the risk of Alzheimer’s by 23%: https://academic.oup.com/qjmed/advance-article-abstract/doi/10.1093/qjmed/hcae103/7684274 “A potential association between COVID-19 vaccination and development of Alzheimer’s disease” (558,017 people). These graphics showed rapidly increasing MCI and AD incidences. The study’s analysis showed incidence increases could not have happened by chance.

ea3f75cb-a071-4cc9-9bd8-0609d0ad8961_1466x890

A doctor’s only honest response to this malfeasance is to publicly apologize, and tell their trusting patients they will make it up to them by providing free healthcare to help mitigate results of their unprofessional conduct. If they tell you something else, it’s a distraction from consequences that are beyond words.

Eat broccoli sprouts to support muscle growth

A 2024 rodent study investigated sulforaphane’s effects on skeletal muscle:

“Sulforaphane (SFN) shows a promising application in skeletal muscle protection and recovery from muscle atrophy and damage. However, limited work has focused on the role of SFN in maintaining the balance of protein and lipid metabolism in skeletal muscle.

The current work investigates effects of SFN at an everyday consumption level on protein and lipid metabolism in skeletal muscle. Investigating SFN at lower levels over an extended period more closely resembles human consumption habits. Four-week-old mice received SFN at a dosage of 1 mg per kilogram of body weight per day (1 mg/kg/d BW) using i.p. injection (SFN1 group) and 3 mg/kg/d BW (SFN3 group) for eight weeks, equivalent to concentrations of 0.14 μM and 0.42 μM.

Histological analysis was performed for the Longissimus dorsi [the largest back muscle]. LD muscle fiber diameter and cross-section area was significantly increased in the SFN3 group, not in the SFN1 group.

SFN muscle growth

The levels of triglycerides and total cholesterol in the LD muscle were found to be decreased in both SFN groups.

This study reported, for the first time, that SFN administration increased peroxisome activity and enhanced the peroxisomal protein shuttle, which supports enhanced peroxisomal fatty acid β-oxidation. SFN redirects the flux of fatty acid to be utilized through β-oxidation in peroxisomes and mitochondria to support muscle growth. Furthermore, SFN treatment influenced lipid and protein metabolism related pathways including AMPK signalling, fatty acid metabolism signalling, cholesterol metabolism signalling, PPAR signalling, peroxisome signalling, TGFβ signalling, and mTOR signalling.”

https://portlandpress.com/bioscirep/article/doi/10.1042/BSR20240084/234562/Sulforaphane-enhanced-muscle-growth-by-promoting “Sulforaphane enhanced muscle growth by promoting lipid oxidation through modulating key signaling pathways”


A human equivalent to this study’s 3 mg daily dose is (3 mg x .081) x 70 kg = 17 mg, albeit doses were intraperitoneally injected. An oral 17 mg is a common sulforaphane floor dose in human studies, and is approximately what I get from eating 60 grams of a microwaved broccoli / red cabbage / mustard 3-day-old sprouts mix daily.

PXL_20240618_094022451

Consequences of perinatal stress

A 2024 rodent study followed up earlier studies of perinatal stress:

“Stress is a multisystemic and multiscale reaction experienced by living beings in response to a wide range of stimuli, encompassing a highly complex order of biological and behavioral responses in mammals, including humans. In the present study, we evaluated changes in mRNA levels in 88 regions of interest (ROIs) in male rats both exposed to perinatal stress and not exposed.

Depending on critical life stage (e.g., perinatal life, infancy, childhood, adolescence, aging), duration, and type of stressor, different effects can be detected by examining behavioral and physiological functions. Stress is related to several cognitive processes, including spatial and declarative memory (involving the hippocampus), fear and memories of emotionally charged events (involving the amygdala), and executive functions and fear extinction (involving the prefrontal cortex).

This PRS paradigm is a well-characterized animal model in which offspring is exposed to stress during pregnancy and after birth because of receiving defective maternal care. Offspring exhibit behavioral hyperreactivity, as well as increased susceptibility to drug addiction and decreased risk-taking behavior.

Starting from day 11 of gestation until delivery, pregnant females were subjected to restraint in a transparent plastic cylinder and exposed to bright light during three daily sessions of 45 min. Since gestational stress induces a <40% reduction of maternal behavior in stressed mothers, we refer to the whole procedure as Perinatal Stress.

Intercorrelation between the orbitofrontal cortex (OFC) and various brain regions such as the thalamus and amygdala were found disrupted in the PRS group. These functional correlations appear to be associated with regulation of executive functions, goal-directed behavior, and directed attention. Also, discrete functional links between the OFC and limbic regions and striatum were lost in the PRS group.

Decreased expression of the Homer1a gene across multiple brain regions after perinatal stress exposure may derange normal architecture of glutamatergic synapses during neurodevelopment and after birth. Changes at the glutamatergic synapse have been considered pivotal in adaptive stress behaviors.

Our results show that PRS preferentially reinforces the centrality of subcortical nodes, resulting in increased centrality of structures such as amygdala, caudate-putamen, and nucleus accumbens, suggestive of reduced cortical control over these regions. In conclusion, when analyzing Homer gene expression after stress exposure not only in terms of quantitative changes compared to the control group, but also as a basis for conducting brain connectivity graph analysis, we observed that perinatal stress could significantly affect the functional connectivity of brain regions implicated in modeling pathophysiology of severe psychiatric disorders.”

https://www.sciencedirect.com/science/article/pii/S0278584624001003 “Perinatal stress modulates glutamatergic functional connectivity: A post-synaptic density immediate early gene-based network analysis”


PXL_20240528_094419674

Eat broccoli sprouts to reverse or prevent glucose-induced metabolic memories

A 2024 human cell study investigated endothelial cell memories of hyperglycemia:

“Transient exposure to high glucose induces enduring transcriptional and chromatin alterations in endothelial cells (ECs). Activation of the NRF2 pathway with sulforaphane can mitigate these cellular memories, offering valuable insight into mechanisms and management of diabetes-associated complications.

LSA-2023-02382_GA

Remarkably, sulforaphane not only prevents most of the aforementioned alterations caused by high glucose (HG), but it can also revert them once established. Although NRF2-independent chemoprotective mechanisms for sulforaphane have been described, our data showing that NRF2 gene overexpression resulted in a similar outcome suggest that beneficial effects conferred by sulforaphane in our HG and memory treatments occur mainly through activation of the NRF2 pathway.

We hypothesize that transient hyperglycemia impacts the epigenetic and functional states of enhancers, priming them to amplify or sustain the transcriptional changes. This mechanism mirrors how inflammation can imprint an enhancer’s epigenetic memory in immune cells and ECs. Ergo, in diabetes patients, repetitive cycles of pathological hyperglycemia could set enhancers into a pathological memory state.

The metabolic memory phenomenon has been studied for over three decades, yet currently, there are no specific treatments to ameliorate diabetes-associated vascular complications, which comprise the leading causes of morbidity and mortality in patients with this disease. Our study highlights the potential use of sulforaphane to revert high-glucose–induced transcriptional and epigenetic memories in human ECs.”

https://www.life-science-alliance.org/content/7/8/e202302382 “Reversal of high-glucose–induced transcriptional and epigenetic memories through NRF2 pathway activation”


A seven-month-long back-and-forth official correspondence history among these researchers and peer reviewers was also published in the Reviewer Comments pdf file, which was informative as to what was and wasn’t included in this study. For examples, in response to peer review comments, the researchers performed an unplanned in vivo rodent study that wasn’t added because it didn’t continue long enough to confirm in vitro human cell primary results. A five-item limitation section was added to this study, though.

PXL_20240516_164820343